The Shadow of the Kissing Disease: Is Mono a Lifetime Illness?
When individuals hear the word "mono"—formally known as infectious mononucleosis—they often immediately picture a brief period of intense fatigue, a sore throat, and a few weeks of missing school or work. Popularly dubbed the "kissing disease" because the Epstein-Barr virus (EBV), its primary culprit, transmits primarily through saliva, mononucleosis is a rite of passage for many teenagers and young adults. Yet, beneath its reputation as a temporary, albeit miserable, teenage affliction lies a complex medical reality that haunts millions long after the initial acute phase fades. The lingering symptoms, intermittent flare-ups, and the virus's uncanny ability to embed itself permanently within the host genome prompt a haunting question for many sufferers: Is mono a lifetime illness?
To understand whether mononucleosis is a permanent sentence, we must separate the acute viral infection from its chronic, long-tail aftermath. While classic acute mononucleosis typically resolves within a few weeks to several months, the underlying pathogen never truly leaves the body. For a distinct subset of patients, the physiological fallout persists for years, blurring the lines between a transient infection and a chronic medical condition. Examining the virology, the epidemiology, the clinical presentation, and the evolving medical consensus surrounding post-viral syndromes provides a comprehensive view of what it truly means to live with the Epstein-Barr virus.
The Anatomy of an Infection: What Happens When Mono Strikes?
Infectious mononucleosis is overwhelmingly caused by the Epstein-Barr virus (EBV), a member of the herpesvirus family. According to global epidemiological data, approximately 90% to 95% of the world’s adult population becomes infected with EBV by the time they reach the age of 35 to 40. This staggering statistic highlights how ubiquitous the virus truly is, even though not everyone develops the classic clinical syndrome of mononucleosis upon initial exposure.
When a person contracts EBV during adolescence or young adulthood—typically between the ages of 15 and 25—the immune response is notably more robust and aggressive than when the infection occurs during early childhood. Children who contract EBV usually experience mild, flu-like symptoms that are easily mistaken for a common cold, whereas adolescents and young adults frequently develop full-blown mononucleosis.
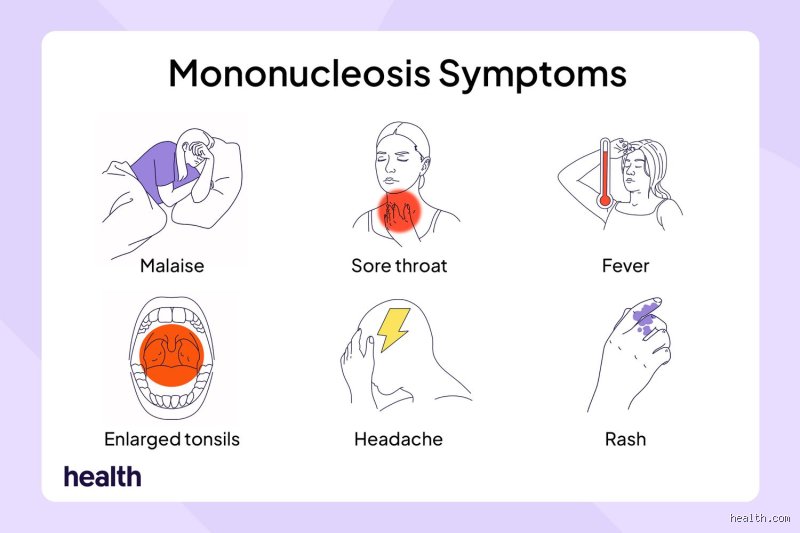
The primary clinical features of acute mononucleosis include:
Profound, debilitating fatigue that can disrupt daily functioning
Severe pharyngitis (sore throat) often accompanied by a white or yellowish exudate on the tonsils
Generalized lymphadenopathy, particularly affecting the posterior cervical lymph nodes
Hepatosplenomegaly (enlargement of the liver and spleen), which carries a rare risk of splenic rupture
Low-grade to high fevers that can persist for weeks
During this acute window, the immune system mounts a massive counteroffensive. T-lymphocytes (specifically CD8+ cytotoxic T cells) proliferate rapidly to destroy cells infected with the virus. This massive immunological battleground is precisely what causes the hallmark swelling of the lymph nodes and the spleen, as these organs work overtime to filter blood and produce infection-fighting white blood cells. Standard diagnostic evaluations, such as the heterophile antibody test (commonly known as the Monospot test) or specific EBV antibody panels, are utilized during this phase to confirm the presence of the active infection. For the vast majority of patients, the immune system successfully suppresses the virus, acute symptoms subside, and normal life resumes. However, for a significant minority, the story does not end at recovery.
The Persistent Ghost: Latency and Viral Persistence
To answer whether mono is a lifetime illness, one must examine the fundamental nature of the Epstein-Barr virus. EBV is a lymphotropic virus, meaning it specifically targets and infects human B-lymphocytes. Once an individual's acute symptoms resolve and they feel completely healthy again, the virus does not vanish from the body. Instead, EBV enters a state known as viral latency.
During latency, the virus shuts down most of its replication machinery, hiding its genetic material inside a small pool of long-lived memory B cells. Because these resting B cells patrol the immune system for years—sometimes decades—the virus successfully evades total eradication by both the host immune response and modern antiviral therapies. In this sense, EBV infection is undeniably lifelong. Once a person contracts the virus, they carry viral DNA within their cellular reservoir for the remainder of their lives.
However, carrying a latent virus is vastly different from suffering from a chronic, active illness. Millions of people harbor latent EBV asymptomatically, experiencing no adverse health consequences whatsoever. The virus remains dormant, held tightly in check by a vigilant immune system. The critical medical dilemma arises when this delicate equilibrium is disturbed, leading researchers to investigate why certain individuals transition from asymptomatic latency to prolonged, debilitating health complications.
Chronic Fatigue and the Post-Viral Aftermath
While standard medical textbooks historically defined mononucleosis as a self-limiting disease lasting no longer than a few weeks, modern clinical observations reveal a much more stubborn trajectory. Clinical studies indicate that approximately 10% to 20% of patients who contract acute mononucleosis fail to make a full recovery within six months. Instead, they experience chronic post-viral fatigue syndrome, a condition characterized by persistent exhaustion, brain fog, unrefreshing sleep, and widespread myalgia.
This prolonged convalescence can be intensely frustrating for patients, particularly when standard blood tests show that the acute infection has passed. The fatigue associated with post-mononucleosis syndrome is not simply the feeling of needing an extra hour of sleep; it is a profound, systemic exhaustion that impairs cognitive function, academic performance, and occupational capacity. Sufferers often find themselves trapped in a cycle of malaise, where minor physical exertion triggers severe post-exertional crashes.
Furthermore, medical research over the past few decades has uncovered compelling epidemiological links between acute Epstein-Barr virus infection and more complex, chronic systemic illnesses. Notably, a substantial body of literature suggests that acute mononucleosis is one of the most prominent environmental triggers for myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS). In these cases, the immune system appears to remain in a state of chronic, dysregulated activation, or the virus undergoes periodic, sub-clinical reactivations that continuously drain the host's physiological resources.
Reactivation, Autoimmunity, and Long-Term Health Risks
Beyond chronic fatigue, the lifelong presence of the Epstein-Barr virus raises critical questions about viral reactivation and its association with autoimmune disorders and oncogenesis. Under conditions of severe physical stress, psychological trauma, or immunosuppression, latent EBV can occasionally reactivate, shedding viral particles into the saliva even in the absence of acute symptoms. While healthy individuals can easily control these minor reactivations, immunocompromised patients—such as organ transplant recipients or individuals undergoing chemotherapy—are at risk for severe EBV-driven complications.
Moreover, extensive immunological research has linked persistent EBV infection to several chronic autoimmune diseases, including systemic lupus erythematosus (SLE), rheumatoid arthritis, and multiple sclerosis (MS). While contracting mono does not guarantee that an individual will develop these complex conditions, viral mimicry and chronic immune stimulation by EBV proteins are heavily implicated as contributing environmental triggers in genetically susceptible hosts. Additionally, persistent EBV infection is a known cofactor in the development of certain malignancies, such as nasopharyngeal carcinoma and specific types of lymphomas, though these severe outcomes remain statistically rare relative to the sheer volume of global EBV infections.
Ultimately, viewing mononucleosis strictly as a short-term inconvenience overlooks the intricate, enduring relationship between the human host and the Epstein-Barr virus. While the acute misery of a swollen throat and profound exhaustion does eventually pass for nearly everyone, the virus establishes a permanent residence within the body, leaving a lingering physiological footprint that continues to command intense scientific research and medical vigilance.
Common mistakes and misconceptions
Navigating the recovery landscape after an acute bout of infectious mononucleosis often leads to widespread confusion. Because the Epstein-Barr virus behaves differently than typical short-term pathogens, patients and even practitioners sometimes fall into persistent analytical traps. Recognizing these faulty assumptions is essential if you want to understand how a temporary illness intersects with long-term bodily changes.
Assuming a negative test means the virus is completely gone
One frequent error is believing that once acute symptoms vanish and standard antibody panels stabilize, the Epstein-Barr virus has been entirely eradicated from your system. In reality, the virus enters a lifelong state of clinical latency housed primarily within memory B cells. Yet, mistaking clinical dormancy for total viral clearance sets up unrealistic expectations for future immune interactions. We must acknowledge that the virus remains a permanent silent resident for nearly all adults, which explains why detecting remnants of past infection years later is a normal biological baseline rather than an active pathology.
Treating post-viral fatigue like standard sleep deprivation
Another pitfall involves treating lingering exhaustion as if it were a simple sleep deficit that responds to an early bedtime. When individuals try to power through post-viral fatigue with high caffeine intake or sheer willpower, they often trigger severe physiological crashes.
Equating a recurrence of symptoms with a brand-new acute infection
A final widespread misconception is assuming that any sudden wave of exhaustion or swollen glands months later represents a reinfection of mono. True clinical reinfection with acute mononucleosis is exceptionally rare in healthy individuals.
To summarize, while the acute misery of mononucleosis typically fades within a few weeks, the underlying viral relationship is genuinely permanent.
How has your own energy management changed since navigating a prolonged viral recovery?