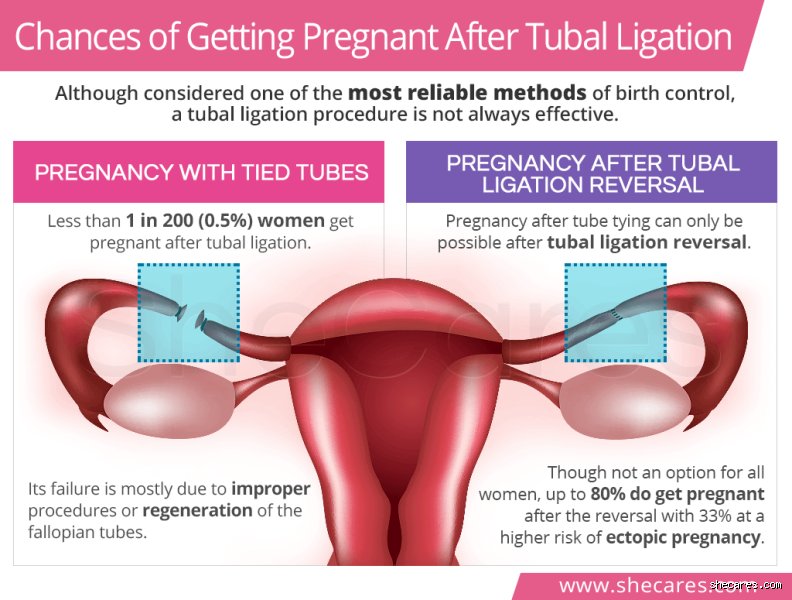
When individuals evaluate their reproductive health several years down the line, a frequent point of inquiry is whether the protective efficacy of the procedure holds steady or if the likelihood of a spontaneous conception shifts as time passes. Specifically, examining the window roughly seven years post-procedure opens up critical discussions surrounding long-term bodily changes, physiological tissue adaptation, and cumulative failure probabilities. This comprehensive expert analysis explores the mechanics, statistics, and physiological phenomena that dictate the likelihood of pregnancy seven years after undergoing a tubal ligation.
The baseline efficacy: How tubal ligation works over Time
To comprehend the probability of pregnancy at the seven-year mark, it is essential to first understand the foundational mechanics of how tubal ligation prevents conception. The fallopian tubes serve as the vital biological highway where a sperm cell must meet and fertilize a released oocyte (egg). A tubal sterilization procedure interrupts this pathway by blocking, cutting, banding, clipping, or removing sections of the fallopian tubes.
Because various surgical techniques are utilized, the long-term integrity of the closure depends heavily on the specific method implemented during the initial operation:
Postpartum Partial Salpingectomy (e.g., Pomeroy technique): Involves tying and removing a portion of the tube shortly after childbirth.
Electrocoagulation (Unipolar or Bipolar): Uses electric current to seal or destroy segments of the tube.
Mechanical Clips and Rings: Devices such as Filshie clips or spring-loaded clips are clamped across the tube to block passage.
Data compiled across extensive multi-year observation periods demonstrates that the cumulative probability of pregnancy is not distributed evenly across the lifespan of the sterilization. In the immediate aftermath of the surgery, most failures are attributed to technical oversight, such as an unrecognised pre-existing luteal-phase pregnancy or an incomplete initial occlusion. However, as the timeline extends toward five, seven, and ten years, the nature of the risk profile shifts entirely toward physiological adaptations of the human body.
Cumulative failure probabilities at the 7-Year milestone
When looking specifically at long-term timelines, medical literature tracks failures using cumulative probability tables per 1,000 procedures. While the standard clinical narrative often cites a generalized failure rate of roughly 1% to 2% over a decade, the precise likelihood at year seven is heavily influenced by the cumulative curve.
Long-term tracking indicates that the risk of a post-sterilization pregnancy does not drop to zero after the first few years; rather, it accumulates incrementally. For instance, landmark tracking from the CREST study highlighted that the cumulative 10-year probability of pregnancy varied dramatically depending on the technique used:
Spring clip applications showed some of the highest cumulative failure rates over time, approaching higher thresholds per 1,000 procedures.
Bipolar coagulation and postpartum partial salpingectomy generally maintained lower, more stable long-term cumulative probabilities, though they were still non-zero.
At the seven-year mark, a woman sits squarely in the middle-to-late phase of the standard longitudinal risk window. Clinical reviews tracking intervals of sterilization failure frequently note that a significant cluster of delayed failures manifests between the one-to-five and six-to-ten-year brackets. This means that year seven represents a period where biological factors, rather than acute surgical errors, take center stage in instances where the procedure fails.
The biological mechanisms behind late failures
Why would a pregnancy occur as late as seven years after a procedure designed to be permanent? The answer lies in the dynamic, living nature of human tissue. The body possesses remarkable regenerative capabilities, and fallopian tubes are biologically active structures that can sometimes circumvent mechanical blocks through unique processes:
1. Spontaneous Recanalization
The most prominent driver of late-stage tubal ligation failure is spontaneous recanalization. Over months and years, severed or cauterized ends of the fallopian tubes can occasionally heal, find one another, and re-establish a microscopic luminal passage. This neo-channeling allows sperm to traverse the previously blocked tube and successfully fertilize an egg, catching patients completely unawares many years after their initial surgery.
2. Tuboperitoneal Fistula Formation
In some cases, even when the primary ligation remains secure, a small fistula (an abnormal passage or channel) can form between the proximal segment of the fallopian tube and the peritoneal cavity. This microscopic opening can bypass the blocked section entirely, creating a secondary route for fertilization.
3. Migration and Mechanical device failure
For procedures utilizing clips, bands, or rings, the mechanical integrity of the device can alter over a prolonged period. Tissue necrosis beneath a tight clip, slippage of the device due to chronic pelvic movements, or gradual erosion can compromise the occlusion, permitting the restoration of tubal patency well into the lifecycle of the patient.
...[Continued from previous sections]
Understanding the 7-Year horizon: Cumulative probability
When analyzing the likelihood of pregnancy 7 years after a tubal ligation, medical professionals rely heavily on landmark epidemiological investigations like the Collaborative Review of Sterilization (CREST) study. A common misconception is that the failure rate of a tubal ligation remains flat year after year, or that if a procedure is going to fail, it will do so within the first few months. In reality, data demonstrates that sterilization failures accumulate steadily over time.
At the 7-year mark, the cumulative probability of pregnancy depends heavily on the specific technique used during the initial surgery. For instance:
Bipolar Coagulation and Spring Clips: These methods historically exhibit a higher cumulative failure rate over extended periods, with probabilities climbing steadily past the 5-year and 7-year milestones.
Postpartum Partial Salpingectomy and Unipolar Coagulation: These techniques generally maintain the lowest long-term failure rates, though a small, persistent risk remains.
Statistically, across all methods evaluated in major long-term cohorts, the cumulative 10-year failure rate sits at approximately 1.85% (or roughly 18.5 per 1,000 procedures). By year 7, a significant portion of this cumulative window has elapsed, meaning that while the annual risk in any single given year remains low (often less than 0.2% to 0.3% per year depending on age and method), the cumulative chance since day one is higher than what patients are often initially told.
Key factors influencing Late-Term failures
Not all patients face the exact same risk profile 7 years down the line. Several critical variables dictate whether a patient is at a higher or lower statistical risk of a late tubal ligation failure:
Age at the Time of Surgery: This is one of the most powerful predictors of sterilization failure. Women who undergo tubal ligation at a younger age (particularly under age 28) have a substantially higher cumulative probability of pregnancy over a 5-, 7-, or 10-year span. This is not because the surgical technique degrades, but rather because younger biological systems possess higher baseline fertility, stronger tissue healing capabilities, and a greater biological drive for cellular recanalization.
The Specific Occlusion Method: The mechanism used to block or remove the tubes matters immensely. Methods that destroy larger segments of the fallopian tube thermal-electrically or via complete removal (salpingectomy) carry near-zero failure rates. Conversely, mechanical barriers like clips or rings leave more intact tissue that can theoretically heal or form fistulas over multi-year periods.
Anatomical Recanalization and Fistula Formation: Over a multi-year timeline, the human body exhibits an incredible capacity for tissue repair. In rare instances, the severed ends of a fallopian tube can naturally reapproximate, or a tiny microscopic channel (a tuboperitoneal fistula) can form, allowing a sperm to reach and fertilize an egg long after the procedure was deemed complete.
Recognizing symptoms and clinical implications
Because a pregnancy occurring 7 years post-procedure is entirely unexpected, patients rarely connect early symptoms to the possibility of gestation. It is vital for individuals to recognize that any delayed, missed, or unusual menstrual cycle warrants attention, even years after permanent sterilization.
Medical literature highlights an essential clinical caveat: if a tubal ligation fails, the resulting pregnancy carries a much higher statistical likelihood of being ectopic (implanting outside the uterine cavity, most commonly in the remaining fallopian tube) compared to pregnancies in the general population. Up to one-third of post-sterilization pregnancies are ectopic, making prompt medical evaluation critical if a positive test occurs.
Conclusion
While tubal ligation remains one of the most secure and reliable forms of permanent birth control available, "permanent" does not mathematically equal absolute zero risk. At 7 years post-procedure, the cumulative probability reflects years of potential exposure time, biological tissue changes, and age-related variables. Anyone experiencing unusual symptoms or suspected pregnancy signs years after their procedure should consult a healthcare provider immediately to ensure accurate diagnosis and safe management.