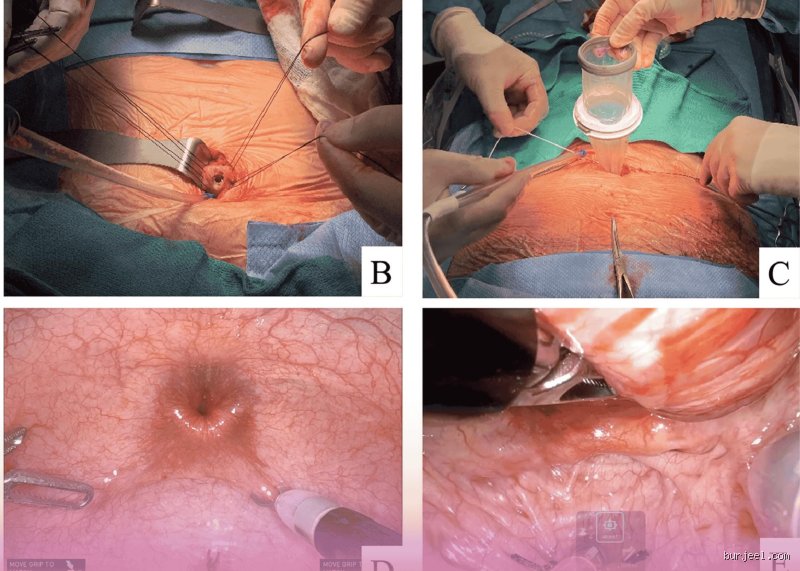
The short, clinically honest answer is yes. A radical prostatectomy—the surgical removal of the prostate gland along with some surrounding tissue and frequently nearby lymph nodes—is a major surgical intervention. It is classified as major pelvic surgery due to the anatomical location of the prostate, its intricate neighborhood of vital nerves and blood vessels, and its crucial role in both urinary and sexual functioning. However, while the procedure is undeniably significant, modern surgical advancements, high-definition visualization tools, and refined techniques such as robotic-assisted and laparoscopic surgery have radically transformed what "major surgery" means for the patient today compared to just a few decades ago.
To fully understand the magnitude, complexity, and implications of a prostatectomy, this expert guide breaks down the anatomy, the surgical landscape, the physiological impacts, and what patients can realistically expect before, during, and after the operating room.
1. Deconstructing the anatomy: Why location matters
To appreciate why a radical prostatectomy is considered a major operation, one must first examine where the prostate lives and what it is surrounded by.
The prostate is a walnut-sized exocrine gland situated deep within the male pelvis. It sits directly underneath the urinary bladder and wraps entirely around the urethra, the muscular tube that carries urine out of the body from the bladder and semen out during ejaculation. Because of this strategic bottleneck, any intervention involving the prostate directly impacts the urinary tract.
The prostate does not exist in an empty space; it is packed tightly against critical pelvic structures:
The Urinary Sphincter: A specialized ring of muscles located just below the prostate that acts as a valve to maintain urinary continence.
The Neurovascular Bundles (Cavernous Nerves): Delicate, microscopic networks of nerves and blood vessels that run directly along the left and right outer walls of the prostate. These nerves are entirely responsible for generating spontaneous erectile function.
The Rectum: The final section of the large intestine, which lies immediately posterior (behind) the prostate gland, separated only by a thin layer of connective tissue known as Denonvilliers' fascia.
Because the prostate is nestled in this tight, confined pelvic cavity, surrounded by structures critical for quality of life, the margin for surgical error is extraordinarily narrow. The surgeon must operate with millimeter precision, navigating around the urinary sphincter to preserve continence, carefully dissecting the neurovascular bundles to preserve sexual function, and avoiding injury to the rectum. It is this combination of delicate anatomy in a deep, narrow surgical field that elevates a prostatectomy from a routine procedure to a major, high-stakes pelvic operation.
2. The evolution of the procedure: Open vs. Minimally invasive Surgery
Historically, removing the prostate meant a large, open incision running from the navel down to the pubic bone (a retropubic radical prostatectomy) or an incision through the perineum (the area between the scrotum and anus). While effective at removing diseased tissue, open radical prostatectomies came with significant physical costs: substantial blood loss, extended hospital stays (often 3 to 5 days or more), large scars, significant postoperative pain, and a lengthy, uncomfortable recovery period lasting many weeks or months.
Over the last twenty years, however, the paradigm of prostate surgery has shifted dramatically toward minimally invasive approaches. Today, the vast majority of radical prostatectomies performed in specialized centers are either laparoscopic or robotic-assisted laparoscopic prostatectomies (RALP).
The Robotic-Assisted Approach
The robotic-assisted technique utilizes a sophisticated computer-enhanced system (such as the da Vinci surgical system) operated by a surgeon sitting at an ergonomic console a few feet away from the patient.
Magnified 3D Visualization: The surgeon views the surgical field through high-definition, 3D-stabilized optics that magnify the delicate nerves and blood vessels up to ten times their actual size.
EndoWrist Articulation: The robotic instruments possess mechanical wrists that mimic and exceed the range of motion of the human hand, filtering out any natural tremors and allowing for ultra-precise dissection in the tight confines of the pelvis.
Smaller Incisions: Instead of a single large open incision, the operation is performed through four to six tiny "keyhole" punctures through which the camera and instruments are inserted.
Clinical benefits of minimally invasive techniques
The transition from open surgery to robotic and laparoscopic platforms has profoundly altered the recovery trajectory for patients:
Drastically Reduced Blood Loss: Better visualization and precise electrocautery minimize bleeding, significantly reducing the likelihood that a blood transfusion will be necessary during the procedure.
Shorter Hospitalization: Most patients undergoing robotic prostatectomy are discharged home either the same day or after a single overnight stay.
Minimized Postoperative Pain: Smaller abdominal incisions translate to far less wall trauma, lower narcotic pain medication requirements, and quicker mobilization.
Faster Return to Normal Activities: While internal healing still takes time, patients are generally able to resume light daily activities, walking, and work much sooner than their open-surgery counterparts.
Despite these remarkable technological leaps, it is crucial to recognize that the internal work remains just as complex. Regardless of whether a robot or a human hand holds the instrument, the surgeon is still performing a radical extirpation (complete removal) of an organ and meticulously reconstructing the urinary tract. The technology enhances precision, but it does not diminish the fundamental gravity of the surgery itself.
3. Anticipating the physiological impact: Continence and potency
When patients ask if a prostatectomy is a "big operation," they are usually thinking beyond the physical incision and the hospital stay. They are deeply concerned with the functional aftermath, specifically, how the surgery will impact their ability to control their bladder and maintain sexual intimacy. These two considerations form the core of why this procedure carries immense emotional and psychological weight.
Urinary Incontinence: The temporary Normal
Immediately following the removal of the catheter (typically 7 to 14 days post-surgery), almost all patients experience some degree of urinary leakage or stress incontinence. Because the prostate was wrapped around the base of the bladder and intimately connected to the urinary sphincter, the sphincter muscle requires time and targeted rehabilitation (such as pelvic floor physical therapy and Kegel exercises) to regain its strength and tone.
For the vast majority of men, urinary control returns progressively over a period of weeks to several months. While permanent, severe incontinence is rare in the hands of experienced high-volume surgeons, managing the recovery phase requires patience, protective pads, and lifestyle adjustments, making the early postoperative period uniquely challenging.
Erectile function: Navigating nerve preservation
The impact on sexual function depends heavily on two primary factors: the patient's baseline erectile function before surgery and whether the surgeon is able to perform a nerve-sparing procedure.
If cancer is contained entirely within the prostate and has not invaded the surrounding tissues, the surgeon can often preserve one or both of the neurovascular bundles. However, if the tumor is aggressive or abuts the outer edge of the prostate, the surgeon may have to sacrifice one or both nerve bundles on one or both sides to ensure complete cancer removal (a non-nerve-sparing approach).
Even with bilateral nerve-sparing surgery, erections do not return overnight. Because the delicate nerves experience stretching, thermal energy, and localized trauma during the dissection, they enter a temporary state of "neuropraxia" (stunning). Recovery of natural erectile function can take anywhere from 12 to 24 months, and many patients require penile rehabilitation protocols involving oral medications, vacuum erection devices, or intracorporeal injections to stimulate blood flow and promote nerve healing during this recovery window.
4. Preparing for the road ahead
Understanding that a radical prostatectomy is a major surgical event allows patients and their families to mentally and physically prepare. Preoperative optimization, including smoking cessation, optimizing cardiovascular health, engaging in pelvic floor muscle training ("prehab") before surgery, and establishing a robust support system at home, matters a lot in achieving optimal surgical outcomes.
In the second part of this expert analysis, we will examine the detailed intraoperative timeline, the specific risks and complications associated with the procedure, the step-by-step recovery milestones during the first year, and how multidisciplinary care teams work together to safeguard both cancer control and long-term quality of life.
Navigating the Postoperative Recovery landscape: What to Expect
When evaluating whether removing the prostate is a major operation, analyzing the surgical theater itself tells only half the story. The true magnitude of a radical prostatectomy or simple prostatectomy is deeply reflected in the rehabilitation timeline, physiological adjustment period, and the meticulous care required during the weeks and months following the procedure. While modern advancements, particularly robot-assisted laparoscopic techniques, have dramatically reduced hospital stays, incision sizes, and immediate blood loss, the biological footprint of the operation remains substantial.
The Immediate Post-Discharge phase (weeks 1 to 2)
For most patients undergoing minimally invasive prostate removal, discharge occurs within 24 to 48 hours. However, leaving the hospital marks merely the beginning of a delicate recovery window at home.
The Urinary Catheter: Perhaps the most tangible reminder of major pelvic surgery is the indwelling urinary catheter, which remains in place for typically 5 to 14 days to allow the fresh surgical anastomosis (the newly stitched connection between the bladder and the urethra) to heal. Managing this catheter requires diligence, patience, and strict adherence to hygiene protocols to prevent urinary tract infections.
Mobility Versus Restriction: While surgeons strongly encourage early, gentle walking on the very day of the operation to stimulate circulation and prevent dangerous blood clots (deep vein thrombosis), heavy lifting, strenuous exercise, twisting, and straining are strictly prohibited. Patients are typically advised not to lift anything heavier than 10 pounds for at least four weeks.
Pain Management: While laparoscopic and robotic approaches minimize large abdominal wall incisions, internal trauma to the deep pelvic floor muscles, nerves, and connective tissue still causes notable soreness, pelvic aches, and fatigue. This is typically managed with a combination of prescribed or over-the-counter analgesics, alongside stool softeners to avoid straining during bowel movements.
Long-Term functional implications: Urinary and sexual Health
The reason a prostatectomy is universally classified as a major operation lies not in its immediate mortality risk, which is remarkably low in specialized centers, but in its potential impact on a patient’s long-term quality of life. The prostate sits in an anatomical crossroads surrounded by a dense meshwork of delicate nerves, blood vessels, and urinary sphincter muscles.
1. Urinary Control and Incontinence
Because the prostate physically wraps around the urethra just below the bladder neck, its removal temporarily or sometimes permanently alters the urinary sphincter mechanism.
The Trajectory: Immediately after the catheter is removed, most men experience varying degrees of stress or urge incontinence. Leaking when coughing, sneezing, laughing, or lifting is common.
Rehabilitation: Recovery is a gradual neuromuscular retraining process. Pelvic floor muscle therapy (frequently referred to as Kegel exercises) matters a lot in strengthening the remaining supportive structures. While many patients regain reliable bladder control within 3 to 6 months, a subset of individuals may require up to a year or secondary interventions to achieve total dryness.
2. Sexual function and erectile Recovery
The delicate cavernous nerves responsible for spontaneous erections run directly alongside the prostate capsule. Even with advanced "nerve-sparing" techniques, these microscopic nerve fibers undergo temporary trauma, stretching, or stunning during the dissection.
The Healing Process: Post-operative erectile dysfunction (ED) is an expected short-term hurdle. Function returns slowly, often taking anywhere from several months to two years as the neural pathways regenerate.
Penile Rehabilitation: Urologists frequently outline proactive medical strategies, such as phosphodiesterase type 5 (PDE5) inhibitors or vacuum erection devices, to encourage blood flow, preserve tissue health, and optimize long-term recovery outcomes. Because the prostate and seminal vesicles are removed, patients experience dry orgasms, meaning climax occurs without the emission of seminal fluid, rendering natural fertility impossible.
The oncological verdict: Weighing risk Versus reward
Defining a prostatectomy as a "big operation" depends heavily on the context of why it is being performed. For individuals diagnosed with localized, intermediate-to-high-risk prostate cancer, radical prostatectomy serves as a cornerstone curative treatment designed to eradicate malignant tissue before it can spread beyond the capsule.
When balanced against the alternative of untreated disease progression, the temporary and permanent side effects of surgery are weighed carefully by patients and multidisciplinary oncology teams. Modern surgical innovations have refined the procedure into a highly precise science, yet it remains a profound physiological event. Approaching a prostatectomy requires thorough pre-operative education, realistic expectations regarding the multi-month recovery curve## Navigating the Recovery Journey: What to Expect After Prostate Surgery
Removing the prostate, medically known as a radical prostatectomy, is a major surgical procedure that marks a significant milestone in the treatment of localized prostate cancer. While the initial section of an expert guide often focuses on the surgical indications, operative techniques (such as open, laparoscopic, or robot-assisted approaches), and the immediate intraoperative experience, the true narrative of recovery unfolds in the weeks, months, and years that follow.
Understanding the full scope of the recovery trajectory helps patients and their families approach the post-operative period with realistic expectations, empowering them to actively participate in their rehabilitation and long-term wellness.
Phase 1: The Immediate Post-Operative period (the first 1 to 6 weeks)
Hospital stay and early mobilization
For modern robot-assisted laparoscopic radical prostatectomies, the hospital stay is remarkably brief, often just one night, and occasionally even outpatient depending on the patient's baseline health and the surgeon's protocol. Open procedures may require a two- to three-day hospital admission.
Regardless of the approach, early mobilization is a cornerstone of modern enhanced recovery after surgery (ERAS) protocols. Nurses and physical therapists will encourage getting out of bed and walking within hours of waking up from anesthesia. Walking is not merely a test of mobility; it is a critical medical intervention that:
Promotes normal bowel motility, reducing postoperative ileus (paralysis of the intestines).
Prevents deep vein thrombosis (DVT) and pulmonary embolisms by keeping blood circulating through the lower extremities.
Helps expand the lung bases, minimizing the risk of postoperative atelectasis or pneumonia.
Managing the Urinary Catheter
Perhaps the most notable feature of the first one to two weeks at home is the indwelling Foley catheter. Because the bladder and the urethra are surgically disconnected during the removal of the prostate and then meticulously reconnected (a process called vesicourethral anastomosis), a watertight seal must be allowed to form. The catheter ensures that urine is continuously drained from the bladder, keeping pressure off the fresh surgical suture line.
Living with a catheter requires patience and strict hygiene:
Drainage Management: Patients manage a leg bag during the day and a larger gravity-drainage bag at night. Keeping the bags lower than the bladder at all times is crucial to prevent urine backflow.
Bladder Spasms: It is common to experience intermittent bladder spasms, cramping sensations in the lower abdomen or a sudden, intense urge to urinate around the catheter. These are typically managed with prescribed medications such as anticholinergics or mild pain relievers.
Catheter Removal Day: After typically 7 to 14 days (determined by the surgeon, sometimes verified with a cystogram X-ray to ensure the connection has healed), the patient returns to the clinic for catheter removal. This is a quick, painless procedure that provides an immediate psychological and physical boost, though it marks the beginning of the next phase: regaining urinary control.
Wound care, Pain Management, and activity restrictions
Incisions: For robotic surgery, small keyhole incisions will have surgical glue or steri-strips. These should be kept clean and dry. Showers are usually permitted after 48 hours, but soaking in a tub or pool is strictly prohibited until the incisions are fully healed.
Pain Control: While surgical pain is generally well-managed compared to traditional open surgeries, patients often experience mild to moderate discomfort, shoulder pain (from the carbon dioxide gas used during laparoscopy), and soreness around the port sites. Non-narcotic pain relievers (like acetaminophen or ibuprofen, as approved by the physician) gradually replace stronger prescription narcotics within the first week.
Restrictions: Heavy lifting (anything over 10 pounds), strenuous exercise, and sexual activity are strictly restricted for 4 to 6 weeks to protect the internal anastomosis and pelvic floor.
Phase 2: Medium-Term Recovery (months 2 to 6)
Once the catheter is removed, the focus of recovery shifts toward two primary quality-of-life domains: urinary continence and sexual function.
Regaining Urinary continence
The urinary sphincter mechanism undergoes significant disruption during a radical prostatectomy. The prostate itself acts as part of the internal urinary sphincter, and its removal means that continence relies entirely on the external rhabdosphincter and the support of the pelvic floor muscles.
Immediate Incontinence: It is entirely normal to experience urinary leakage, ranging from minor spotting when coughing, sneezing, or lifting, to more substantial leakage, immediately after the catheter comes out.
Pelvic Floor Rehabilitation (Kegel Exercises): Patients are strongly encouraged to work with specialized pelvic floor physical therapists. Learning how to properly isolate and strengthen the levator ani and sphincter muscles accelerates the return of dryness. Consistency is paramount; doing targeted pelvic floor contractions daily retrains the neuromuscular pathways.
The Recovery Timeline: Continence recovery is a gradual curve. Many men achieve predictable control within 3 to 6 months, though for some, minor improvements can continue up to 12 to 18 months post-surgery.
Navigating sexual Health and erectile function
The nerves responsible for erections (the neurovascular bundles) run along the outer edges of the prostate. Depending on the cancer's stage, location, and aggressiveness, surgeons may perform a "nerve-sparing" procedure on one side, both sides, or neither side.
Penile Rehabilitation: Even with nerve-sparing techniques, erectile function is temporarily stunned by the surgical manipulation. Modern urology emphasizes "penile rehabilitation", the early introduction of oral medications (PDE5 inhibitors like sildenafil or tadalafil), vacuum erection devices, or intracavernosal injections, to maintain blood flow to the erectile tissues, prevent fibrosis (scarring), and encourage natural nerve recovery over time.
Psychological Adjustment: Sexual recovery after prostate surgery is a journey that often requires open communication with partners, emotional patience, and sometimes consultation with a sexual health therapist or counselor to navigate changes in intimacy.
Phase 3: Long-Term outlook and survivorship (6 months and beyond)
As patients move past the six-month mark, the day-to-day focus shifts from acute healing to long-term cancer surveillance and lifestyle adaptation.
Oncological Follow-Up: The PSA test
The ultimate measure of surgical success is the eradication of the cancer. Because all prostate tissue (and hopefully the cancer within it) was removed, the patient’s Prostate-Specific Antigen (PSA) levels should drop to an undetectable level (typically less than 0.1 ng/mL) within 6 weeks to 3 months post-surgery.
Regular Monitoring: Periodic blood tests to check PSA levels are scheduled regularly, usually every 3 to 6 months for the first two years, then annually thereafter.
Peace of Mind vs. Vigilance: A persistently undetectable PSA provides profound reassurance. However, if the PSA begins to rise, it serves as an early warning sign of biochemical recurrence, prompting discussions about further localized treatments, such as salvage radiation therapy.
Long-Term lifestyle and wellness
A radical prostatectomy is a major life event, but it does not define a man's future capacity for a vibrant, active life. Long-term survivorship thrives on proactive health habits:
Cardiovascular Health: Regular aerobic exercise supports overall cardiovascular health, which is intrinsically linked to erectile recovery and general well-being.
Nutritional Balance: A diet rich in fruits, vegetables, whole grains, and lean proteins supports overall health and immune function.
Support Networks: Joining cancer survivorship support groups can provide invaluable emotional outlets, connecting patients with peers who have navigated the exact same surgical path.
Conclusion
So, is removing the prostate a big operation? Anatomically and surgically, yes. It involves delicate work in a confined space surrounded by critical structures controlling urinary and sexual function.
However, when evaluated through the lens of modern surgical innovation, comprehensive perioperative care, and dedicated rehabilitation, it is a manageable journey with a high rate of successful cancer control and restored quality of life. By understanding the phases of recovery, from the early days of catheter management to the gradual return of continence and vitality, patients can face the procedure with confidence, clarity, and resilience.