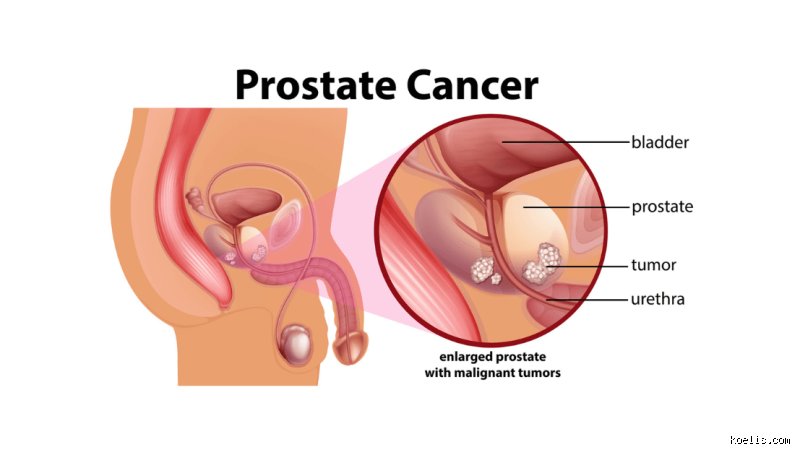
When facing a prostate cancer diagnosis, patients and their families are often swept into a whirlwind of medical consultations, diagnostic imaging, and urgent treatment decisions. Among the most common and historically established interventions for localized prostate cancer is radical prostatectomy—the surgical removal of the entire prostate gland and surrounding tissues.
For decades, surgery has been presented as a definitive way to eradicate cancerous cells trapped within the gland. However, while modern surgical techniques, such as nerve-sparing robotic-assisted laparoscopy, have advanced significantly, the procedure remains a major physiological and psychological hurdle. To make an informed decision, patients must look beyond survival statistics and oncological outcomes to confront the profound, multifaceted downsides of prostate removal.
This in-depth exploration examines the physiological, functional, and psychological consequences of radical prostatectomy, providing a comprehensive view of what recovery truly entails.
1. The Immediate Postoperative Phase and Surgical Risks
Every major surgical intervention carries inherent risks, and a radical prostatectomy is no exception. Because the prostate sits deep within the male pelvis, surrounded by a complex web of delicate nerves, major blood vessels, and adjacent organs like the bladder and rectum, the operation is surgically demanding.
Anesthesia and Perioperative Complications
As with any major surgery requiring general anesthesia, patients face risks associated with cardiopulmonary stress, adverse drug reactions, and prolonged immobilization. While modern operating rooms boast exceptional safety records, the risk of anesthetic complications remains a baseline reality, particularly for older men who may have underlying cardiovascular or pulmonary comorbidities.
Hemorrhage and Blood Transfusions
The prostate gland is exceptionally vascular, receiving a rich supply of blood from branches of the internal iliac artery. During dissection, particularly around the dorsal venous complex, significant bleeding can occur. While surgical expertise has minimized the need for blood transfusions compared to open techniques of the past, the risk of intraoperative hemorrhage requiring a transfusion remains present.
Lymphocele Formation and Infection
During a radical prostatectomy, surgeons frequently perform a pelvic lymph node dissection to check for micro-metastases. Removing these nodes can occasionally disrupt lymphatic drainage, leading to the accumulation of lymph fluid in the pelvic cavity, known as a lymphocele. If a lymphocele becomes large or infected, it can cause severe pelvic pain, deep venous thrombosis, or require subsequent drainage procedures. Furthermore, surgical site infections, urinary tract infections, and sepsis remain potential risks during the initial weeks of recovery.
2. The Devastating Impact on Urinary Continence
Perhaps the most universally feared and challenging consequence of prostate removal is the disruption of urinary control. To understand why urinary leakage is so common after prostatectomy, one must look closely at pelvic anatomy.
The Anatomy of Continence
The prostate gland acts as an internal anchor and functional extension of the urinary sphincter mechanism. The bladder neck connects directly to the top of the prostate, while the external urinary sphincter (a ring of striated muscle fibers) sits immediately below the apex of the prostate. During a radical prostatectomy, the surgeon must cut the urethra both above and below the prostate, completely removing the gland, and then re-stitch the bladder neck directly to the remaining urethra (a process known as vesicourethral anastomosis).
This process inherently disrupts the natural sphincteric architecture. Even with meticulous, nerve-sparing techniques that preserve the external sphincter, the trauma to the surrounding supporting tissues, nerves, and blood supply is substantial.
The Timeline and Spectrum of Incontinence
Postoperative urinary leakage ranges from mild stress urinary incontinence—where a man leaks a few drops of urine when coughing, sneezing, lifting heavy objects, or laughing—to total, continuous incontinence requiring heavy protective padding.
Immediate Post-Removal: Virtually 100% of men experience significant urinary incontinence immediately after the urinary catheter is removed (typically 1 to 3 weeks post-surgery). At this stage, the newly formed anastomosis is healing, and the external sphincter is stunned and unsupported.
Medium-Term Recovery (3 to 6 Months): Through diligent pelvic floor physical therapy (Kegel exercises), biofeedback, and progressive healing, the vast majority of men regain significant control. However, "significant control" often still means wearing a light safety pad daily.
Long-Term Persistence: A substantial subset of patients—ranging anywhere from 5% to 20% or more, depending on age, baseline bladder function, and the surgeon's skill—experience permanent, long-term urinary incontinence. For these men, the chronic need for protective pads, the physical discomfort of skin chaffing, and the constant psychological anxiety of accidental leaks profoundly diminish their day-to-day quality of life.
3. Sexual Dysfunction: Erectile Impairment and Structural Changes
Sexual health is a cornerstone of overall well-being and intimacy for many men. Unfortunately, radical prostatectomy is notorious for its devastating impact on sexual function, altering both erectile capacity and the mechanics of orgasm.
The Vulnerability of the Cavernous Nerves
Running directly along the lateral capsules of the prostate are the neurovascular bundles (the cavernous nerves). These microscopic bundles of nerves are responsible for transmitting the electrical signals from the brain that trigger an erection.
Even in the hands of an expert surgeon utilizing "nerve-sparing" techniques—where the surgeon deliberately works to peel these delicate nerve fibers away from the prostate—the nerves suffer from unavoidable thermal energy (from cauterization), stretching, bruising, and traction during the operation.
Erectile Dysfunction (ED)
The rates of erectile dysfunction following prostatectomy are sobering. Even under optimal conditions with bilateral nerve-sparing surgery in younger, highly motivated patients with excellent baseline function, returning to unassisted, rigid erections capable of penetrative intercourse can take anywhere from 18 to 36 months—if it happens at all.
The Reality of Non-Nerve-Sparing Surgery: If the cancer is advanced or abuts the capsule, the surgeon may have to sacrifice one or both neurovascular bundles to ensure clear surgical margins. In these cases, spontaneous, unassisted erections are virtually impossible.
Penile Rehabilitation: Patients must often embark on a rigorous, expensive, and sometimes frustrating regimen of penile rehabilitation. This involves the use of phosphodiesterase type 5 inhibitors (PDE5 inhibitors like sildenafil or tadalafil), vacuum erection devices, intraurethral suppositories, or intracavernosal injections (direct needle injections into the penis). Despite these interventions, many men never recover their pre-surgical erectile capacity, leading to chronic frustration and strained intimate relationships.
Anatomical Alterations of Organs and Orgasms
Beyond erectile failure, prostate removal permanently alters the physiological mechanics of male orgasm:
Dry Orgasms (Anejaculation): Because the prostate and the seminal vesicles (which produce the bulk of seminal fluid) are entirely removed, men no longer ejaculate fluid during climax. While sensation remains, orgasms are often described as "dry" or fundamentally altered in character.
Penile Length Reduction: Due to the removal of the prostate and the tension required to pull the bladder down to reconnect it to the urethra, many men experience a noticeable shortening of the penis (often ranging from 0.5 inches to over an inch). This occurs due to internal scarring, fibrosis, and the downward traction of the shortened urethral stump.
4. Pelvic Floor Damage and Structural Side Effects
The surgical trauma to the pelvis does not stop at the urinary and sexual systems. The entire pelvic floor undergoes a structural transformation that can manifest in several chronic physical symptoms.
Pelvic Pain and Discomfort
The pelvic floor muscles (the levator ani complex) are often cut, retracted, or traumatized during radical prostatectomy. Chronic pelvic floor muscle spasm is a frequent, under-reported complication. Patients may experience aching pain in the perineum, groin, lower abdomen, or rectum, particularly during prolonged sitting or physical exertion.
Inguinal Hernias
The disruption of the pelvic floor integrity, combined with the incisions made in the abdominal wall (whether via open laparotomy or robotic multi-port entry), significantly weakens the anatomical barriers of the lower abdomen. Consequently, the incidence of post-prostatectomy inguinal hernias rises dramatically, with many men requiring secondary hernia repair surgeries within a few years of their cancer operation.
5. Psychological and Emotional Toll
The physical downsides of prostate removal do not exist in a vacuum; they exert a profound, cascading psychological toll on the patient. Society often treats prostate cancer as the "good cancer" due to high relative survival rates, but this cultural narrative can invalidate the intense emotional suffering experienced by survivors.
Body Image and Identity Crisis
For many men, virility, urinary control, and physical autonomy are deeply intertwined with their core sense of masculinity. Facing sudden, permanent incontinence and profound sexual dysfunction can trigger a severe identity crisis. The need to wear absorbent pads, the loss of penile length, and the inability to achieve natural erections can lead to deep feelings of inadequacy, diminished self-esteem, and grief over the loss of their former physical self.
Anxiety, Depression, and Relational Strain
The chronic stress of managing leakage, coupled with the frustration of sexual rehabilitation, frequently precipitates clinical depression and anxiety. Furthermore, these changes place immense strain on romantic partnerships. Intimacy requires vulnerable communication, and when both partners must navigate the loss of spontaneous sexual expression and the management of urinary leakage, relationships can fracture without dedicated psychological counseling and couples therapy.
This concludes the first part of our comprehensive exploration into the downsides of radical prostatectomy. In the upcoming sections, we will delve into long-term oncological trade-offs, comparative analysis with alternative therapies (such as radiation and active surveillance), and strategies for navigating post-surgical rehabilitation.
Navigating Long-Term Recovery and Quality of Life
The decision to undergo a radical prostatectomy—the surgical removal of the prostate gland, typically performed to treat localized prostate cancer—marks a significant turning point in a patient's medical journey. While the initial phases of recovery involve managing surgical incisions, catheter care, and immediate post-operative restrictions, the true complexity of the procedure often reveals itself in the months and years that follow.
Understanding the full spectrum of potential downsides is essential not only for informed consent but also for preparing patients and their partners for the profound lifestyle adaptations that may be required. Beyond the immediate physical healing, long-term side effects heavily influence urinary control, sexual function, and emotional well-being.
Urinary Incontinence: Mechanisms and Management
One of the most immediate and frequently discussed long-term downsides of a prostatectomy is a temporary, and occasionally permanent, alteration in urinary function. To understand why this occurs, it helps to look at the anatomical relationship between the prostate and the urinary tract.
The prostate sits directly beneath the bladder, and the urethra—the tube that carries urine out of the body—runs straight through the center of the gland. During a radical prostatectomy, the surgeon must detach the bladder from the urethra, remove the prostate and surrounding seminal vesicles, and then meticulously reconnect (anastomose) the bladder neck directly to the remaining urethra.
This process disrupts the natural urinary sphincter mechanism, which relies in part on tissues within and immediately surrounding the prostate. While modern surgical techniques, particularly nerve-sparing and robotic-assisted approaches, have greatly improved outcomes, most patients experience a period of urinary leakage following catheter removal.
Stress Urinary Incontinence (SUI): The most common form of post-prostatectomy leakage occurs during activities that increase abdominal pressure, such as coughing, sneezing, laughing, lifting heavy objects, or standing up quickly.
Timeline for Recovery: For the majority of men, continence gradually returns over time as the surrounding pelvic floor muscles compensate for the altered anatomy. While significant improvement is often seen within three to six months, full recovery can take up to a year, and in some cases, longer.
Persistent Incontinence: A small percentage of patients experience long-term or permanent urinary leakage that does not resolve with conservative measures. This can range from minor spotting requiring a light absorbent pad to more severe incontinence that substantially impacts daily activities and social confidence.
Rehabilitation Strategies
To combat urinary incontinence, urologists and pelvic floor physical therapists strongly advocate for targeted rehabilitation:
Pelvic Floor Muscle Training (Kegel Exercises): Strengthening the levator ani muscles helps support the bladder neck and maintain closure of the urethral sphincter. Starting these exercises before surgery (pre-habilitation) and continuing them diligently afterward can significantly accelerate recovery.
Medical Interventions: In cases where conservative measures fall short after 12 months, secondary treatments are available. These include urethral bulking agents, minimally invasive male slings, or the surgical implantation of an artificial urinary sphincter, which remains the gold standard for severe, persistent SUI.
Sexual Dysfunction and Erectile Health
For sexually active men, the potential impact of a prostatectomy on erectile function and ejaculation is often one of the most concerning aspects of the procedure. The delicate bundles of nerves and blood vessels responsible for erections—known as the neurovascular bundles—run immediately alongside the prostate gland.
Even with meticulous surgical precision and nerve-sparing techniques, these microscopic nerves can experience significant trauma, stretching, or thermal injury during the dissection and removal of the prostate.
Erectile Dysfunction (ED): The ability to achieve and maintain an erection sufficient for sexual intercourse is frequently compromised post-surgery. The timeline and degree of recovery depend heavily on several baseline factors:
Age: Younger men generally recover erectile function more rapidly and successfully than older men, largely due to better baseline vascular health and nerve resiliency.
Pre-operative Function: Men who had strong erectile function prior to surgery have a much higher likelihood of regaining it.
Nerve-Sparing Status: Depending on how closely the cancer hugs the prostate, a surgeon may perform a bilateral nerve-sparing (both sides), unilateral nerve-sparing (one side), or non-nerve-sparing procedure. Non-nerve-sparing surgeries, often necessitated by aggressive cancer margins, result in permanent natural erectile dysfunction.
Loss of Ejaculation and Fertility: Because the prostate and seminal vesicles are entirely removed, the production of seminal fluid ceases. While orgasm can still be experienced (often described as "dry orgasms" or orgasmic sensations without emission), natural fertility is permanently lost. Patients desiring future biological children must pursue sperm banking prior to the procedure.
Penile Rehabilitation Protocols
To maximize the chances of natural erectile recovery, many urologists recommend a structured penile rehabilitation program. The primary goal is to maintain oxygenation and blood flow to the erectile tissues during the months when natural nocturnal erections may be absent, thereby preventing permanent structural changes like smooth muscle fibrosis and tissue shrinkage. Components of rehabilitation often include:
Oral phosphodiesterase type 5 (PDE5) inhibitors (such as sildenafil or tadalafil), taken either daily on a low-dose schedule or on-demand.
Intracorporeal injections or intraurethral suppositories if oral medications are ineffective or contraindicated.
Vacuum erection devices (VEDs) to mechanically draw blood flow into the corporal bodies.
Anatomical Changes and Physical Side Effects
Beyond urinary and sexual concerns, removing the prostate can lead to subtle yet notable changes in pelvic anatomy and physical sensations.
Penile Length Reduction: Many patients notice a visible decrease in flaccid and, occasionally, erect penile length following surgery. This phenomenon is multifactorial, resulting from a combination of internal scarring (fibrosis), lack of regular nocturnal erections, and the inward retraction of the urethral stump during the bladder-neck reconstruction. While various stretching devices and traction therapies are sometimes explored, managing expectations regarding physical changes is a vital part of pre-surgical counseling.
Inguinal Hernia Risk: The disruption of the pelvic floor and lower abdominal wall fascia during a radical prostatectomy—particularly through open or laparoscopic approaches—significantly increases the lifetime incidence of developing an inguinal hernia. Patients should remain vigilant for bulges or discomfort in the groin area and report them promptly to their physician.
Lympoedema (Rare): If pelvic lymph nodes are extensively removed during a lymph node dissection (often performed alongside radical prostatectomy for intermediate- to high-risk cancers), fluid drainage in the lower extremities can occasionally be impaired, leading to swelling in the legs or genital region, though this is less common with prostate surgery compared to other pelvic oncologic procedures.
Psychological, Emotional, and Relational Impacts
The downsides of prostate removal extend far beyond the physiological realm. The simultaneous management of urinary leakage, sexual dysfunction, and the psychological weight of a cancer diagnosis can take a heavy toll on mental health.
Anxiety and Depression: The fear of cancer recurrence, coupled with frustration over slow physical recovery, can trigger clinical anxiety or depressive symptoms. Men may struggle with changes in body image, self-esteem, and masculinity, particularly when confronting sudden erectile dysfunction or urinary pads.
Impact on Intimacy and Partnerships: Relationships often undergo a period of adjustment. Sexual intimacy requires open, vulnerable communication between partners as they navigate new ways of expressing closeness, pleasure, and affection when traditional intercourse is temporarily or permanently altered.
Support Systems: Engaging with specialized support groups, counseling services, or couples therapy can provide invaluable coping strategies. Sharing experiences with other prostate cancer survivors helps normalize the recovery process and reduces feelings of isolation.
Weighing Risks Against Oncological Benefits
When evaluating the comprehensive list of downsides associated with prostate removal—ranging from urinary incontinence and erectile dysfunction to anatomical alterations and emotional stress—it is crucial to contextualize these challenges within the broader goal of treatment. For patients with intermediate- to high-risk localized prostate cancer, a radical prostatectomy remains a potentially curative intervention that removes the primary tumor source and provides critical staging information via pathology reports.
Modern medicine continues to refine surgical instrumentation, robotic platforms, and nerve-sparing methodologies to minimize these adverse effects as much as possible. Ultimately, a thorough, individualized discussion with a multidisciplinary care team—including urologic oncologists, radiation oncologists, pelvic floor therapists, and mental health professionals—empowers patients to weigh the profound physical and emotional trade-offs against their long-term survival and oncological health goals.
Key Takeaway: While a radical prostatectomy is a powerful tool in cancer management, its long-term downsides require proactive preparation. Engaging in pre-surgical pelvic floor therapy, maintaining open communication with partners, and adhering to structured rehabilitation protocols are vital steps toward optimizing quality of life after surgery.
What specific aspect of post-prostatectomy recovery or management would you like to explore further?