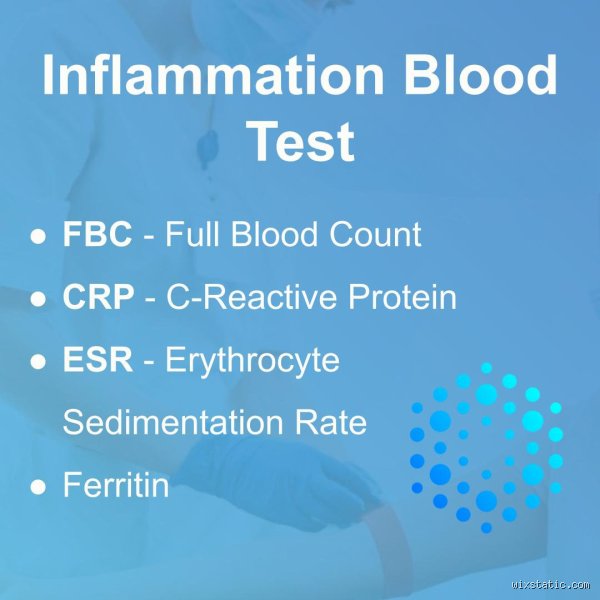
Yes, a blood test can indeed detect systemic inflammation in your body by measuring specific circulating proteins and cellular responses produced in reaction to immune triggers. While these routine tests—such as C-reactive protein and the erythrocyte sedimentation rate—readily highlight active inflammation, they act as broad warning flags rather than precise diagnostic tools, pointing only to the presence of an inflammatory state rather than its exact root cause or anatomical location.
Introduction: The Invisible Flame Within
Inflammation is one of the body’s most evolutionary refined survival mechanisms. When your immune system detects a threat—whether it is a splinter piercing your skin, a viral invader attacking your respiratory tract, or damaged tissue from a physical injury—it dispatches an intricate cascade of biochemical signals, white blood cells, and proteins to neutralize the danger and begin tissue repair. This acute inflammatory response is localized, highly regulated, and ultimately healing.
However, when this protective alarm system fails to turn off, or when it triggers inappropriately in the absence of an acute physical injury, inflammation transforms from a vital defense mechanism into a smoldering, systemic internal fire. Chronic, low-grade systemic inflammation is increasingly recognized by modern medicine as a foundational driver or exacerbating factor in a vast array of chronic conditions, ranging from cardiovascular disease and type 2 diabetes to autoimmune disorders, neurodegenerative diseases, and certain cancers.
Because chronic inflammation is often entirely invisible—lacking the classic localized signs of redness, heat, swelling, and acute pain—clinicians rely heavily on laboratory diagnostics to peer beneath the surface. Blood tests have become the gold standard for quantifying this immune activity, allowing healthcare providers to objectively measure what the patient feels only as vague fatigue, joint stiffness, or generalized malaise.
Why Measure Inflammation? The Clinical Role of Biomarkers
In clinical practice, blood tests designed to detect inflammation do not look for "inflammation" itself as a physical substance; rather, they search for biomarkers. A biomarker is a measurable biological indicator of a state or condition. In the context of inflammatory pathways, these biomarkers typically fall into two categories:
Acute-phase reactants: Proteins synthesized predominantly by the liver whose blood concentrations increase (positive acute-phase reactants) or decrease (negative acute-phase reactants) in response to inflammatory cytokines.
Cellular indicators: Changes in the absolute numbers, ratios, or characteristics of circulating blood cells—most notably white blood cells—that reflect ongoing immune activation.
The utility of these biomarkers lies in their ability to bridge the gap between subjective patient symptoms and objective physiological data. A primary care physician or specialist may order inflammatory blood panels for several distinct clinical reasons:
Screening and Risk Assessment: Evaluating an apparently healthy individual's baseline systemic inflammation to estimate long-term risks for cardiovascular events or metabolic dysfunction.
Diagnosing Suspected Inflammatory Conditions: Confirming or ruling out suspected systemic autoimmune or autoinflammatory diseases, such as rheumatoid arthritis, lupus, or inflammatory bowel disease (IBD).
Monitoring Treatment Efficacy: Tracking whether therapeutic interventions—such as biologic agents, disease-modifying antirheumatic drugs (DMARDs), lifestyle modifications, or dietary changes—are successfully lowering a patient's inflammatory burden over time.
Detecting Occult Infection or Tissue Necrosis: Identifying hidden bacterial infections, tissue ischemia, or malignancies when the physical presentation is ambiguous.
Key Blood Tests Used to Detect Inflammation
While dozens of specialized immunological assays exist in advanced research laboratories, standard clinical practice relies on a core group of accessible, highly validated blood tests. Understanding what each test measures helps demystify laboratory reports and highlights why physicians often order multiple tests simultaneously.
1. C-Reactive Protein (CRP) and High-Sensitivity CRP (hs-CRP)
C-reactive protein is perhaps the most widely recognized acute-phase reactant used in medicine. Discovered in the 1930s, CRP is a ring-shaped, pentameric protein produced primarily by hepatocytes (liver cells) in response to circulating pro-inflammatory cytokines—most notably interleukin-6 (IL-6) released by macrophages and T cells.
Standard CRP: Standard CRP assays are typically utilized to detect moderate-to-high levels of inflammation associated with acute infections, tissue trauma, or severe inflammatory flares. In the presence of acute bacterial infection or severe tissue injury, CRP levels can skyrocket from baseline values under 1.0 milligrams per liter (mg/L) to well over 100 mg/L within 24 to 48 hours.
High-Sensitivity CRP (hs-CRP): For cardiovascular risk assessment, standard CRP is insufficiently sensitive. High-sensitivity CRP assays can detect minute, low-grade fluctuations in systemic inflammation, measuring levels down to 0.1 mg/L or lower. Clinicians use hs-CRP to stratify patients into cardiovascular risk categories:
Low Risk: Under 1.0 mg/L
Average Risk: 1.0 to 3.0 mg/L
High Risk: Above 3.0 mg/L
Despite its clinical utility, CRP is notoriously nonspecific. A spike in CRP does not tell a physician where the inflammation is occurring. A severely elevated CRP could equally indicate pneumonia, a recent heart attack, a flare of Crohn's disease, or even severe dental abscesses.
2. Erythrocyte Sedimentation Rate (ESR)
Often referred to simply as the "sed rate," the Erythrocyte Sedimentation Rate is one of the oldest laboratory tests still in routine clinical use, originally developed in the early 20th century. Unlike CRP, which measures a specific circulating protein, the ESR measures the physical property of how quickly red blood cells (erythrocytes) settle to the bottom of a vertical, calibrated tube over the course of one hour, measured in millimeters per hour (mm/hr).
The mechanics behind the sed rate are rooted in basic biophysics. Under normal physiological conditions, red blood cells carry a negative electrical charge, causing them to repel one another and remain suspended evenly in plasma. However, during systemic inflammation, the liver increases production of large, asymmetric acute-phase proteins—predominantly fibrinogen, along with immunoglobulins.
When these large proteins coat the surface of red blood cells, they neutralize their negative electrical charges, causing the cells to stick together in stacks resembling rolls of coins, a phenomenon known as rouleaux formation. Because these stacked clusters are heavier and denser than individual red blood cells, they plummet through the plasma much faster, resulting in an elevated ESR.
Clinical Advantages: ESR remains a stalwart test in rheumatology. It is particularly valuable in diagnosing and monitoring classic inflammatory conditions such as polymyalgia rheumatica (PMR) and giant cell arteritis (GCA), where baseline values are often exceptionally high.
Limitations: ESR is influenced by numerous non-inflammatory variables. Age, biological sex (naturally higher in females), pregnancy, anemia, kidney disease, and technical factors (such as room temperature during testing) can all alter the sedimentation rate, making interpretation nuanced.
3. Complete Blood Count (CBC) with Differential
While CRP and ESR measure systemic biochemical responses, a Complete Blood Count (CBC) with differential examines the cellular cellular composition of the blood. White blood cells (leukocytes)—our immune system's primary frontline soldiers—provide critical clues regarding the nature of an inflammatory or infectious process.
Within the white blood cell differential, specific cell lineages point toward distinct etiologies:
Neutrophils: These are the most abundant white blood cells and act as rapid responders. An elevated neutrophil count (neutrophilia) strongly suggests an acute bacterial infection, tissue infarction, or acute physical stress/trauma.
Lymphocytes: Elevated lymphocytes (lymphocytosis) frequently point toward viral infections, though chronic lymphocytic leukemias or certain chronic inflammatory states can also alter these ratios.
Eosinophils and Basophils: Elevated counts in these cell lines often signal allergic reactions, parasitic infections, or specific hypersensitivity-related inflammatory disorders like asthma or atopic dermatitis.
Platelets: Platelets are not technically white blood cells, but they function as acute-phase reactants. Prolonged systemic inflammation stimulates thrombopoiesis (platelet production), leading to reactive thrombocytosis.
The Biological Cascade: How the Liver Responds to Signals
To truly grasp what a blood test is capturing, it helps to understand the molecular relay race that occurs inside the human body when inflammation flares. The process does not begin in the blood; it starts at the site of tissue irritation.
When cells are damaged or invaded, resident immune cells—specifically macrophages and mast cells—release potent chemical messengers known as cytokines. Among these, Interleukin-1 (IL-1), Tumor Necrosis Factor-alpha (TNF-alpha), and Interleukin-6 (IL-6) serve as master conductors of the inflammatory orchestra.
These cytokines enter the bloodstream and travel directly to the liver. The liver acts as the body's central metabolic and acute-phase response factory. Upon receiving the hormonal SOS signals from IL-6 and TNF-alpha, hepatocyte cellular machinery shifts gears, upregulating the transcription of genes responsible for manufacturing acute-phase proteins like CRP, fibrinogen, haptoglobin, and serum amyloid A, while simultaneously downregulating the production of other proteins like albumin and transferrin.
This orchestrated hepatic response is evolutionarily designed to help the organism survive trauma and infection—for instance, by helping blood clot more effectively (via fibrinogen) and assisting in pathogen clearance. However, when chronic lifestyle factors, persistent visceral adiposity (fat tissue), chronic stress, or autoimmune dysregulation keep this cytokine relay running indefinitely, the liver maintains an elevated output of these proteins month after month. Blood tests simply capture this ongoing hepatic output.
Decoding the Markers: A Closer Look at Specific Inflammation Blood Tests
When your physician suspects systemic or localized inflammation, they rarely order a single generalized test. Instead, they look at a panel of biomarkers that capture different facets of the immune response. Understanding these specific tests can help demystify your lab report and prepare you for a more informed conversation with your doctor.
1. C-Reactive Protein (CRP) and High-Sensitivity CRP (hs-CRP)
C-reactive protein is a ring-shaped protein produced by the liver in response to signaling molecules called cytokines (specifically interleukin-6) released by white blood cells during tissue damage or infection.
Standard CRP: This test typically measures larger concentrations of the protein. It is most useful for detecting acute inflammation, such as severe bacterial infections, flare-ups of inflammatory bowel disease, or major tissue trauma. Standard CRP levels can surge dramatically—sometimes by a factor of a thousand—within hours of an acute injury or infection.
High-Sensitivity CRP (hs-CRP): This version measures much lower concentrations of CRP in the bloodstream. Because minute variations can signal low-grade, chronic vascular inflammation, hs-CRP is frequently used in cardiology to assess an individual's long-term risk for cardiovascular disease and stroke. Even if you feel completely healthy, an elevated hs-CRP can indicate simmering inflammation inside your blood vessels, signaling a need for preventive lifestyle or medical adjustments.
2. Erythrocyte Sedimentation Rate (ESR or "Sed Rate")
The Erythrocyte Sedimentation Rate is one of the oldest yet still widely used blood tests for inflammation. Rather than measuring a specific chemical molecule, the ESR measures how quickly red blood cells (erythrocytes) settle to the bottom of a vertical, thin glass tube over the course of an hour.
How it works: Under normal conditions, red blood cells carry a negative electrical charge that causes them to repel one another, keeping them suspended evenly in the plasma. When inflammation is present, proteins such as fibrinogen and immunoglobulins increase in the blood. These proteins bind to red blood cells, causing them to stick together into heavy clumps (a phenomenon known as rouleaux formation). Because these clumps are heavier, they settle more rapidly to the bottom of the tube.
Clinical utility: An elevated ESR is a classic hallmark of chronic inflammatory and autoimmune conditions, such as rheumatoid arthritis, polymyalgia rheumatica, and temporal arteritis. However, like standard CRP, it is non-specific; pregnancy, anemia, kidney disease, and aging can also cause an elevated sed rate.
3. Plasma Viscosity (PV)
In some medical settings, plasma viscosity is used as an alternative or complement to the ESR. This test measures the thickness and stickiness of blood plasma compared to water. Because acute-phase proteins increase the thickness of the fluid portion of your blood, elevated plasma viscosity correlates strongly with active inflammation. Unlike the ESR, plasma viscosity is not influenced by red blood cell count or shape variations, making it a more stable measure in certain patient populations.
4. Advanced Cytokine and Specialized Panels
In specialized rheumatological, immunological, or oncological investigations, physicians may order panels looking deeper into the immune cascade:
Interleukin-6 (IL-6): A key pro-inflammatory cytokine that stimulates the liver to produce CRP.
Tumor Necrosis Factor-alpha (TNF-alpha): Involved in systemic inflammation and a primary target for biologic therapies used in autoimmune disorders like Crohn's disease and rheumatoid arthritis.
Procalcitonin: Primarily used to differentiate bacterial infections from viral infections or non-infectious inflammation, guiding antibiotic stewardship.
Interpreting Your Results: What Do the Numbers Actually Mean?
Receiving lab results containing flagged high values can cause immediate anxiety, but context is everything. To interpret an inflammation blood test accurately, healthcare providers evaluate several critical factors:
The Magnitude of the Elevation: A mild elevation in CRP or ESR often points to lifestyle factors, chronic low-grade stress, mild allergies, or a healing minor injury. Conversely, extremely high spikes usually indicate acute infection, severe tissue trauma, or an acute autoimmune flare.
Symptom Correlation: A high lab value without accompanying clinical symptoms requires a different approach than the same lab value in a patient experiencing joint pain, persistent fatigue, or unexplained weight loss.
Trend Analysis: A single snapshot in time tells only part of the story. Serial testing—repeating the blood draw weeks later—helps determine whether inflammation is worsening, resolving, or remaining chronically stable.
The Limitations of Inflammation Blood Tests
While inflammation panels are powerful clinical tools, they possess inherent limitations that every patient should understand:
They Lack Specificity: This is their most significant drawback. A positive inflammation test tells your doctor that your immune system is active, but it provides zero information about where the inflammation is located or what is causing it. An elevated CRP cannot distinguish between a sprained ankle, a urinary tract infection, gum disease, or early-stage cardiovascular plaque rupture.
High Rate of Confounding Variables: Numerous everyday factors can temporarily spike your inflammatory markers without indicating a serious medical pathology. These include:
Pregnancy and menstruation
Obesity (fat tissue itself releases pro-inflammatory cytokines)
Smoking and heavy alcohol consumption
Intense, unaccustomed physical exercise (e.g., running a marathon)
Acute lack of sleep or high psychological stress
Common medications, including birth control pills and hormone replacement therapy
Normal Results Don't Always Mean Zero Inflammation: It is entirely possible to have localized, low-grade tissue inflammation or chronic conditions where systemic markers remain stubbornly normal. Diagnosis relies on a comprehensive evaluation, not blood work alone.
From Blood Test to Clinical Diagnosis: Next Steps
If your blood work reveals unexpected or persistent inflammation, your physician will embark on a systematic diagnostic journey to uncover the root cause. This typically involves:
Detailed Medical History & Physical Examination: Reviewing your diet, sleep, stress levels, medication use, family history, and specific bodily symptoms.
Targeted Diagnostic Imaging: Depending on your symptoms, this may include ultrasound, X-rays, MRI scans, or CT scans to visualize joints, blood vessels, or internal organs.
Specific Autoimmune or Infectious Workups: If an autoimmune condition is suspected, tests like Antinuclear Antibodies (ANA), Rheumatoid Factor (RF), or anti-CCP antibodies may be ordered. If infection is suspected, cultures or targeted microbial panels will follow.
Actionable Strategies to Manage and Reduce Chronic Inflammation
Whether your blood tests revealed mild systemic inflammation or you are simply looking to optimize your long-term health, incorporating evidence-based anti-inflammatory habits into your daily routine can yield profound benefits:
Adopt an Anti-Inflammatory Dietary Pattern: Focus on whole, nutrient-dense foods rich in antioxidants and healthy fats. Emphasize leafy greens, berries, fatty fish rich in omega-3 fatty acids (such as salmon and mackerel), nuts, seeds, and extra virgin olive oil. Simultaneously, minimize ultra-processed foods, refined carbohydrates, trans fats, and excessive added sugars, which promote pro-inflammatory pathways.
Prioritize Restorative Sleep: Chronic sleep deprivation is a powerful trigger for systemic inflammation. Aim for seven to nine hours of quality sleep per night to allow your immune system and tissues to repair.
Involve Regular, Moderate Movement: Consistent physical activity helps regulate immune function and reduces visceral fat stores that secrete inflammatory chemicals. Avoid overtraining, however, as acute exhaustion can temporarily elevate inflammatory markers.
Manage Chronic Stress: Prolonged psychological stress elevates cortisol and adrenaline, which over time can dysregulate immune responses and increase systemic inflammation. Incorporate mindfulness, meditation, yoga, or deep-breathing exercises into your weekly schedule.
Conclusion
Blood tests like CRP and ESR are invaluable windows into the internal state of your immune system. While they cannot pinpoint a diagnosis on their own, they serve as crucial early warning signals, guiding physicians toward underlying infections, autoimmune disorders, or cardiovascular risks. By understanding what these tests measure—and acknowledging their limitations—you can partner more effectively with your healthcare team. Armed with this knowledge and supported by proactive lifestyle modifications, you can take meaningful control of your health, reduce chronic inflammation, and foster long-term vitality.
What specific symptoms or health goals prompted you to look into inflammation testing today?