The critical significance of scale in Vascular pathology
The primary determinant of clinical intervention, monitoring frequency, and catastrophic rupture risk is size. Yet, defining what qualifies as a "large" aneurysm is neither a static nor a universal endeavor. The threshold that classifies an aneurysm as large depends entirely on its anatomical location, the specific blood vessel involved, the underlying etiology of the disease, and patient-specific variables such as biological sex, connective tissue integrity, and comorbidities.
1. The physics of vulnerability: Laplace’s Law and Aneurysm growth
To understand why a specific millimeter## Defining the Threshold: What Constitutes a "Large" Aneurysm in Modern Vascular Medicine?
When clinicians discuss vascular pathologies, few terms carry as much immediate weight as the word "aneurysm." Defined as a localized, balloon-like bulge or dilation of a blood vessel caused by a weakening of the vessel wall, aneurysms can develop in nearly any part of the circulatory system. However, the single most critical determinant of clinical management, risk stratification, and intervention is not merely the presence of the aneurysm, but its size.
in vascular surgery and interventional cardiology, the classification of an aneurysm as "large" is neither arbitrary nor universal. Instead, "large" is a relative and highly nuanced descriptor dictated primarily by the anatomical location of the lesion, the normal baseline diameter of the affected artery, and the exponential non-linear relationship between vessel caliber and the risk of catastrophic rupture.
Understanding what is classed as a large aneurysm requires moving past a one-size-fits-all definition and examining how medical consensus defines these thresholds across different vascular beds, most notably the aorta, cerebral vasculature, and peripheral arteries.
The anatomy of Vascular expansion: Why size dictates risk
To comprehend why certain measurements cross the threshold into "large" territory, one must look at the mechanical forces acting upon blood vessel walls. According to the law of Laplace in physics, the tension (TTT) within the wall of a cylindrical vessel is directly proportional to the product of the internal pressure (PPP) and the radius (rrr) of the vessel, divided by the wall thickness (hhh):
T=P×rhT = \frac{P imes r}{h}T=hP×r
As an aneurysm expands, its radius (rrr) increases. Unless the wall thickens proportionally, which it does not, as the pathological remodeling of an aneurysm actually degrades structural proteins like elastin and collagen, the wall tension (TTT) escalates dramatically. This creates a dangerous biomechanical feedback loop: larger radius leads to higher wall stress, which causes further expansion, ultimately culminating in rupture if left unchecked.
Consequently, vascular specialists treat aneurysm diameter as a direct proxy for rupture risk. When an aneurysm crosses the boundary from "medium" to "large," the annual risk of rupture often begins to outweigh the inherent risks of surgical or endovascular repair.
Abdominal Aortic Aneurysms (AAA): The benchmark of size classification
The abdominal aorta is the most common and intensively studied site for aneurysmal disease. The normal adult abdominal aorta typically measures roughly 2.0 centimeters in diameter, though this varies slightly based on age, sex, and body surface area.
In clinical practice, abdominal aortic aneurysms are categorized using strict millimeter-based thresholds that dictate monitoring versus active intervention:
Small Aneurysm: Generally defined as a diameter between 3.0 cm and 4.0 cm. These typically require surveillance via duplex ultrasonography every 6 to 12 months.
Medium Aneurysm: Ranging from 4.0 cm to 5.4 cm. These demand closer monitoring (often every 3 to 6 months) as they approach the threshold where intervention is routinely considered.
Large Aneurysm: Classically defined as 5.5 centimeters or greater in men (and often 5.0 cm to 5.2 cm in women, given baseline anatomical differences).
An AAA measuring 5.5 cm or larger is universally recognized by major vascular societies, including the Society for Vascular Surgery (SVS) and the European Society for Vascular Surgery (ESVS), as a large aneurysm requiring prompt evaluation for elective repair (either via Open Surgical Repair [OSR] or Endovascular Aneurysm Repair [EVAR]). At this size, the five-year cumulative risk of rupture spikes significantly, often exceeding the procedural mortality risk of elective intervention.
Aneurysms that exhibit rapid expansion, defined as growth of 0.5 cm or more within a six-month period or 1.0 cm within a year, are clinically reclassified as "rapidly growing" or functionally large, regardless of their absolute diameter, triggering an urgent recommendation for treatment.
Thoracic Aortic Aneurysms (TAA): Ascending vs. Descending Thresholds
Moving upward into the chest cavity, the thoracic aorta handles immense hemodynamic forces directly ejected from the left ventricle. Thoracic Aortic Aneurysms (TAAs) are subdivided into the ascending aorta, the aortic arch, and the descending thoracic aorta. Because the native diameters and baseline tissue characteristics differ significantly between these segments, the criteria for a "large" aneurysm vary accordingly:
1. Ascending aorta and Aortic root
The normal ascending aorta typically measures between 2.5 cm and 3.5 cm. Because ascending aortic aneurysms carry a high propensity for acute aortic dissection, a catastrophic tearing of the inner layer of the wall, the threshold for intervention is more conservative than in the abdomen.
Large / Threshold for Surgery: Generally defined at 5.5 cm for individuals with sporadic (non-genetic) TAAs.
Lower Thresholds (4.5 cm to 5.0 cm): Applied to patients with underlying genetic connective tissue disorders, such as Marfan syndrome, Loeys-Dietz syndrome, or vascular Ehlers-Danlos syndrome, where the structural integrity of the extracellular matrix is profoundly compromised. Familial history of aortic dissection also lowers the definition of what constitutes a dangerous size.
2. Descending Thoracic aorta
The descending thoracic aorta shares more biomechanical similarities with the abdominal aorta.
Large Aneurysm: Typically classed at 6.0 cm or greater. Because descending thoracic repairs historically carried higher morbidity, the size threshold before accepting surgical risk is slightly higher than for the ascending aorta, though modern thoracic endovascular aortic repair (TEAR/TEVAR) has shifted these paradigms.
Cerebral (Intracranial) Aneurysms: Scale in millimeters
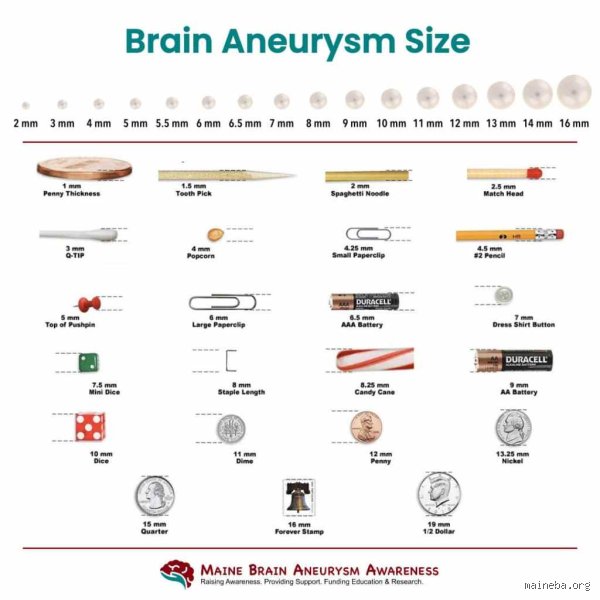
When transitioning from the high-capacity arterial conduits of the torso to the delicate microvasculature of the brain, the scale of measurement shrinks from centimeters to millimeters. Intracranial aneurysms (often colloquially called brain aneurysms) are localized dilations of arteries within the Circle of Willis and its branching vessels.
While a 5.0 cm aneurysm in the abdomen is considered large, a 5.0 mm aneurysm in the brain is a significant clinical finding. However, when defining a "large" intracranial aneurysm specifically, neurosurgeons and neurointerventionalists rely on a distinct taxonomy:
Small Intracranial Aneurysms: Less than 7 mm in diameter. The vast majority of incidental small aneurysms have a very low annual rupture risk.
Large Intracranial Aneurysms: Ranging from 10.0 mm to 24.0 mm (1.0 cm to 2.4 cm). At this scale, the risk of subarachnoid hemorrhage (SAH) increases substantially.
Giant Intracranial Aneurysms: Measuring 25.0 mm (2.5 cm) or greater. Giant aneurysms represent a distinct pathological entity; they not only carry an extraordinarily high rupture risk over a multi-year period but can also cause local mass effect, compressing adjacent cranial nerves and brain parenchyma, mimicking space-occupying tumors.
The classification of cerebral aneurysms also factors in location. For instance, posterior circulation aneurysms (such as those on the basilar artery) carry a inherently higher risk of rupture at smaller diameters compared to anterior circulation aneurysms of the same size, demonstrating that "large" is always a contextual judgment influenced by local hemodynamic stress.
Peripheral Aneurysms: Popliteal and Iliac vessels
Beyond the aorta and cerebral circulation, aneurysms can form in peripheral arteries. The two most clinically significant sites outside the central axes are the popliteal artery (behind the knee) and the iliac arteries in the pelvis.
Popliteal Artery Aneurysms (PAAs): The normal popliteal artery measures roughly 0.8 cm to 1.1 cm in diameter. Unlike aortic aneurysms, where the primary fear is rupture, the primary danger of popliteal aneurysms is thrombosis (clot formation) and distal embolization (where clots break off and block blood flow to the lower leg and foot, leading to acute limb ischemia). A popliteal artery is generally classed as an aneurysm when its diameter exceeds 1.5 to 2.0 centimeters (roughly double its normal size), and surgical evaluation is strongly recommended once it hits these dimensions, even if asymptomatic.
Iliac Artery Aneurysms: Isolated iliac aneurysms are often grouped with or secondary to AAAs. A common iliac artery diameter exceeding 2.5 cm to 3.0 cm is classed as an aneurysm and approaches the threshold for intervention due to both rupture risk and the risk of compression on adjacent pelvic structures, such as the ureters.
Diagnostic precision: Measuring size accurately
Because a difference of a few millimeters can shift a patient's management plan from watchful waiting to immediate surgical intervention, the methods used to measure aneurysm size must possess exceptional precision.
Clinicians rely on advanced cross-sectional imaging modalities to assess aneurysm dimensions across three orthogonal planes (axial, sagittal, and coronal):
Computed Tomography Angiography (CTA): The gold standard for assessing aortic and peripheral aneurysms. CTA provides sub-millimeter spatial resolution and allows for multiplanar and three-dimensional centerline reconstructions. Crucially, true diameter measurement must be performed perpendicular to the true centerline of the vessel rather than in the transverse plane of the body, as tortuous vessels can artificially inflate apparent measurements if measured improperly.
Magnetic Resonance Angiography (MRA): Often utilized for cerebral and thoracic evaluations, particularly in younger patients or those needing serial follow-ups, as it avoids ionizing radiation.
Duplex Ultrasonography: The preferred, non-invasive modality for initial screening and routine surveillance of abdominal aortic and peripheral aneurysms, offering high reproducibility when performed by certified vascular technologists.
...To fully comprehend why a specific diameter triggers the clinical designation of a "large" aneurysm, one must look beyond a simple universal ruler and examine the distinct anatomical beds in which these vascular dilatations occur. The threshold that classifies an aneurysm as large is inextricably linked to the natural history, baseline rupture risk, and physiological behavior of the specific blood vessel involved.
Anatomical Thresholds: Defining "Large" across Vascular beds
Because different arteries experience vastly different hemodynamic forces, wall compositions, and baseline pressures, the definition of a large aneurysm varies significantly depending on its anatomical location:
Abdominal Aortic Aneurysms (AAA): The normal infrarenal abdominal aorta typically measures approximately 2 cm2 ext{ cm}2 cm in diameter. An aneurysm is clinically diagnosed when the diameter reaches or exceeds 3 cm3 ext{ cm}3 cm. However, an AAA is generally classified as large when it reaches or exceeds 5.5 cm5.5 ext{ cm}5.5 cm in men (and frequently 5.0 cm5.0 ext{ cm}5.0 cm in women, due to smaller baseline body habitus and higher relative rupture risks at smaller diameters). Aneurysms exceeding 7.0 cm7.0 ext{ cm}7.0 cm are categorized as massive or very large, carrying exceptionally high annual rupture risks.
Thoracic Aortic Aneurysms (TAA): The thoracic aorta handles higher systolic velocity and direct cardiac output. For the ascending aorta and aortic arch, a diameter of 5.5 cm5.5 ext{ cm}5.5 cm is the standard threshold for surgical intervention in sporadic cases, though this drops to 4.5 to 5.0 cm4.5 ext{ to }5.0 ext{ cm}4.5 to 5.0 cm for patients with genetic connective tissue disorders such as Marfan syndrome, Loeys-Dietz syndrome, or familial thoracic aortic disease. For the descending thoracic aorta, the threshold for a large aneurysm is typically 6.0 cm6.0 ext{ cm}6.0 cm.
Intracranial (Cerebral) Aneurysms: In the delicate vasculature of the brain, the scale is entirely different. Intracranial aneurysms under 10 mm10 ext{ mm}10 mm are standard, but a cerebral aneurysm is classified as large when it measures between 10 mm10 ext{ mm}10 mm and 25 mm25 ext{ mm}25 mm (1.0 cm to 2.5 cm1.0 ext{ cm to }2.5 ext{ cm}1.0 cm to 2.5 cm). Aneurysms exceeding 25 mm25 ext{ mm}25 mm are designated as giant intracranial aneurysms. Due to the confined space of the intracranial vault and the fragility of cerebral vessels, even a "large" classification here represents a high-acuity neurosurgical challenge.
Peripheral Aneurysms (Popliteal and Femoral): Popliteal artery aneurysms, the most common peripheral aneurysms, are typically considered large when they exceed 2.0 cm2.0 ext{ cm}2.0 cm (normal being ≈1 cm\approx 1 ext{ cm}≈1 cm). Unlike aortic aneurysms where rupture is the primary feared complication, large peripheral aneurysms pose an equally severe threat of acute limb ischemia secondary to thrombosis or thromboembolism.
The biomechanics of size: Laplace's Law and wall stress
The reason size dictates classification and clinical urgency is rooted in basic physics, specifically the Law of Laplace. For a cylindrical vessel, wall tension (TTT) is directly proportional to the intravascular pressure (PPP) multiplied by the radius (rrr), divided by the wall thickness (hhh):
T=P×rhT = \frac{P imes r}{h}T=hP×r
As an aneurysm expands, its radius (rrr) increases. Unless the wall thickens proportionally, which it does not, as chronic expansion instead leads to extracellular matrix degradation, smooth muscle cell apoptosis, and collagen thinning (hhh), the wall tension escalates exponentially.
When a vessel crosses the boundary into the "large" category, it enters a non-linear phase of biomechanical stress. The structural proteins (elastin and collagen) within the medial layer of the arterial wall can no longer bear the load. At this critical juncture, the risk of rupture begins to rise steeply year-over-year, often eclipsing the procedural risks associated with elective surgical or endovascular repair.
Diagnostic precision: Measuring Aneurysms accurately
Classifying an aneurysm as large requires high-precision imaging modalities. Relying on outdated or inconsistent imaging can misclassify a high-risk lesion. Standard diagnostic pathways include:
Computed Tomography Angiography (CTA): The gold standard for aortic and peripheral aneurysms. CTA provides isotropic 3D volumetric datasets that allow vascular surgeons to measure true maximum transverse diameters perpendicular to the centerline of blood flow, avoiding oblique measurements that artificially inflate size estimates.
Magnetic Resonance Angiography (MRA): Frequently utilized for intracranial aneurysms and younger patients requiring serial surveillance without ionizing radiation exposure.
Duplex Ultrasonography: Highly effective for serial surveillance of abdominal aortic and popliteal aneurysms, offering real-time dimensional tracking without contrast agents.
Specialists also monitor growth rate alongside absolute size. An aneurysm that expands by 0.5 cm0.5 ext{ cm}0.5 cm or more within a six-month window is considered rapidly expanding, even if it has not yet crossed the absolute 5.5 cm5.5 ext{ cm}5.5 cm cutoff. Rapid expansion functions as a functional equivalent to a "large" classification, frequently triggering an expedited recommendation for intervention.
Clinical management paradigms for Large Aneurysms
Once an aneurysm is classified as large, the clinical strategy shifts decisively from conservative surveillance (watchful waiting with blood pressure optimization and smoking cessation) to active intervention.
Endovascular Repair: Procedures such as EVAR (Endovascular Aneurysm Repair) for abdominal aortas, TEVAR (Thoracic Endovascular Aortic Repair) for thoracic segments, or endovascular coiling and flow diversion for intracranial aneurysms allow specialists to exclude the aneurysmal sac from systemic blood pressure via minimally invasive catheter-based delivery systems.
Open Surgical Reconstruction: For patients with unfavorable anatomy, hostile neck morphology, or connective tissue disorders, open surgical resection and graft placement remain the durable benchmark for definitive treatment.
Conclusion
Classifying an aneurysm as "large" is not merely a semantic label; it is a critical clinical inflection point. It signifies that the physical forces acting upon the vessel wall have surpassed the biological limits of arterial integrity, shifting the therapeutic calculus from conservative observation to definitive intervention. Through rigorous imaging, adherence to evidence-based anatomical size thresholds, and an understanding of underlying biomechanical stress, modern vascular medicine successfully mitigates the catastrophic risks associated with these complex dilatations.