The evolving timeline: When do we actually outgrow the speculum?
For generations, the annual pelvic exam was an unquestioned ritual of womanhood, a yearly milestone passed down from mothers to daughters like a dubious biological inheritance. Then the guidelines changed. Major medical bodies, including the U.S. Preventive Services Task Force (USPSTF) and the American Cancer Society, looked at the data and realized that over-screening was causing more anxiety and unnecessary procedures than actual lifesaving interventions. Cervical cancer develops slowly, often taking 10 to 20 years to progress from an initial human papillomavirus (HPV) infection to a malignant tumor, which explains why the risk dynamic shifts so dramatically as we collect gray hairs.
The golden rule of 65 and its strict prerequisites
So, what exactly constitutes an acceptable exit ticket from the screening pool? The guidelines are rigid: you can stop at 65 only if you have had three consecutive negative Pap tests or two consecutive negative co-tests (Pap plus HPV screening) within the past 10 years, with the most recent test occurring within 5 years. But let's be honest, who actually keeps a meticulous spreadsheet of their gynecological history spanning the Clinton, Bush, and Obama administrations? If you changed health insurance providers, moved across state lines to a city like Chicago or Boston, or your old doctor retired to Florida, those records might be buried in a digital abyss. And if you haven't been adequately screened in your 50s, stopping at 65 is downright dangerous.
The hysterectomy loophole and its frequent misunderstandings
Here is where things get complicated for a massive subset of the population. If you underwent a total hysterectomy for a non-cancerous condition—such as severe uterine fibroids or debilitating endometriosis—you genuinely no longer need a Pap smear, regardless of your current age, because your cervix was removed along with your uterus. The catch: many women mistake a partial hysterectomy for a total one. If your surgeon left the cervix intact, you are still very much in the running for cervical dysplasia, meaning the standard age-based rules still apply to your anatomy. I find it astonishing how often patients are left in the dark about the exact blueprint of their own internal organs after a major surgery.
The biological math: Why the threshold sits exactly where it does
To understand the rationale behind the age 65 cutoff, we have to look at the statistical trajectory of human papillomavirus, the culprit behind virtually all cervical malignancies. HPV is an incredibly common sexually transmitted infection that most people contract in their late teens or twenties. In young women, the immune system acts like a hyper-efficient bouncer, clearing the virus silently within a couple of years. But as the decades roll by, the immune system loses its youthful edge, a biological reality that matters most when it comes to persistent viral strains.
The danger of persistent infections and the Late-Onset spike
When an HPV infection manages to evade the immune system and camp out in the cervical tissue for twenty or thirty years, it silently alters the cellular DNA. Statistics from the National Cancer Institute reveal that roughly 20 percent of new cervical cancer cases are diagnosed in women over the age of 65. Think about that for a second. Why are we stopping screenings at the exact demographic threshold where a fifth of all cases emerge? The trouble is that these senior diagnoses usually represent long-festering, indolent infections rather than brand-new exposures, meaning the window to catch them was actually in the decade leading up to retirement.
Immune senescence and the re-emergence myth
There is an ongoing, fierce debate in oncological circles about whether a dormant HPV infection from a woman's youth can suddenly reawaken during her sixties due to age-related immune decline. Some virologists argue that the virus behaves like shingles, waiting for a period of profound physical or emotional stress to break out of latency, while others maintain that late-stage diagnoses are simply the result of inadequate screening in middle age. Regardless of which camp is right, the clinical outcome is identical: older women who develop cervical cancer are far more likely to be diagnosed at an advanced, less treatable stage than their younger counterparts.
The blind spots of public health: Who is left unprotected?
Public health guidelines are designed for populations, not individuals. They are calculated mathematical equations balancing the financial and physical cost of screening millions of people against the number of lives saved. But when you are the person sitting on the examination table covered in a paper sheet, population aesthetics matter very little. The current guidelines harbor massive blind spots that fail specific groups of older women, making the universal age limit a highly flawed benchmark.
The sexual renaissance of the golden years
The architects of our screening guidelines seem to operate under the bizarre, puritanical assumption that women suddenly become asexual monastics the moment they qualify for Medicare. With the rise of online dating apps and vibrant retirement communities from Arizona to Florida, older adults are experiencing a profound sexual renaissance. A 67-year-old divorcee entering a new relationship faces the exact same biological exposure to new HPV strains as a 22-year-old college student. Yet, under the current framework, the grandmother navigating the modern dating pool is told she no longer needs a Pap, leaving her vulnerable to new infections that could quietly transform into malignancy over the next decade.
Disparities, geography, and the historical screening gap
We cannot discuss medical guidelines without acknowledging who gets left behind in the gears of the healthcare machine. According to data published in the journal Cancer, Black and Hispanic women in the United States are significantly more likely to die from cervical cancer than white women, a disparity that widens in older demographics. A woman living in a rural medical desert in Appalachia may not have had access to regular co-testing during her prime years. So cutoffs based on the assumption of a perfect, uninterrupted lifetime of medical care are fundamentally classist and epidemiologically reckless.
Modern alternatives: Is the Pap smear becoming obsolete for older women?
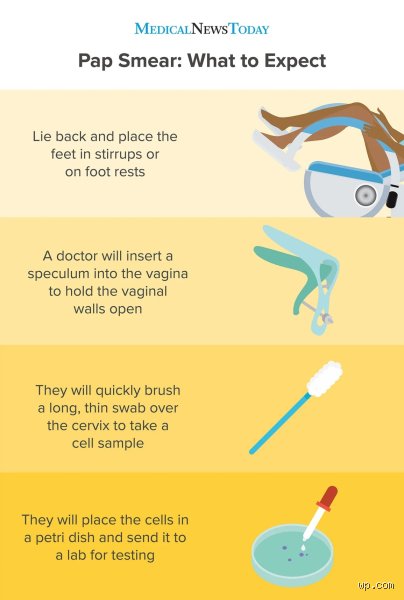
The traditional Pap smear, which involves scraping cells from the cervix and looking at them under a microscope to spot physical mutations, is no longer the only game in town. In fact, for older women looking to confirm whether they can safely exit the screening loop, newer technological methods offer much greater diagnostic certainty.
Primary HPV testing vs. Traditional cytology
The biggest shift in modern gynecology is the transition to primary HPV screening. Instead of looking for damaged cells, this molecular test searches directly for the DNA or RNA of high-risk viral strains, particularly HPV 16 and 18. It is a far more sensitive tool for older women. If you are 64 years old and your primary HPV test comes back negative, your statistical risk of developing cervical cancer over the next ten years is practically zero, providing a level of reassurance that a standard Pap smear simply cannot match. As a result, many progressive physicians are abandoning the traditional smear entirely for their older patients, using the molecular test as the definitive exit interview for the cervix.
Common mistakes and dangerous misconceptions
The "I haven't had sex in years" pass
Many mature women falsely believe that marital status changes or long periods of sexual abstinence act as a shield against cervical cancer. The problem is that the Human Papillomavirus (HPV) behaves like a microscopic sleeper cell. You might have contracted a high-risk strain decades ago, which then lay completely dormant while your immune system kept it in check. But as your biology undergoes age-related changes, that latent viral load can suddenly awaken. Thinking you are exempt just because your bedroom has been quiet is an incredibly risky gamble. Because the virus does not follow a strict chronological schedule, skipping your regular checks because of a dry spell can lead to delayed diagnoses.
Assuming menopause means automatic retirement from screening
Another widespread blunder involves conflating the end of menstruation with the end of oncological vulnerability. Your ovaries stepping down from their reproductive duties has absolutely nothing to do with the cellular integrity of your cervix. The cessation of your monthly cycle changes your hormonal landscape, yet the tissue at the cervical transformation zone remains susceptible to malignant transformations. The age at which a woman no longer needs a Pap smear is not dictated by hot flashes or the arrival of postmenopausal life. Some patients even assume that a routine pelvic examination or a manual bimanual checkup automatically includes a cellular scrape, which is an assumption that leaves them entirely unprotected while they believe they are perfectly safe.
The hidden factor: Immunosenescence and your cervix
Why aging immunity changes the screening calculus
Medical discussions rarely address the phenomenon of immunosenescence, the gradual fading of our immune defense mechanisms as the decades accumulate. When you turn sixty-five, your T-cells lose their youthful agility, meaning your body struggles to suppress persistent HPV infections that it previously managed with ease. This biological decline is exactly why stopping your screenings must be an intentional, data-driven decision rather than a random birthday milestone. If you have a brand-new partner in your sixties, your aging immune system faces a double jeopardy: higher exposure to fresh viral strains and a diminished capacity to clear them.
Expert guidance on calculating your exit strategy
The problem is that freedom from the speculum requires a flawless track record. Before you completely abandon the examination table, your physician must verify that you meet the strict criteria for cessation. This means having either three consecutive negative Pap results or two consecutive negative co-tests within the preceding ten years, with the most recent evaluation occurring within the last five years. (And no, self-testing kits you find online do not count toward this official tally). If your medical records are a chaotic patchwork of missing files or sporadic appointments, you simply cannot walk away yet.
Frequently asked questions
At what age does a woman no longer need a Pap test if she has had a total hysterectomy?
If your surgical procedure involved the complete removal of both your uterus and your cervix for benign reasons like uterine fibroids, you can generally stop these evaluations immediately regardless of your current age. The clinical paradigm shifts entirely because the target tissue responsible for cervical carcinoma is no longer present in your body. However, a crucial exception applies to individuals whose hysterectomy was performed as a direct treatment for high-grade cervical dysplasia or actual malignancy, which explains why these high-risk patients must continue tracking their vaginal vault health for twenty years post-surgery. Data from gynecological registries shows that cellular abnormalities can still emerge in the remaining vaginal tissue, making ongoing surveillance a necessity for this specific cohort.Can I request to continue screening after 65 if I want the extra peace of mind?
You possess the absolute right to advocate for continued testing, though insurance coverage might become a financial hurdle once you pass the standard age threshold. Major medical guidelines, including those from the American Cancer Society, note that women over sixty-five account for roughly twenty percent of new cervical cancer diagnoses, often because they slipped through the cracks of systematic screening in their younger years. If you have a dynamic dating life or a medical condition that requires immunosuppressive medications, your personal risk profile looks vastly different from institutional averages. Talk frankly with your clinician about your lifestyle because a blanket age limit cannot account for individual human behavior.What happens if I test positive for HPV during my very final scheduled screening?
A positive viral marker at age sixty-four completely derails your exit strategy and resets your clinical timeline. You will not be permitted to graduate from regular surveillance because an active infection at this stage carries a significantly higher risk of rapid progression due to your body's declining viral clearance rates. Your practitioner will initiate a closer management protocol, which often includes a colposcopy or repeated testing at twelve-month intervals instead of the usual five-year gap. Statistics reveal that elderly patients diagnosed with cervical malignancies frequently present with advanced-stage tumors, a tragic reality that underscores why we must never ignore a positive signal just because you are near the finish line.An honest look at your final screening milestone
Age boundaries in medicine are useful benchmarks, but they are never absolute truths. The age at which a woman no longer needs a Pap test should be viewed as a hard-earned biological graduation, not a bureaucratic chore that you simply drop out of boredom. We must stop treating the age of sixty-five as a magical shield that automatically repels oncological threats. The actual data shows that a well-screened population can safely stop, but a poorly-screened individual is walking into a dangerous trap by abandoning surveillance. Your individual sexual history, immune vigor, and medical paperwork should dictate this transition. Do not let administrative convenience dictate your cellular safety. Work closely with an experienced gynecologist to ensure your exit from the screening pool is backed by concrete, negative lab results.