Which country needs more dentists? A global analysis of Oral Health disparities
Understanding where the greatest need lies requires looking past raw headcounts and examining dentist-to-population densities, healthcare funding models, regional distribution gaps, and the profound socioeconomic barriers that leave millions of people with untreated oral disease.
The global divide: Developing nations and the crisis of basic access
When evaluating absolute necessity and the severity of untreated conditions, low- and middle-income countries in regions such as Sub-Saharan Africa, South Asia, and parts of Southeast Asia bear the heaviest burden. In these regions, the shortage of dental professionals is not merely a matter of long waiting lists or cosmetic inconvenience; it is a public health crisis defined by chronic pain, systemic infections, and a total lack of preventative infrastructure.
Consider the stark contrast in workforce density. While high-income nations often maintain dentist-to-population ratios ranging from 50 to over 80 dentists per 100,000 residents, many developing countries operate at a fraction of that capacity. In nations like India, parts of Southeast Asia, and rural pockets across the globe, the ratio can plummet to fewer than 10 dentists per 100,000 people—effectively translating to a single practitioner for every 10,000 citizens.
Compounding this numerical deficit is the unequal geographic distribution of available professionals. Dentists, much like physicians, tend to concentrate in affluent urban centers where private-pay practices are economically viable. Rural and remote populations are consequently left in what can accurately be described as "dental deserts." In these areas, basic procedures like fillings, scaling, or safe extractions are luxury services. Without access to preventative care or education, minor tooth decay frequently escalates into severe oral pathology, forcing individuals to rely on emergency hospital visits or, in worst-case scenarios, endure unmanaged agony.
Developed nations under strain: The paradox of wealth and shortages
While developing nations struggle with foundational infrastructure, advanced economies face a different yet equally pressing crisis characterized by workforce burnout, insurance constraints, and crumbling public dental systems. Even in wealthy nations where the aggregate number of licensed dentists appears adequate on paper, access to care remains severely restricted for large segments of the population.
1. The United Kingdom and the "NHS Dental desert"
Few nations illustrate the modern industrial dental crisis quite as vividly as the United Kingdom. Driven by structural dissatisfaction with the National Health Service (NHS) dental contract framework, the UK has experienced an exodus of practitioners moving away from public-sector work.
Recent analyses highlight that millions of adults across England experience unmet NHS dental needs, with vast regional disparities. Regions in the South West and rural counties suffer from acute vacancy rates where local practices are entirely closed to new NHS patients. The mismatch between soaring public demand and a dwindling base of participating NHS dentists has created a tier-based system where comprehensive care is increasingly restricted to those who can afford private fees, leaving lower-income households structurally underserved.
2. Australia and regional imbalances
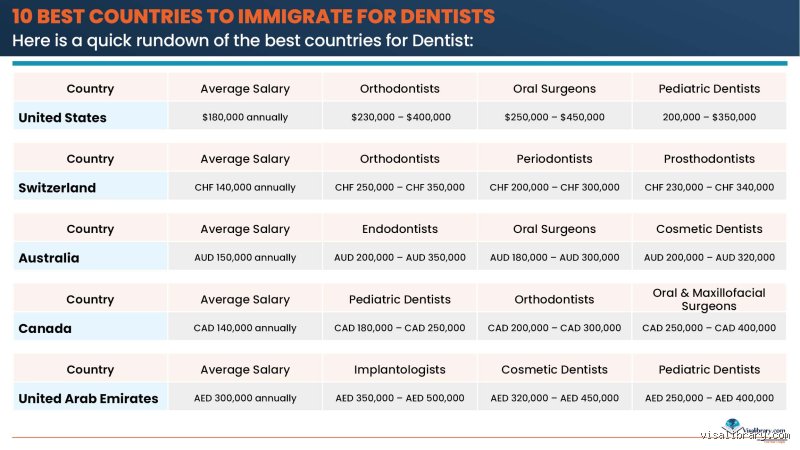
Similarly, Australia boasts a high-performing private dental sector, yet faces chronic shortages in regional, rural, and remote territories. Because major dental treatments and general preventative maintenance are largely excluded from universal Medicare coverage, out-of-pocket costs remain a significant deterrent. The Australian Government and state health authorities continuously list dental practitioners as core skill-shortage occupations, relying heavily on international recruitment and sponsored migration pathways to keep regional clinics staffed.
3. North America: Financial barriers and capped benefits
In the United States and Canada, the primary driver of unmet dental need is financial architecture rather than a literal absence of dental schools. US dental education produces highly skilled clinicians, but dental insurance models frequently feature low annual maximum caps (often remaining stagnant at $1,000 to $2,000 for decades) that fail to cover major restorative or preventative procedures. Consequently, low-income families, elderly populations, and uninsured workers routinely skip routine check-ups, translating into high rates of untreated decay despite the country's high dentist density in affluent metropolitan suburbs.
Why workforce metrics can be misleading
When international health organizations evaluate dentist shortages, relying solely on national averages can obscure localized realities. A country may report a healthy national ratio of 70 dentists per 100,000 residents, yet 80% of those professionals may practice within two major metropolitan hubs, catering primarily to high-end cosmetic and elective procedures.
True workforce adequacy requires analyzing three intersecting variables:
Active Clinical Participation: The number of licensed professionals actively practicing clinical dentistry versus those in administration, research, or retirement.
Public vs. Private Distribution: The proportion of dentists willing to accept public insurance or government-subsidized tariffs versus private-pay models.
Preventative Capacity: Whether the workforce is large enough to shift from reactive treatments (extractions and emergency surgery) to proactive public health education and early intervention.
Moving forward: Addressing the global gap
Solving the international deficit of dental care requires multifaceted policy interventions tailored to regional needs. In developing nations, international health initiatives and governmental investments must focus on training mid-level dental therapists and expanding mobile clinic networks to reach isolated rural populations. In developed nations experiencing public-sector retention crises—such as the UK, overhauling reimbursement models, reducing administrative burdens, and incentivizing practitioners to remain within public healthcare frameworks are essential steps toward closing the access gap.
Whether measured by the vast populations of rural developing regions lacking basic hygiene tools or the millions of citizens in wealthy nations priced out of local clinics, the global demand for expanded, equitable dental care has never been more urgent.
The severity of regional deficits: Sub-Saharan Africa and South Asia
While macroeconomic discussions often highlight high-income nations grappling with regional shortages, such as dental deserts in rural parts of the United States, the United Kingdom, or continental Europe, the true epicenter of the global dental crisis lies in low- and middle-income regions. According to World Health Organization (WHO) and global health workforce analyses, Sub-Saharan Africa bears the most acute deficit of dental professionals on the planet.
In nations like Nigeria, Ethiopia, and the Democratic Republic of the Congo, population-to-dentist ratios can skyrocket to extremes exceeding 40,000:1, and in some hyper-rural sectors, nearly one million residents rely on a single clinical dental provider. To contextualize this figure against the global average or high-income standards, where ratios frequently hover between 1,000:1 and 2,000:1, the scale of unmet need becomes staggering. Millions of individuals in these regions live with chronic, untreated dental pain, systemic oral infections, and severe nutritional complications stemming from basic tooth decay that has no access to primary care intervention.
South Asia presents a contrasting yet similarly challenging dynamic. While countries like India produce a high total volume of dental graduates annually, structural maldistribution creates massive internal disparities. Urban centers may approach adequate or even saturated dentist-to-population ratios, whereas vast rural hinterlands remain heavily underserved. Consequently, national aggregates can mask deep internal pockets of severe workforce scarcity.
Macro-Level drivers of the global dentist shortage
The discrepancy in dental workforce distribution is governed by several interconnected economic, educational, and systemic barriers:
Underfunded Educational Infrastructure: Establishing dental schools requires immense capital investment for specialized simulation labs, advanced imaging tech, chair units, and consumable materials. Developing nations frequently lack the public budgets required to scale up training slots.
The "Brain Drain" Phenomenon: Highly skilled dental professionals trained in developing nations frequently migrate to high-income economies (such as the US, Canada, the UK, and Gulf States) seeking better remuneration and modern technological infrastructure. This exacerbates shortages in their countries of origin.
Out-of-Pocket Cost Structures: In many developing health systems, dental care is entirely privatized and omitted from universal health coverage (UHC) packages. Because impoverished populations cannot afford private fees, demand remains latent rather than financially expressed, masking the true need for practitioners.
Geographic Mal-distribution: Even within developed economies experiencing nominal workforce stability, dentists overwhelmingly concentrate in affluent metropolitan environments, leaving agricultural and remote communities starved of continuous oral healthcare.
Strategic solutions for sustainable workforce growth
Closing the global dental deficit requires moving beyond traditional models of high-cost, urban-centric dental practice. Public health experts advocate for a multi-pronged policy approach:
Expanding Mid-Level Dental Providers: Deploying trained dental therapists, hygienists, and mid-level practitioners can dramatically extend the reach of primary preventative care into remote areas at a fraction of the training cost of a full specialist dentist.
Integrating Oral Health into Universal Health Coverage (UHC): Treating oral disease as an optional cosmetic luxury perpetuates global inequities. Incorporating basic restorative and preventative treatments into national health packages creates sustainable demand and employment stability for practitioners in underserved regions.
Mandatory Rural Service Frameworks and Retention Incentives: Governments can implement targeted loan forgiveness programs, housing subsidies, and career advancement paths specifically conditioned on practicing for a set duration in high-need rural "dental deserts."
Answering "which country needs more dentists" points to a global map of systemic health inequality. While Sub-Saharan Africa and South Asia experience the most catastrophic numerical shortages, nearly every nation faces localized distribution failures that leave vulnerable populations exposed to preventable oral disease. Resolving this crisis demands coordinated international investment in localized training, task-shifting models, and structural healthcare reform.