Understanding the pancreas and the mystery of intermittent Abdominal discomfort
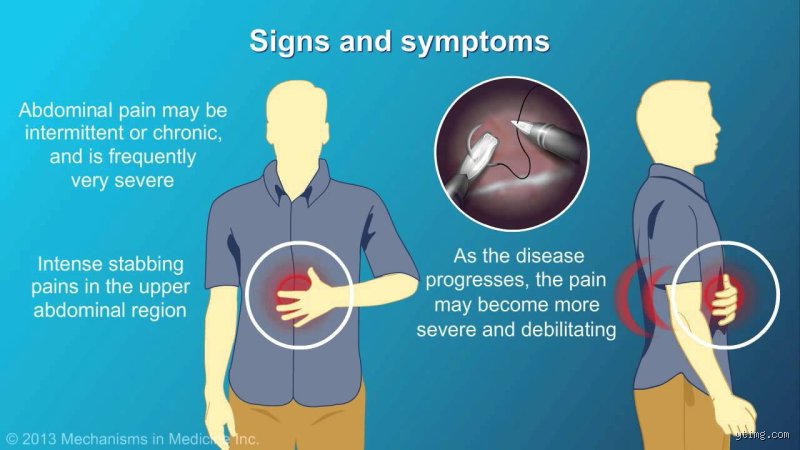
Unlike a sharp scrape on the skin or a broken bone that causes localized, constant agony, visceral pain originating from deep-seated abdominal organs like the pancreas rarely follows a simple, straightforward trajectory. Visceral sensory fibers are structurally distinct from somatic nerves; they are distributed more sparsely and tend to map poorly to exact locations in the brain. Consequently, discomfort tied to pancreatic stress often presents as a deep, dull ache, a heavy pressure, or a burning sensation in the upper central abdomen, frequently referred to clinically as the epigastric region. What puzzles many individuals is the intermittent nature of these episodes: a person might experience acute discomfort following certain meals or periods of high stress, only to feel completely normal for days, weeks, or even months afterward. This episodic pattern can mask underlying chronic processes, leading people to attribute their symptoms to routine indigestion, acid reflux, or muscle strain, while a deeper physiological narrative unfolds quietly inside the retroperitoneal space.
To comprehensively examine what drives this intermittent pattern, medical professionals look closely at how the pancreas handles its own powerful secretions. Under normal circumstances, digestive enzymes manufactured by pancreatic acinar cells remain in an inactive precursor state as they travel through a branching system of tiny tubes known as pancreatic ducts. These ducts eventually merge into the main pancreatic duct, safely delivering the enzymes into the duodenum (the first part of the small intestine), where they activate to digest food. However, if anything disrupts this smooth transit, such as micro-obstructions, localized swelling, structural narrowing (strictures), or transient blockages caused by small biliary sediments, these enzymes can become trapped prematurely within the glandular architecture. When trapped, they can initiate a localized process of auto-digestion and irritation, triggering a cascade of inflammatory responses. As the tissue mounts an immune defense, localized swelling occurs, stretching the sensitive capsule that envelops the pancreas and stimulating visceral pain receptors. Once the minor obstruction clears or the localized inflammation temporarily recedes, the physical pressure subsides, explaining why the discomfort appears to vanish entirely, only to return unpredictably when predisposing triggers re-emerge.
The spectrum of chronic and recurrent Pancreatic irritation
When evaluating intermittent upper abdominal pain, medical science frequently categorizes potential triggers into distinct physiological pathways, ranging from recurrent acute flare-ups to early-stage chronic inflammatory conditions. Chronic pancreatitis, for instance, does not always announce itself with unremitting, debilitating agony from day one. In many cases, it begins insidiously as a smoldering, intermittent process. Over time, repeated cellular injury leads to progressive fibrosis, the accumulation of fibrous scar tissue, which gradually replaces healthy, functional pancreatic parenchyma. This structural remodeling can distort the internal ductal system, creating localized bottlenecks where pancreatic juice pools under pressure. Every time dietary habits, metabolic shifts, or environmental exposures place a sudden surge in demand on these compromised pathways, a temporary spike in internal pressure occurs, culminating in a transient wave of sharp or gnawing pain that frequently radiates straight through to the back.
Another critical element in understanding intermittent pancreatic discomfort involves the biliary tree, the intricate network of drainage channels shared by the liver, gallbladder, and pancreas. The main pancreatic duct often joins the common bile duct just before emptying into the small intestine at a muscular valve called the sphincter of Oddi. If a small gallstone, biliary sludge, or functional spasm of the sphincter of Oddi intermittently temporarily blocks this shared junction, backpressure builds simultaneously within both the biliary system and the pancreas. This transient bottleneck can induce a temporary rise in pancreatic ductal pressure, setting off a wave of sharp, colicky upper abdominal pain that mimics classic gallbladder attacks but carries distinct pancreatic implications. Because these tiny crystalline deposits or functional spasms can shift, pass, or relax on their own, the resulting pain profile is inherently intermittent, appearing abruptly and disappearing just as mysteriously once normal flow is restored.
Lifestyle factors, systemic metabolic environments, and genetic predispositions play profound roles in shaping whether an individual experiences sporadic pancreatic distress. Persistent systemic exposures, such as chronic tobacco use or regular high-volume alcohol consumption, exert cumulative oxidative stress on pancreatic cells, making them hypersensitive to minor physiological provocations. Even in individuals who completely avoid alcohol, rare genetic mutations affecting proteins like cystic fibrosis transmembrane conductance regulator (CFTR) or serine protease inhibitor Kazal type 1 (SPINK1) can subtly alter the fluidity of pancreatic secretions, predisposing the ducts to microscopic plugging and recurrent, low-grade inflammatory episodes. Recognizing these diverse contributors highlights why a symptom as seemingly straightforward as intermittent upper abdominal discomfort requires a careful, highly nuanced look at everything from anatomical architecture and lifestyle patterns to systemic metabolic health.
Medical Disclaimer: The following information is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Because intermittent abdominal pain can stem from serious underlying conditions, including recurrent acute or chronic pancreatitis, anyone experiencing persistent or recurring pain in the upper abdomen should consult a qualified healthcare provider or gastroenterologist for a proper evaluation.
Navigating the diagnostic journey
When upper abdominal discomfort comes and goes, identifying the underlying trigger can be clinically challenging. Unlike acute pancreatitis, which typically presents with a sudden, severe, and unrelenting epigastric pain that often radiates straight through to the back, intermittent or smoldering pancreatic pain can mimic a variety of other gastrointestinal and biliary disorders.
To determine whether the pancreas is truly the source of intermittent pain, clinicians rely on a comprehensive diagnostic pathway that combines detailed clinical history, laboratory testing, and advanced imaging modalities.
1. Laboratory Evaluations
During or immediately following an episode of pain, specific blood tests can offer critical clues:
Serum Lipase and Amylase: These digestive enzymes are typically elevated during acute inflammation of the pancreas. However, in cases of chronic or mild intermittent pancreatitis, enzyme levels can sometimes return to normal relatively quickly, meaning a normal test does not automatically rule out pancreatic involvement.
Liver Function Tests (LFTs): Bilirubin, alkaline phosphatase, and transaminases are checked to evaluate for biliary tract obstruction, such as gallstones lodged in the common bile duct or ampulla of Vater, which frequently trigger pancreatic duct irritation.
Lipid Panel and Calcium Levels: Hypertriglyceridemia (excessively high triglycerides) and hypercalcemia are both well-documented metabolic triggers for recurrent pancreatic inflammation.
HbA1c and Fasting Glucose: Assessing long-term blood sugar regulation helps determine if exocrine pancreatic insufficiency is beginning to impact endocrine function (pancreatic diabetes).
2. Advanced imaging and visualization
Because the pancreas lies deep within the retroperitoneum, surrounded by the stomach, duodenum, and transverse colon, standard physical exams can easily miss subtle abnormalities. Imaging allows physicians to visualize the ductal architecture, parenchyma, and surrounding structures:
Abdominal Ultrasound: Often the first-line imaging tool to screen for gallstones, sludge, or dilation of the common bile duct.
Computed Tomography (CT) Scan: Contrast-enhanced CT imaging provides detailed cross-sectional views of the pancreatic parenchyma, helping to identify calcifications, fluid collections, pseudocysts, or structural atrophy indicative of chronic pancreatitis.
Magnetic Resonance Cholangiopancreatography (MRCP): A non-invasive MRI technique specialized for visualizing the pancreatic and bile ducts without the need for ionizing radiation or invasive instrumentation.
Endoscopic Ultrasound (EUS): Considered a gold standard for high-resolution evaluation of the pancreas, EUS involves passing a specialized endoscope down the esophagus and stomach to view the gland from centimeters away, allowing for fine-needle tissue sampling if a mass or autoimmune etiology is suspected.
Management and Lifestyle considerations
Once a definitive diagnosis is established, managing intermittent pancreatic pain focuses on addressing the root cause, preventing recurrent injury, and preserving long-term digestive and endocrine function.
+------------------------------------------------------------+
| Core Pillars of Management |
+------------------------------------------------------------+
| 1. Root Cause Resolution (e.g., Cholecystectomy for |
| gallstones, metabolic optimization for triglycerides) |
| 2. Dietary Modifications (Low-fat, frequent small meals, |
| complete cessation of alcohol and tobacco) |
| 3. Pain Modulation & Enzyme Replacement (PERT for |
| exocrine insufficiency, multimodal analgesia) |
+------------------------------------------------------------+
Addressing underlying triggers
Biliary Disease: If gallstones or biliary sludge are identified as the inciting factor, a cholecystectomy (surgical removal of the gallbladder) is frequently recommended to prevent future episodes of gallstone pancreatitis.
Lifestyle Modifications: Complete cessation of alcohol consumption is paramount, as alcohol is a major driver of toxic-metabolic pancreatic injury. Similarly, tobacco cessation is critical, as smoking synergistically accelerates the progression of chronic pancreatic damage.
Dietary Adjustments: Adopting a low-fat diet and eating smaller, more frequent meals can reduce the secretory workload on the pancreas, minimizing postprandial pain flare-ups.
Enzyme Supplementation: For individuals experiencing malabsorption or chronic pain related to inadequate digestive enzyme secretion, Pancreatic Enzyme Replacement Therapy (PERT) may be prescribed to support digestion and reduce pancreatic stimulation.
Summary and next steps
Intermittent pain in the region of the pancreas warrants thorough medical evaluation rather than dismissal as routine indigestion. Because symptoms can overlap significantly with peptic ulcer disease, gastritis, biliary colic, and other intra-abdominal conditions, partnering with a gastroenterologist is essential for obtaining an accurate diagnosis and tailored treatment plan.