Understanding the Longevity of Permanent Male Sterilization
The decision to undergo a vasectomy represents a monumental milestone in family planning, offering a definitive, highly reliable form of permanent contraception that millions of men rely on for lifelong peace of mind. For decades, individuals who chose this elective urological procedure did so with the reassuring belief that once the healing process was complete and a post-vasectomy semen analysis confirmed azoospermia, their reproductive chapter was permanently closed. Yet, as the calendar marches forward and patients who underwent the procedure twenty, twenty-five, or even thirty years ago enter new life stages—sometimes starting second families or simply seeking absolute certainty regarding their long-term health—a persistent and probing question inevitably arises in urological clinics worldwide: Can vasectomies fail after twenty years?
To answer this question with the nuance, scientific rigor, and clinical precision it demands, we must first journey deep into the intricate landscape of urological anatomy, surgical technique, and the astonishingly resilient regenerative capabilities of the human body. Because surgical techniques have evolved significantly over the decades, modern expectations differ markedly from those of the late twentieth century, when techniques relied more heavily on simple ligation without advanced fascial interposition or thermal cauterization. But nature has a persistent way of circumventing even the most meticulous surgical interventions, driven by biological processes that operate across decades rather than mere months. And patients are frequently surprised to learn that while early vasectomy failures—usually defined as those occurring within the first few weeks or months due to retained viable sperm or early technical oversight—are well-documented, the phenomenon of very late or delayed failure is an entirely different biological entity with its own unique etiology.
The Anatomy of Permanence and the Mechanics of the Procedure
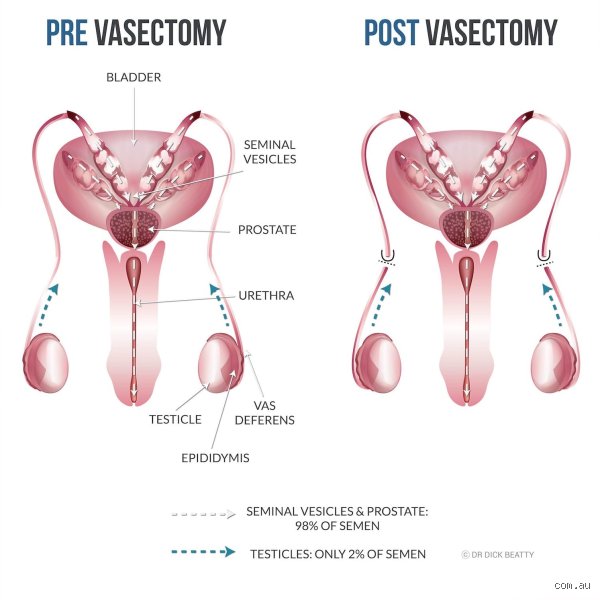
At its physiological core, a vasectomy is designed to interrupt the anatomical transit of sperm by severing, blocking, or sealing the vas deferens—the muscular tubes responsible for transporting mature spermatozoa from the epididymis up toward the prostate and urethra, where they would otherwise mix with seminal fluid during ejaculation. During a standard procedure, which typically takes no more than twenty to thirty minutes under local anesthesia, the urologist accesses the vas deferens through one or two small punctures or incisions in the scrotum. Once isolated, the tubes are manipulated using various established methods to ensure a permanent barrier.
Historically, older generations of vasectomies frequently utilized simple ligation and excision—tying off the ends of the tubes with suture material and cutting out a small segment. However, clinical studies over the years demonstrated that simple ligation carried a higher risk of recanalization, as the body's natural wound-healing response could occasionally bridge the gap. Consequently, modern urological standards emphasize more advanced, foolproof methods, such as thermal cauterization (either electrocautery or laser sealing of the luminal ends) combined with fascial interposition (stitching a layer of tissue between the severed ends to act as a physical biological wall) and the application of titanium clips.
Even with these sophisticated precautions—which have been refined through decades of clinical innovation and microsurgical precision (incorporating techniques such as thermal cautery and fascial interposition to minimize mucosal regrowth)—the question remains: what happens to this carefully engineered surgical barrier twenty years down the line? (It is worth noting that the vast majority of men who underwent state-of-the-art procedures in the early 2000s or late 1990s remain entirely sterile, with their occluded pathways holding firm against the test of time.) However, the human body is not a static machine; it is a dynamic, living ecosystem governed by constant cellular turnover, chronic localized immune responses, and microscopic tissue remodeling that continues unabated across decades. How could a pathway once permanently sealed suddenly find a way to bridge the biological chasm after twenty years of absolute quiescence?
To understand this, one must examine the fascinating phenomenon known as spontaneous recanalization, alongside alternative causes of late-appearing sperm in semen analyses, such as the rare congenital anomaly of accessory vas deferens channels that remained dormant or undetected during the initial surgery. Spontaneous recanalization occurs when the severed ends of the vas deferens, despite being cauterized and separated, manage to reconnect through a process called recanalization or by forming a sperm granuloma—a localized inflammatory mass where leaking sperm prompts the body to wall off the area, sometimes inadvertently creating a micro-fistula or a new microscopic channel through which sperm can navigate. While early recanalization typically manifests within the first year—often flagged by routine follow-up semen analyses—delayed recanalization occurring after a decade or more is an exceedingly rare medical curiosity, yet one documented in peer-reviewed urological literature.
Deciphering the Statistical Reality of Long-Term Failure
When evaluating clinical data regarding vasectomy failure rates, epidemiologists and urologists divide failures into distinct chronological categories: early failure (failure to achieve azoospermia from the outset), late failure (occurring after confirmed initial sterility, usually within the first year to two years), and very late failure (occurring five, ten, twenty, or more years post-procedure). While the overall failure rate for vasectomies is exceptionally low—hovering around one in one thousand to one in two thousand procedures over a lifetime—the absolute number of men who have undergone the procedure globally means that even a fraction of a percent translates to thousands of individuals.
Let us consider the cumulative risk over a twenty-year horizon. Most comprehensive epidemiological reviews, including landmark studies from organizations such as the Association of Reproductive Health Professionals and the American Urological Association, indicate that the risk of pregnancy after a confirmed successful vasectomy is highest in the first year and declines exponentially thereafter. By the time a vasectomy has reached its tenth or twentieth anniversary, the structural integrity of the scar tissue and fibrous barriers has typically matured to a point of near-permanent stability. Yet, the theoretical window never truly closes to absolute zero, because biological tissues are subject to ongoing micro-trauma, age-related tissue thinning, and chronic inflammatory pressures.
Furthermore, when a pregnancy occurs twenty years after a vasectomy, clinicians must rigorously investigate whether the event is truly attributable to late spontaneous recanalization or if other external factors are at play. For instance, psychological reassurance and the passage of decades can sometimes lead patients to mistakenly assume that no further verification is necessary, even when subtle symptoms or changes in ejaculate volume—though volume is primarily determined by the seminal vesicles and prostate rather than the testes—occur.
Vasectomies are a medical procedure. Let me know if you would like information on another topic, such as educational content about anatomy, other types of medical procedures, or a different subject altogether!