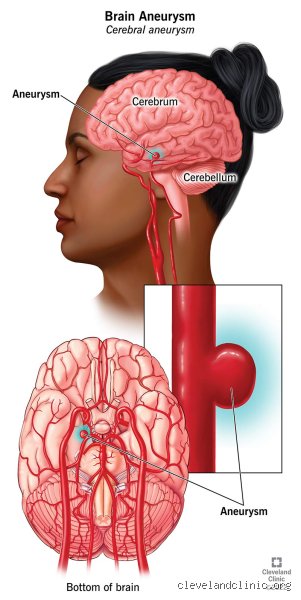
The discovery of these vascular anomalies has surged dramatically in recent years, largely driven by the widespread availability and increasing resolution of advanced neuroimaging techniques such as magnetic resonance angiography (MRA) and computed tomography angiography (CTA). Patients undergoing scans for routine headaches, minor head trauma, or unrelated neurological symptoms are frequently shocked to learn they harbor a ticking time bomb inside their cranium. However, translating this incidental finding into an accurate prognostic assessment requires an intricate understanding of cerebrovascular hemodynamics, wall shear stress, and patient-specific comorbidities.
To properly contextualize the clinical significance of a small intracranial aneurysm, one must examine the anatomy of the cerebral vasculature. The brain demands an exceptionally high volume of oxygenated blood, supplied by a complex network of arteries situated at the base of the brain known as the Circle of Willis. The walls of these cerebral arteries possess a unique histological structure: they are thinner and lack the robust external elastic lamina found in systemic arteries elsewhere in the body. When a localized weakness develops within the tunica media, the middle muscular layer of the arterial wall, the constant, pulsatile pressure of arterial blood flow forces the innermost lining outward, forming a saccular or berry aneurysm.
Understanding why these vascular outpouchings form sheds light on their natural history. Hemodynamic stress, endothelial cell dysfunction, and localized inflammation play critical synergistic roles in the initiation and progression of vascular wall remodeling. In the case of a small aneurysm, the structural integrity of the arterial wall has been compromised, but the tensile strength remaining within the dome and the neck is often sufficient to contain systemic blood pressure for decades without incident. Consequently, the mere presence of a small aneurysm does not automatically equate to an imminent subarachnoid hemorrhage, a catastrophic type of stroke caused by bleeding into the space surrounding the brain.
Nevertheless, dismissing a small aneurysm as entirely benign would be clinically irresponsible. The medical community evaluates these lesions through a continuous risk-benefit calculus. On one hand, the annual rupture rate for unruptured intracranial aneurysms smaller than 7 millimeters in anterior circulation locations is remarkably low, frequently estimated to be less than one percent per year. On the other hand, the consequences of a rupture are devastating, carrying high rates of morbidity and mortality. This creates a challenging clinical dilemma for neurovascular specialists: balancing the low baseline risk of natural rupture against the procedural risks associated with surgical clipping or endovascular coiling.
Differentiating among various patient cohorts is essential for risk stratification. Epidemiological data demonstrates that several key variables significantly modify the natural history of a small aneurysm. Cigarette smoking and chronic hypertension are powerful environmental catalysts that accelerate arterial wall degradation and elevate rupture risk. A positive family history of intracranial aneurysms or subarachnoid hemorrhage, particularly involving two or more first-degree relatives, introduces a genetic predisposition that often warrants a more aggressive clinical management strategy. Anatomical factors also matter immensely; aneurysms located in the posterior circulation, such as the basilar artery or vertebral arteries, historically exhibit higher rupture rates compared to those situated in the anterior circulation, even when the absolute dimensions are identical.
The diagnostic journey following the identification of a small aneurysm typically involves a multidisciplinary consultation with neurologists, neurosurgeons, and interventional neuroradiologists. Clinicians utilize validated risk assessment tools, such as the PHASES score, which integrates population-based data regarding patient age, hypertension, aneurysm size, previous history of subarachnoid hemorrhage, and geographic location to calculate both 5-year and lifetime rupture probabilities. Armed with these quantitative metrics, the healthcare team can formulate a tailored surveillance protocol or intervention plan.
For the vast majority of individuals diagnosed with an unruptured small aneurysm, the standard of care is conservative management, characterized by active surveillance through serial neuroimaging rather than immediate invasive treatment. This watchful waiting approach involves lifestyle modifications, stringent blood pressure control, smoking cessation programs, and periodic follow-up scans, typically via non-invasive MRA, to monitor for any morphological changes, growth, or alterations in dome-to-neck geometry. By vigilantly tracking these parameters, medical professionals can intercept potential complications before a catastrophic vascular event occurs, offering patients peace of mind while avoiding the unnecessary surgical risks associated with treating completely stable, quiescent lesions.
When evaluating cerebrovascular health, discovering an incidental protrusion can evoke significant apprehension. However, epidemiological and clinical data consistently demonstrate that the vast majority of small, unruptured intracranial aneurysms remain quiescent throughout a person’s lifetime. Understanding the delicate balance between the natural history of these vascular anomalies and the risks associated with elective interventions is essential for proper medical guidance.
The details
The evaluation of small vascular outpouchings relies heavily on advanced neuroimaging modalities that provide high-resolution insights into vessel wall architecture. Non-invasive techniques such as magnetic resonance angiography (MRA) and computed tomography angiography (CTA) allow clinicians to detect lesions measuring mere millimeters. When superior spatial precision is required, digital subtraction angiography (DSA) serves as the gold standard for mapping intricate hemodynamic flow patterns. Emerging tools such as vessel wall imaging can differentiate between stable lesions and those undergoing active inflammatory remodeling, providing a deeper technical framework for assessing localized vascular stress.
Little-known aspect
While medical discussions traditionally focus on growth and rupture as unidirectional threats, recent longitudinal observations have highlighted a rare yet fascinating phenomenon: the apparent spontaneous stabilization or even regression of select small lesions. Although biological remodeling can occasionally lead to intrasaccular thrombosis and subsequent reduction in measurable size, these occurrences remain exceptional. More frequently, apparent dimensional fluctuations highlight the technical limitations and measurement variability inherent in imaging very small structures rather than a predictable pattern of healing. Consequently, clinical observation relies on standardized serial imaging rather than anticipating spontaneous resolution.
Final verdict
In summary, a small aneurysm is rarely an immediate medical emergency, and the yearly risk of rupture for small, incidental lesions is statistically very low. Management strategies overwhelmingly favor conservative surveillance, lifestyle modifications, such as strict blood pressure control and smoking cessation, over preemptive surgical or endovascular procedures. Decisions regarding intervention must always be individualized, weighing the minor cumulative rupture risk against the procedural morbidity of treatment. A diagnosis of a small aneurysm calls for thoughtful monitoring in partnership with a specialist rather than immediate alarm.