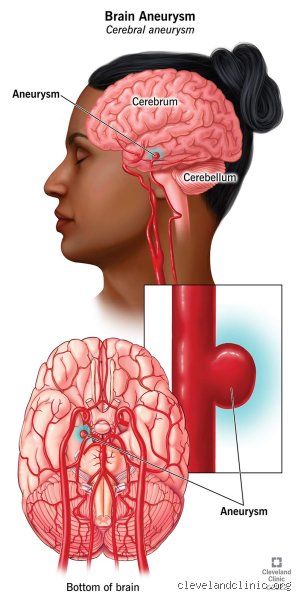
Building upon baseline physiological factors influencing vascular integrity, the precise anatomical site of a cerebral outpouching heavily dictates rupture probability. Statistical tracking consistently shows that anterior circulation lesions—specifically those situated along the middle cerebral artery or the internal carotid artery—tend to exhibit a statistically lower annual rupture rate compared to their posterior circulation counterparts. Lesions residing on the basilar artery, the posterior cerebral artery, or the posterior inferior cerebellar artery face unique biomechanical challenges. High-velocity blood flow impacts these posterior junctions directly, generating continuous shear stress that accelerates structural degradation of the vessel wall. Consequently, sizing metrics that suggest stability in an anterior vessel might necessitate intervention when observed in a posterior location. Hemodynamic simulation studies reveal that secondary branching angles and vessel curvature exacerbate localized wall tension, transforming seemingly minor structural anomalies into high-risk zones over extended periods.
Beyond sheer volumetric measurements, the geometry of the vascular sac provides critical insight into susceptibility. Irregularly shaped protrusions, characterized by multiple lobes or secondary outpouchings known as daughter sacs, indicate focal weaknesses within the wall architecture. These structural asymmetries concentrate mechanical forces onto specific points, creating localized zones of extreme tension. Clinical evaluations frequently utilize the aspect ratio, the height of the sac divided by the neck width, alongside the size ratio to gauge stability. A high aspect ratio correlates strongly with an elevated risk of structural failure, as a narrow neck coupled with a distended dome restricts normal blood recirculation, trapping turbulent currents against the vulnerable apex. Turbulent flow patterns inside the sac induce chronic endothelial injury, upregulating inflammatory pathways that degrade the extracellular matrix and thin the wall progressively.
Intrinsic patient characteristics modify baseline rupture probabilities significantly. Chronic hypertension exerts a continuous, destructive pressure upon already compromised vascular tissue, accelerating the degradation of elastin and collagen fibers that provide structural elasticity. Smoking acts as an independent catalyst, introducing systemic inflammation and altering endothelial function, which compromises the body's natural tissue repair mechanisms. Age and biological sex also play measurable roles; post-menopausal women demonstrate a statistically higher incidence of unruptured formations and a correspondingly elevated rupture risk, pointing toward hormonal influences on vascular wall resilience. Familial history introduces a genetic component, wherein individuals possessing a first-degree relative with a history of intracranial bleeding face a compounded probability profile. Genetic screening initiatives continue to uncover specific chromosomal loci associated with structural weakness in cerebral arteries, allowing for refined risk stratification based on hereditary predispositions.
Tracking the progression or stability of an identified vascular anomaly requires high-resolution neuroimaging. Magnetic Resonance Angiography (MRA) and Computed Tomography Angiography (CTA) offer non-invasive methods to monitor dimensional changes over time without the risks associated with catheterization. When precise geometric analysis becomes necessary, digital subtraction angiography serves as the gold standard, providing real-time visualization of blood flow dynamics and subtle morphological shifts. Establishing a consistent surveillance schedule allows clinicians to detect subtle expansion or shape alterations long before catastrophic failure occurs, shifting the clinical paradigm from emergency intervention to proactive management. Radiomics and machine learning algorithms are increasingly applied to imaging datasets, extracting textural features from the vessel wall that standard visual inspection might miss, thereby enhancing predictive accuracy.
The integration of computational fluid dynamics into everyday clinical practice represents a significant leap forward in understanding vascular vulnerability. By simulating blood flow patterns tailored to an individual patient’s specific geometry, specialists can calculate exact wall shear stress vectors and oscillatory shear index values. These advanced computational models reveal how microscopic variations in blood velocity and pressure distribution contribute to localized cellular fatigue. As research progresses, these tools bridge the gap between static imaging observations and dynamic physiological reality, offering unprecedented clarity regarding which vascular formations are truly quiescent and which harbor active destabilization processes. Consequently, clinical monitoring protocols evolve from generic population-based timelines into highly customized surveillance schedules tailored precisely to the mechanical reality of each individual case.
When diagnostic data indicates a high probability of rupture, medical professionals must weigh prophylactic treatment against natural history risks. Surgical clipping involves placing a titanium clip across the neck of the sac, isolating it from normal circulation while preserving parent vessel patency. Alternatively, endovascular interventions utilize platinum coils, stents, or flow-diverting devices deployed via catheter to induce thrombosis within the anomaly, effectively neutralizing the rupture threat from within. Each therapeutic pathway carries inherent procedural risks, requiring a meticulous calculation where the anticipated likelihood of spontaneous rupture must outweigh the potential morbidity associated with treatment. Patient-specific factors such as overall health status, age, and individual preferences heavily influence this shared decision-making process, ensuring that interventions align with broader wellness objectives.
Evaluating the likelihood of intracranial vessel failure demands a multidimensional approach that integrates size, location, morphology, patient health habits, and genetic background. Modern neurovascular assessment moves away from rigid thresholds, embracing personalized risk calculators and sophisticated computational fluid dynamics to predict outcomes accurately. By combining precise imaging technology with comprehensive clinical evaluations, healthcare providers navigate the delicate balance between watchful waiting and timely surgical or endovascular intervention, ultimately safeguarding neurological health through rigorous, individualized care strategies.