The Decision-Making process: To treat or to monitor?
When a small aneurysm is detected—whether in the brain, the aorta, or another peripheral blood vessel—the primary challenge for vascular specialists and neurosurgeons is determining the optimal timing and method of intervention. Because every patient's anatomical profile, overall health status, and aneurysm characteristics are unique, the choice between immediate intervention and conservative observation involves a meticulous risk-benefit analysis. Factors such as the exact location of the aneurysm, its shape, a patient's family history of rupture, and age all play critical roles in shaping the medical roadmap.
For many small aneurysms, the natural history, meaning the likelihood that the aneurysm will remain stable versus the risk of it rupturing, favors a cautious approach. However, advancements in modern medicine have also made elective treatments safer and more precise than ever before.
Approach one: Active Surveillance (watchful waiting)
For the majority of small, unruptured aneurysms, particularly cerebral or abdominal aortic aneurysms measuring under certain clinical thresholds, the standard of care often begins with active surveillance, commonly referred to as watchful waiting or conservative management.
The Rationale: The risks associated with treating a very small, asymptomatic aneurysm can sometimes outweigh the small statistical risk of rupture. Therefore, holding off on invasive procedures allows the medical team to monitor the stability of the vessel over time.
Imaging Protocols: Patients undergoing active surveillance are typically scheduled for regular follow-up imaging scans. For brain aneurysms, this might involve Magnetic Resonance Angiography (MRA) or Computed Tomography Angiography (CTA). For abdominal aortic aneurysms (AAAs), serial ultrasound examinations are the gold standard. These scans are usually performed at six months after the initial diagnosis, and if stability is confirmed, spacing out to annual intervals.
Risk Factor Modification: While waiting, the focus shifts aggressively toward mitigating factors that weaken blood vessel walls. This includes rigorous blood pressure control, smoking cessation, managing cholesterol levels, and adopting a heart-healthy lifestyle to reduce hemodynamic stress on the aneurysm site.
Approach two: Minimally invasive Endovascular interventions
If a small aneurysm demonstrates growth, changes in shape, or if patient risk factors dictate active treatment, modern medicine heavily favors minimally invasive endovascular techniques whenever anatomically feasible. These procedures are performed from inside the blood vessels, avoiding the need for traditional open surgery.
Endovascular Coiling: Most commonly used for cerebral aneurysms, this technique involves threading a microcatheter through the femoral artery in the groin up to the site of the aneurysm. Platinum coils are then deployed into the aneurysm sac. These coils induce a clotting response (thrombosis), sealing off the aneurysm from normal blood circulation and preventing future rupture.
Flow Diverters: For wide-necked or more complex small aneurysms, specialized stent-like devices called flow diverters are placed across the neck of the aneurysm inside the parent artery. This redirects blood flow past the aneurysm opening, prompting the body to heal the vessel wall naturally over time.
Stent-Graft Placement (Endovascular Aneurysm Repair - EVAR): When dealing with small aortic aneurysms, surgeons often use EVAR. A fabric-lined metal stent (graft) is guided through blood vessels to line the weakened section of the aorta, creating a new pathway for blood flow and relieving pressure on the aneurysm wall.
Advantages of Endovascular approaches
Endovascular techniques have revolutionized vascular care by offering significantly shorter hospital stays, minimal physical scarring, reduced risk of infection, and a much faster return to normal daily activities compared to open surgery.
Approach three: Open Surgical Repair (Clipping)
While endovascular methods are preferred in many cases, open surgical repair remains a foundational and highly effective option, particularly when aneurysm anatomy is unsuitable for catheter-based devices or when a permanent, definitive cure is desired in younger patients.
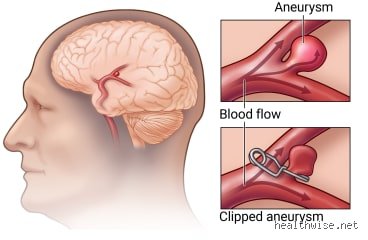
Surgical Clipping for Brain Aneurysms: This procedure requires a neurosurgeon to perform a craniotomy, temporarily removing a small section of the skull to access the aneurysm. Under microscopic visualization, a tiny metallic clip is placed directly across the neck of the aneurysm, permanently stopping blood flow into the sac while preserving normal blood flow through the main artery. Once the clip is secured, the aneurysm is safely isolated from the circulation.
Open Surgical Repair for Aortic Aneurysms: For peripheral or aortic locations, open surgery involves making an incision in the abdomen or chest, clamping the blood vessel temporarily, opening the aneurysm sac, and sewing a synthetic graft in place to reinforce the vessel wall.
Clinical Considerations
Open surgery is generally more invasive and requires a longer recovery period, including a brief stay in an intensive care unit (ICU) followed by inpatient rehabilitation. However, it boasts a long-term track record of durability, often requiring fewer follow-up imaging studies over a lifetime compared to certain endovascular devices.
Post-Procedure Recovery and Long-Term management
Regardless of whether a small aneurysm is managed via watchful waiting, endovascular coiling, or surgical clipping, the journey does not end with the procedure. Comprehensive long-term care is essential to ensure lasting vascular health.
Immediate Recovery Phase: Following an endovascular procedure, patients are monitored closely in a recovery unit for several hours, focusing on puncture site stability and neurological or hemodynamic checks. Open surgery recovery involves pain management, gradual mobilization, and monitoring for post-operative complications.
Medication and Lifestyle Adherence: Patients are frequently prescribed antiplatelet or anticoagulant medications (such as aspirin or clopidogrel) following endovascular interventions to prevent blood clots from forming on devices. Lifelong blood pressure management remains the single most important prescription for preventing recurrence or the development of new aneurysms.
Ongoing Surveillance: Even after successful treatment, periodic imaging follow-ups are scheduled. These check-ups confirm that coiling compaction remains stable, clips or stents are securely positioned, and no new vascular abnormalities are developing elsewhere in the body.
Would you like to explore the specific differences in recovery times and lifestyle adjustments required after brain aneurysm treatment versus aortic aneurysm treatment?