Almost as quickly as the ice pack is pulled from the cooler, a familiar rule is chanted by coaches, trainers, and parents alike: “Keep it on for twenty minutes, then take it off for twenty minutes.”
For decades, this "20 on, 20 off" rhythm has been treated as an absolute commandment of first-aid and sports rehabilitation. Yet, how many of us actually understand the biological choreography dictating that specific rhythm? Why twenty minutes? Why not ten, thirty, or leaving the ice on continuously until the swelling subsides?
To answer these questions, we have to look past the simple chill of a frozen gel pack and dive deep into human physiology, vascular dynamics, and the delicate balance between reducing acute inflammation and preserving healthy tissue.
The acute phase: Understanding what happens when injury strikes
To understand why we apply ice in pulses, we must first understand what happens inside the body the moment an injury occurs. Whether it is a sprain, a strain, or a contusion, tissue trauma triggers an immediate, highly orchestrated emergency response known as the inflammatory cascade.
When muscle fibers, ligaments, or blood vessels are torn or stressed, the body sends out chemical distress signals—histamines, prostaglandins, and cytokines. These signaling molecules cause nearby blood vessels to dilate and become porous, allowing white blood cells, plasma, and fluid to flood into the surrounding tissue to begin the cleanup and repair process.
This fluid accumulation is what we recognize as acute swelling, accompanied by localized heat, redness, and pain. While inflammation is a necessary and vital part of healing, an excessive or uncontrolled inflammatory response can create a secondary problem:
Increased pressure: Swelling builds up mechanical pressure inside the confined spaces of muscle compartments and joint capsules.
Cellular hypoxia: This high pressure can compress surrounding micro-vessels, starving healthy, uninjured cells of oxygen and nutrients, thereby widening the zone of cellular damage.
This is where cold therapy—scientifically known as cryotherapy, enters the equation. By applying an external source of cold to the traumatized area, we seek to modulate this aggressive initial response, buying the body time and preventing secondary tissue injury.
The mechanics of cold: Vasoconstriction and metabolic slowdown
When an ice pack touches the skin, it triggers a rapid sequence of physical and chemical reactions designed to cool the target tissue down. The primary objective is twofold: reducing blood flow and lowering cellular metabolism.
1. Vasoconstriction and flow reduction
The immediate physiological reaction to cold is vasoconstriction, the narrowing of blood vessels. As the local temperature drops, the smooth muscles surrounding the local arterioles and capillaries contract. This dramatically slows down the delivery of blood to the injury site. By restricting the influx of fluid, plasma, and inflammatory cells, ice acts as a temporary brake on the swelling process, limiting the total volume of extravasated fluid that accumulates in the interstitial spaces.
2. Metabolic suppression and hypoxia defense
Every cell in the human body relies on metabolic processes to survive. When a cell is injured, its metabolic demand spikes because it is trying to repair itself, yet its oxygen and nutrient supply is compromised due to disrupted local circulation.
Applying cold lowers the temperature of the tissue, which directly depresses cellular metabolism. Think of it as putting the local cells into a mild state of thermal hibernation. By slowing down their metabolic rate, these cells require significantly less oxygen and energy to survive. Consequently, they become far more resilient to the temporary ischemic (low-oxygen) state caused by the injury and subsequent vasoconstriction, dramatically reducing the risk of cell death (necrosis).
3. Neurological pain modulation
Beyond vascular and metabolic effects, cold therapy provides immediate relief by altering nerve conduction velocity. Sensory nerve endings transmit pain signals to the spinal cord and brain at high speeds. When chilled, these nerve fibers experience a temporary slowdown in conduction velocity. Cold activates specialized thermoreceptors in the skin that gate-control pain pathways, effectively overriding and dampening the discomfort signals sent to the central nervous system.
The critical threshold: Why "too much of a good thing" becomes dangerous
Given the impressive benefits of cold therapy, reduced swelling, lowered metabolism, and pain relief, it is entirely natural to wonder: If 20 minutes is good, wouldn't 60 minutes or continuous icing be even better?
The answer is a definitive and hazardous no.
Human skin, subcutaneous fat, and skeletal muscle are living biological tissues that have strict physiological limits regarding thermal tolerance. Pushing beyond these limits transforms a therapeutic intervention into a destructive agent. There are two primary reasons why continuous, unmanaged cold exposure causes severe harm:
1. The risk of Cold-Induced tissue damage (frostbite and nerve injury)
When skin temperature drops below a certain threshold, typically around 15°C (59°F), and approaches freezing levels, the local blood vessels do not just constrict; they can begin to freeze or suffer permanent endothelial damage. Ice crystals can form within the extracellular and intracellular spaces, disrupting cell membranes and leading to localized tissue death (frostbite). Superficial nerves running close to the surface (such as the peroneal nerve near the knee or the ulnar nerve at the elbow) are exceptionally vulnerable to cold injury, which can result in temporary or even permanent localized numbness, tingling, or motor dysfunction.
2. The paradoxical Response: The Lewis Hunting Reaction
The human body is remarkably stubborn when it comes to defending its core and local temperatures against extreme environments. If cold exposure is sustained continuously for too long (usually past 20 to 30 minutes), the body initiates a protective neurological reflex known as the Lewis Hunting Reaction (or cold-induced vasodilation).
Instead of maintaining continuous vasoconstriction, the local blood vessels suddenly and aggressively dilate. The body attempts to flood the freezing tissue with warm blood to prevent tissue necrosis and preserve local viability.
While this sounds beneficial on paper, in the context of an acute injury, it has the exact opposite effect of what is desired:
It dumps a fresh wave of warm blood and inflammatory fluids directly back into the injury site.
It rapidly reverses the metabolic slowing you just achieved.
It re-initiates swelling and increases acute pain pressure.
Therefore, leaving an ice pack on indefinitely defeats its own purpose, flipping the physiological switch from therapeutic vasoconstriction right back into unwanted vasodilation and increased inflammation.
Setting the boundary: The physics of Thermal transfer
To establish the "20 on" portion of the protocol, sports medicine researchers and clinicians had to evaluate the physics of thermal transfer through human tissue layers.
Human skin, fat, and muscle have distinct thermal conductivity properties. Fat, in particular, acts as an excellent thermal insulator. When an ice pack is applied to an area with a significant layer of subcutaneous adipose tissue, it takes a considerable amount of time for the cold energy to penetrate through the skin and fat layers down to deep skeletal muscle or joint capsules.
Studies measuring intramuscular temperatures during ice application reveal that it generally takes between 15 to 20 minutes for the cooling effect to reach its optimal therapeutic depth in most standard soft-tissue injury sites without risking superficial skin freezing.
Stopping at the 20-minute mark represents a calculated biological sweet spot: it maximizes the cooling and metabolic suppression of the target tissue while keeping cumulative thermal stress safely below the threshold of skin damage, nerve injury, or the onset of the counterproductive Hunting Reaction.
Preparing for the "Off" Cycle
Having established why the cold must be applied in timed bursts to successfully manage metabolic demand and acute swelling without triggering tissue damage or reflexive vasodilation, the next critical component is understanding the recovery phase.
The twenty minutes during which the ice pack is removed are not simply a waiting period, they are an active, equally vital phase of the physiological cycle that allows normal micro-circulation to briefly restore vital nutrients and clear out metabolic waste before the next cooling phase begins.
The physiological mechanics: What happens during the first twenty minutes
When an ice pack is applied to an acute injury, a trauma site, or a post-operative surgical area, the primary objective is to alter local tissue thermodynamics. Heat transfer occurs rapidly between the skin surface and the cold medium, causing cutaneous and subcutaneous blood vessels to constrict. This physiological process, known as vasoconstriction, dramatically reduces local blood flow by narrowing the microvascular lumen.
By restricting microvascular perfusion, the body curtails the extravasation, the leakage of fluid, blood cells, and inflammatory mediators, into the surrounding interstitial spaces. This is the core mechanism responsible for mitigating acute swelling and preventing massive hematoma formation. Cold application significantly lowers nerve conduction velocity. Sensory nerve endings transmit pain signals to the central nervous system at a severely impaired rate, effectively acting as a localized, non-pharmacological analgesic that dulls nociceptive feedback loops.
However, skin and superficial muscle tissue have strict physiological thresholds. Within the initial 15 to 20 minutes of cold exposure, maximum therapeutic vasoconstriction is typically achieved. Extending the exposure past this window yields diminishing returns regarding pain reduction and edema control, while exponentially increasing the risk of cellular damage and superficial nerve neuropraxia.
The critical necessity of the "off" period: Preventing ischemia and rebound effects
The twenty-minute break is not merely a convenience or a pause for comfort; it is a vital physiological safeguard. When tissue temperature drops significantly, cellular metabolism slows down drastically. If this cold-induced metabolic depression is maintained indefinitely without intermittent rewarming, local cells are starved of adequate oxygen and nutrients, leading to a state of tissue ischemia.
Prolonged cold exposure triggers a protective physiological mechanism known as the Hunting response (or cold-induced vasodilation). After a prolonged period of intense vasoconstriction, the body attempts to protect the tissue from freezing damage by abruptly dilating the blood vessels. Paradoxically, this sudden influx of warm blood can cause an immediate surge in local swelling, hyperemic flush, and inflammation, counteracting the very objective the therapy sought to achieve.
Allowing a twenty-minute "off" period permits the skin, capillaries, and muscle tissue to return to their baseline temperature. This cyclical thermal rhythm prevents ischemic injury, protects superficial nerve pathways from cold-induced damage, and ensures that the microvasculature remains responsive to subsequent therapeutic applications rather than becoming desensitized or damaged.
Balancing pain management and the inflammatory cascade
A common misconception in modern sports medicine and post-operative care is that inflammation is an entirely adverse process that must be completely eradicated. In reality, acute inflammation is the essential first phase of the body's natural tissue repair sequence. Neutrophils and macrophages flood the injury site during the initial inflammatory window to clear cellular debris, fight potential pathogens, and secrete growth factors that initiate collagen synthesis and tissue remodeling.
Over-icing, such as leaving cold packs on continuously for hours at a time, can suppress this necessary inflammatory response to a pathological degree, ultimately delaying long-term tissue regeneration. The 20-on / 20-off protocol strikes an evidence-based clinical balance:
Targeted Control: It suppresses acute, debilitating pain and excessive fluid accumulation during peak inflammatory hours.
Preserved Healing: It leaves sufficient intervals of normal metabolic temperature for cellular repair mechanisms and immune cell migration to function unimpeded.
This measured approach ensures that patients can manage post-procedural discomfort or athletic trauma without inadvertently disrupting the body's intrinsic biological healing timeline.
Clinical best practices for implementing the protocol
To maximize the efficacy of the 20-on / 20-off method while safeguarding skin integrity, clinicians emphasize several non-negotiable guidelines:
Always Use a Thermal Barrier: Direct skin contact with frozen surfaces can cause localized ice burns, frostbite, or epidermal necrosis within minutes. A damp washcloth or thin towel provides optimal thermal conductivity while protecting the epidermis from direct crystallization.
Monitor Cutaneous Response: During the "off" phase, the skin should be inspected for abnormal pallor, persistent numbness, or blistering. Normal color and sensation must return before any subsequent ice cycle begins.
Combine with Elevation: Whenever anatomically feasible, elevating the injured limb above the level of the heart during both the "on" and "off" phases harnesses gravity to facilitate venous return and lymphatic drainage, further reducing dependent edema.
Transition Timing: For most soft tissue injuries and surgical recoveries, intensive round-the-clock application is typically restricted to the first 48 to 72 hours, after which therapy tapers down to post-activity management or transitions toward thermotherapy as directed by a healthcare professional.
Conclusion
The ubiquity of the 20-on / 20-off rule across orthopedics, physical therapy, and surgery recovery is rooted in rigorous physiological science. By understanding the delicate balance between vascular constriction, metabolic preservation, and the body's inflammatory response, practitioners can utilize cryotherapy as a precise medical tool. Respecting both halves of this cyclical protocol ensures maximum relief of pain and swelling while protecting tissue health and supporting long-term rehabilitation.
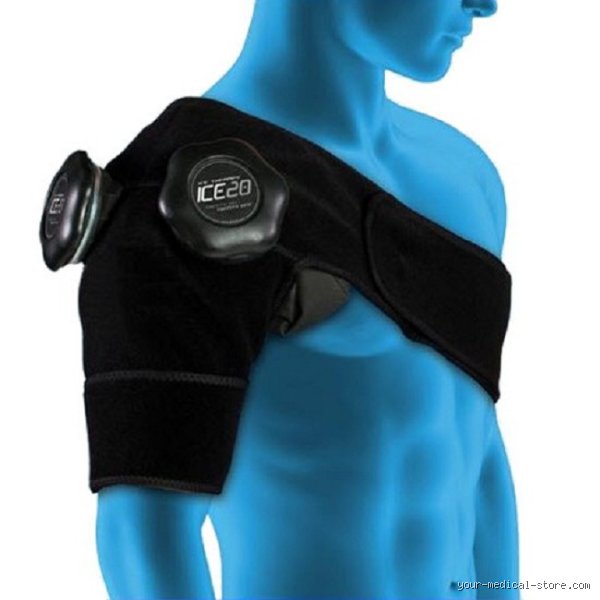
To see a practical demonstration of how cold therapy and targeted compression are applied using structured intervals, you can watch this ICE20 Double Shoulder Ice Compression Therapy demonstration. This video provides a visual overview of how specialized wraps maintain the precise positioning required during active recovery sessions.