Pancreatitis can present as a sudden, ferocious flare-up (acute pancreatitis) or as a smoldering, progressive destruction of tissue over time (chronic pancreatitis). Because the pancreas is anatomically deep and shares physical space and nerve pathways with many other abdominal organs—including the stomach, liver, gallbladder, and duodenum—diagnosing pancreatitis is rarely straightforward. Medical professionals cannot simply look at the organ from the outside; instead, they must rely on a sophisticated, multi-tiered investigative strategy.
To determine whether a patient is suffering from pancreatitis, figure out its severity, and pinpoint its underlying root cause, modern medicine utilizes a comprehensive triad: clinical evaluation, laboratory blood and stool tests, and advanced medical imaging. This first part of our in-depth examination explores the initial steps clinicians take, starting with the physical assessment and moving through the crucial blood and laboratory markers that sound the alarm when the pancreas is in distress.
1. The initial Clinical evaluation and Medical history
Long before any high-tech scanner is powered on or blood is drawn into a vial, the diagnostic process begins with a meticulous clinical conversation and physical examination. When a patient arrives at a clinic or emergency department complaining of severe, unyielding upper abdominal pain, the hallmark symptom of acute pancreatitis, physicians must act like medical detectives.
Decoding the patient's history
A healthcare provider will immediately begin mapping out the clinical narrative by asking targeted questions about the pain:
Onset and Progression: Did the pain strike suddenly, or has it been building over days or weeks? Acute pancreatitis typically features a rapid onset of severe, constant pain in the upper middle abdomen (the epigastric region).
Radiation: Does the pain stay localized, or does it pierce straight through to the back? Radiation of pain through to the thoracic or lumbar spine is a classic clue pointing toward pancreatic involvement, as the organ sits retroperitoneally (behind the abdominal cavity lining) right against the back wall.
Aggravating and Alleviating Factors: Does the pain worsen after eating or drinking? In acute pancreatitis, digestive enzyme activation inside the organ causes meals to trigger excruciating flare-ups. Patients often report that curling into a fetal position or leaning forward provides marginal relief.
Lifestyle and Medical Background: Because specific triggers account for the vast majority of pancreatitis cases, doctors will probe into personal and family histories. They look closely for known risk factors, such as a history of gallstones, regular or heavy alcohol consumption, recent abdominal trauma, or the use of specific medications (including certain diuretics, immunosuppressants, and anti-seizure drugs) known to irritate the pancreas.
The Physical Examination
Following the verbal history, the clinician performs a hands-on physical exam. The physician gently palpates the abdomen to check for localized tenderness, muscular guarding, and swelling. In acute pancreatitis, the upper abdomen is often profoundly tender to the touch, and the patient may exhibit abdominal distension due to an ileus, a temporary paralysis of the intestinal muscles caused by nearby inflammation. In severe hemorrhagic or necrotizing cases, doctors may even check for rare, subtle skin discolorations around the umbilicus (Cullen’s sign) or along the flanks (Grey Turner’s sign), which indicate internal bruising and blood tracking from retroperitoneal inflammation.
However, physical signs and symptoms alone are notoriously unreliable because conditions like perforated ulcers, acute cholecystitis, bowel obstructions, and acute myocardial infarctions can mimic the exact presentation of pancreatitis. To bridge this gap, medicine turns to biochemistry.
2. Laboratory diagnostics: The biochemical smoke alarms
When pancreatic cells (acinar cells) are injured, inflamed, or dying, they leak their internal contents, specifically the specialized enzymes they manufacture, into the surrounding tissue and ultimately into the bloodstream. Blood tests serve as the primary biochemical smoke alarms of pancreatic injury.
Serum lipase: The gold standard Blood test
Among all routine blood assays, serum lipase stands out as the premier biomarker for diagnosing acute pancreatitis. Lipase is an enzyme specifically tasked with breaking down dietary fats. Under normal physiological conditions, only minute amounts circulate in the blood.
When acute pancreatitis strikes, lipase levels skyrocket. Clinicians generally look for a value that is three times or greater than the upper limit of normal to establish a firm biochemical diagnosis. Lipase offers distinct clinical advantages: it begins to rise within 4 to 8 hours of symptom onset, peaks at around 24 hours, and stays elevated for anywhere from 7 to 14 days. This extended window means that even if a patient delays seeking care for several days, a lipase test can still catch the signature elevation.
Serum amylase: The traditional companion
Amylase is another digestive enzyme, primarily produced by the pancreas and the salivary glands, that aids in breaking down complex carbohydrates. Like lipase, amylase levels climb rapidly during an acute attack, usually within 2 to 12 hours of the onset of pain.
Despite its historical utility, amylase has a major drawback: it is cleared from the bloodstream much faster than lipase, often returning to normal ranges within 3 to 5 days. Amylase is less specific to the pancreas; elevated amylase can also be triggered by salivary gland disorders, kidney dysfunction, intestinal infarction, or gynecological conditions. Consequently, modern diagnostic protocols place greater clinical confidence in serum lipase due to its higher specificity and sensitivity.
Clinical Note: While a threefold elevation in lipase or amylase is a cornerstone criterion for diagnosing acute pancreatitis, neither enzyme level correlates directly with the severity of the disease. A patient with only moderately elevated enzymes can sometimes experience a severe, systemic illness, while someone with extremely high numbers may experience a relatively mild, self-limiting course.
Comprehensive metabolic panels and organ Function checks
Diagnosing pancreatitis involves looking far beyond just two enzymes. A comprehensive blood workup includes several other vital components to assess systemic impact, rule out mimics, and identify the root cause:
Complete Blood Count (CBC): Evaluates white blood cell (WBC) counts. An elevated WBC count points toward acute inflammation or infection. It also monitors hemoglobin and hematocrit levels, tracking whether a patient is losing fluid into the third space or developing hemoconcentration.
Liver Function Tests (LFTs): Measures bilirubin, alkaline phosphatase, aspartate aminotransferase (AST), and alanine aminotransferase (ALT). If these liver enzymes are sharply elevated alongside pancreatic markers, it strongly suggests a biliary etiology, meaning a gallstone has slipped out of the gallbladder, traveled down the biliary tree, and temporarily lodged itself at the ampulla of Vater, choking off the pancreatic duct.
Lipid Profile: Serum triglycerides are measured because severe hypertriglyceridemia (abnormally high blood fats) is a well-documented metabolic trigger for acute pancreatitis. Triglyceride levels soaring above 1,000 mg/dL can precipitate a dangerous inflammatory cascade in the gland.
Calcium and Renal Function: Calcium levels are monitored because severe pancreatitis can cause saponification (where free fatty acids bind calcium in the abdomen, causing hypocalcemia). Blood urea nitrogen (BUN) and creatinine are tracked to evaluate kidney hydration and filtration, as acute inflammation frequently induces acute kidney injury due to systemic fluid shifts.
Stool testing for chronic pancreatitis
While blood tests reign supreme in acute settings, diagnosing chronic pancreatitis, where the gland undergoes slow, progressive scarring and loses its ability to function, often requires looking at waste output.
Because a chronically damaged pancreas fails to produce adequate digestive enzymes (a condition called exocrine pancreatic insufficiency, or EPI), nutrients pass through the gut unabsorbed. Doctors may order a fecal elastase test. Elastase is a protein-digesting enzyme made exclusively by the pancreas that survives transit through the intestinal tract. A low concentration of elastase in a stool sample signals that the pancreas is no longer synthesizing sufficient digestive enzymes. Qualitative or quantitative stool studies can detect steatorrhea, excess fat in the stool, confirming that the body is failing to process fats properly due to pancreatic failure.
Moving forward in the diagnostic journey
By synthesizing the patient’s clinical presentation, physical tenderness, and striking elevations in serum enzymes like lipase alongside metabolic panels, physicians can establish a confident diagnosis of pancreatitis in the vast majority of acute cases. However, laboratory values cannot show the physical landscape of the organ, reveal hidden structural blockages, or map out tissue necrosis and fluid collections.
To understand how advanced medical imaging techniques, such as high-resolution abdominal ultrasounds, cross-sectional CT scans, and specialized internal scopes, allow doctors to visually inspect the pancreas and its delicate ductal networks, continue to the second part of this comprehensive clinical guide.
Advanced diagnostic Imaging: Looking inside the abdomen
When blood tests reveal sky-high enzyme levels, medical professionals have confirmed that the pancreas is distressed, but they still need to see why. Because the pancreas is tucked deep behind the stomach and near the spine, doctors rely on sophisticated medical imaging to map its precise structural state.
Computed tomography (CT) scans
A contrast-enhanced CT scan is often considered the gold standard for visualizing acute inflammation. During this painless procedure, an intravenous (IV) contrast dye is injected into the arm, which highlights blood vessels and allows radiologists to distinguish healthy pancreatic tissue from areas of necrosis (tissue death) or fluid collections. CT scans can instantly reveal swelling, calcifications, and the presence of acute fluid collections or pseudocysts.
Magnetic Resonance cholangiopancreatography (MRCP)
For patients who cannot tolerate CT contrast dye or radiation, an MRCP is a specialized type of Magnetic Resonance Imaging (MRI) that uses powerful magnetic fields and radio waves. MRCP is exceptionally detailed at mapping the intricate network of the pancreatic duct and the biliary tree. It can effortlessly spot tiny gallstones hiding in the ducts that traditional ultrasounds might miss.
Specialized endoscopic procedures
When non-invasive scans leave lingering questions or when a blockage needs immediate treatment, gastroenterologists turn to specialized scope-based procedures. These tools bridge the gap between diagnosis and active intervention.
Endoscopic Ultrasound (EUS)
An EUS involves passing a thin, flexible tube equipped with a high-frequency ultrasound probe down the throat, through the stomach, and into the small intestine. Because the tip of the scope rests inches away from the pancreas, it provides remarkably high-resolution images. Doctors use EUS to detect subtle signs of chronic scarring, early fibrosis, tiny blockages, or abnormal growths.
Endoscopic retrograde cholangiopancreatography (ERCP)
ERCP is unique because it is both a diagnostic tool and a therapeutic procedure. It combines X-ray imaging with the use of an endoscope. If a doctor suspects that a gallstone or a stricture is physically blocking the pancreatic or bile ducts, they can thread tiny instruments through the scope, locate the obstruction, extract the stone, or place a small stent to keep the duct open. While highly effective, ERCP carries a small risk of triggering temporary inflammation, so it is reserved for situations where intervention is necessary.
Evaluating chronic pancreatitis and Long-Term Function
While acute pancreatitis strikes suddenly and violently, chronic pancreatitis develops gradually over years, slowly destroying the organ's architecture. Diagnosing this chronic state often requires looking beyond structure to measure actual function.
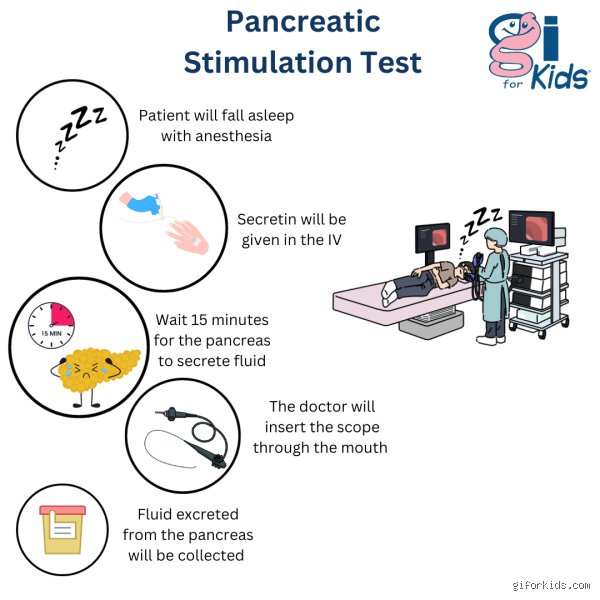
Stool Tests (Fecal Elastase): When the pancreas fails to produce enough digestive enzymes (a condition called exocrine pancreatic insufficiency), fats and proteins pass through the body unabsorbed. A stool sample measuring elastase levels helps doctors determine if the pancreas is manufacturing enough enzymes to support proper digestion.
Blood Glucose and HbA1c Tests: Because the pancreas houses the islets of Langerhans, the clusters of cells responsible for producing insulin, chronic inflammation frequently damages these cells, leading to secondary diabetes. Monitoring blood sugar is a vital component of a comprehensive pancreatic evaluation.
Putting the pieces together for a tailored treatment plan
Diagnosing pancreatitis is rarely a matter of ordering a single test. Instead, physicians assemble a clinical puzzle, combining a detailed personal history (evaluating alcohol intake, medication history, or family background), physical tenderness exams, enzyme biomarkers, and cross-sectional imaging.
By accurately pinpointing whether the inflammation is acute or chronic, and identifying its underlying root cause, such as a rogue gallstone or metabolic imbalance, medical teams can design an targeted treatment plan. Early and accurate detection remains the single most effective tool for managing symptoms, preventing recurring attacks, and preserving long-term digestive and metabolic health.