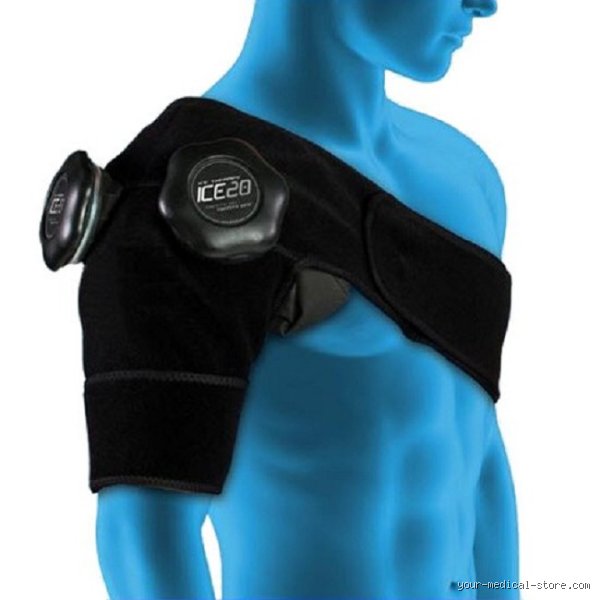
Demystifying Cold Therapy: The Science and Strategy Behind the "20 On, 20 Off" Rule
Whether you are an elite marathon runner pushing through the final miles of a grueling race, a weekend warrior who twisted an ankle on the soccer pitch, or someone recovering from joint surgery, the advice you receive from athletic trainers, physical therapists, and physicians is almost always identical: “Go home, elevate it, and put some ice on it.”
For decades, the standard prescription for managing acute soft-tissue injuries, muscle soreness, and post-operative inflammation has revolved around a specific, rhythmic cadence: 20 minutes on, followed by 20 minutes off. To the uninitiated, this recurring cycle might seem like an arbitrary rule of thumb—a convenient way to structure an afternoon of recovery. However, this protocol is far from random. It is rooted deeply in human physiology, vascular dynamics, and cellular biology.
Understanding why this exact ratio works requires a journey beneath the skin's surface, examining how blood vessels respond to extreme cold, how tissues manage metabolic stress, and why leaving an ice pack on indefinitely can actually sabotage your body's natural healing process.
The Vascular Response: Vasoconstriction and Metabolic Slowdown
To comprehend why the 20-minute mark holds such critical importance, we must first look at what happens the exact moment a sub-zero or near-freezing cold compress makes contact with the skin.
When an injury occurs—be it a sprained ligament, a strained muscle, or a severe contusion—the body immediately initiates an inflammatory cascade. Blood vessels in the local area dilate (vasodilation) to rush white blood cells, nutrients, and fluid to the site of the damage. While this acute inflammation is a necessary first step for tissue repair, an excess of fluid leads to swelling, intense pressure on surrounding nerve endings, and severe pain. Furthermore, the localized trauma creates cellular hypoxia; injured cells require oxygen, but damaged capillaries struggle to deliver it efficiently.
Applying an ice pack introduces a rapid drop in temperature that alters this environment through two primary mechanisms:
Vasoconstriction (The Tapering of Blood Flow): As cold penetrates the subcutaneous tissue, the smooth muscles surrounding the local blood vessels contract. This causes the capillaries and arterioles to narrow sharply, drastically reducing the volume of blood rushing into the injured zone. By limiting blood flow, ice acts as a physiological brake on the inflammatory cascade, preventing runaway swelling and minimizing fluid accumulation.
Metabolic Suppression: Cold temperatures slow down cellular metabolism. Just as food spoils more slowly in a refrigerator, injured muscle and connective tissue cells require significantly less oxygen and energy when chilled. By lowering the metabolic rate of the cells surrounding the injury, ice protects them from dying off due to temporary oxygen deprivation (secondary hypoxic injury), effectively putting the traumatized tissue into a state of suspended animation until the body can stabilize.
Why Twenty Minutes Is the Optimal Threshold
If lowering tissue temperature and reducing blood flow are the primary goals, common logic might suggest that more is better. Why not leave the ice pack on for an hour, or strap it down for the entire afternoon to keep the area completely numb?
As it turns out, human biology does not operate on linear assumptions. Leaving ice on the skin past a certain window transforms a therapeutic tool into a destructive hazard. Twenty minutes has universally emerged as the gold-standard threshold in sports medicine for several crucial reasons:
1. The Risk of Cold-Induced Tissue Damage (Frostbite and Cell Death)
Skin and superficial soft tissues have a finite tolerance for extreme cold. When temperatures drop significantly, extracellular fluids can begin to freeze, forming ice crystals that pierce cell membranes and cause irreversible tissue necrosis. Even short of actual freezing, prolonged exposure to cold constricts blood vessels so severely that the tissue is starved of vital oxygen and nutrients. Twenty minutes provides more than enough time to achieve the desired therapeutic vasoconstriction and metabolic slowdown without pushing the skin and underlying fat layers past the brink of cellular distress.
2. Nerve Conduction and Analgesia
Ice is a phenomenal natural pain reliever because it temporarily blocks nerve conduction velocity. Sensory nerve endings become sluggish, dulling the pain signals traveling up the spinal cord to the brain. This numbing effect typically peaks around the 15-to-20-minute mark. Pushing past this window yields diminishing returns regarding pain relief while exponentially increasing the risk of cold-induced nerve neuropraxia—a temporary or even prolonged loss of motor and sensory function caused by freezing or crushing nerve fibers beneath the skin.
3. The Paradox of Prolonged Icing
Perhaps the most compelling argument against prolonged icing is a physiological phenomenon known as the Hunting Response (or Lewis Hunting Reaction). First documented by Sir Thomas Lewis in 1930, this is a protective reflex loop managed by the central nervous system. When the body senses that a localized area is becoming dangerously cold (typically after 20 to 30 minutes of continuous exposure), the precapillary sphincters abruptly override the cold-induced vasoconstriction. They force the blood vessels to dilate rapidly, flooding the chilled area with warm blood to protect the tissue from freezing.
If you leave an ice pack on for an hour, you trigger this rebound vasodilation. Instead of keeping blood flow suppressed to control swelling, you inadvertently reopen the vascular floodgates, sending a surge of inflammatory fluid right back into the injury site.
The Critical Role of the "20 Off" Recovery Phase
Just as the 20-minute application window prevents tissue damage and over-cooling, the mandatory 20-minute rest period is vital for restoring physiological homeostasis. Treating ice therapy as a continuous, unbroken chore misunderstands how living tissue recovers.
During the 20 minutes that the ice is removed, several essential processes occur:
Reperfusion and Normalization: The tissue is allowed to re-warm naturally to its baseline temperature. This passive re-warming restores normal cellular metabolism and allows fresh, oxygenated blood to circulate through the micro-capillaries, delivering the nutrients necessary for genuine cellular repair.
Preventing Ischemic Injury: By breaking up the cold exposure into manageable intervals, you prevent prolonged ischemia (restriction of blood supply). The body is given alternating phases of protection (cooling) and nourishment (re-warming).
Resetting the Nerves: It gives the sensory receptors in the skin a break, preventing cumulative thermal shock and allowing you to safely evaluate the skin's condition before launching into a subsequent round of therapy.
Summary of the First Phase
The "20 on, 20 off" protocol is a carefully calibrated biological handshake. It harnesses the power of thermodynamics to throttle inflammation and dull acute pain, while respecting the delicate thresholds of human tissue to prevent frostbite and the paradoxical rebound of blood flow known as the Hunting Response.
What is a climate zone in building regulations?
In construction and energy standards (such as building regulations and thermal performance guidelines), regions are categorized into specific climate zones—often designated as H1, H2, and H3.
How do H2 and H3 zones differ from one another?
The H2 zone typically represents regions with a moderate, temperate climate where winter heating needs are balanced, whereas the H3 zone covers warmer Mediterranean areas.