Introduction: The Hidden Global Crisis
To modern citizens in high-income nations, acute gastroenteritis—commonly referred to as diarrhea—is typically viewed as an inconvenient, short-lived, and self-limiting affliction. Most individuals expect to recover within a few days with minimal intervention beyond rest, hydration, and over-the-counter remedies. However, on a global scale, diarrheal disease represents a vastly different reality. It is a formidable, systemic threat that claims hundreds of thousands of lives annually, acting as a major indicator of global health disparities, socioeconomic inequality, and infrastructure deficits.
When examining the question of who has died from diarrhea, the epidemiological data points starkly toward specific demographics: young children in low-resource settings, immunocompromised individuals, elderly populations in crisis regions, and communities stripped of basic human necessities like clean water, sanitation, and hygiene (WASH) infrastructure.
This first part of our comprehensive expert analysis explores the macro-level statistics, demographic breakdowns, geographical patterns, and systemic risk factors that define the populations most vulnerable to fatal outcomes from diarrheal diseases.
The Scale of the Crisis: Global Mortality Metrics
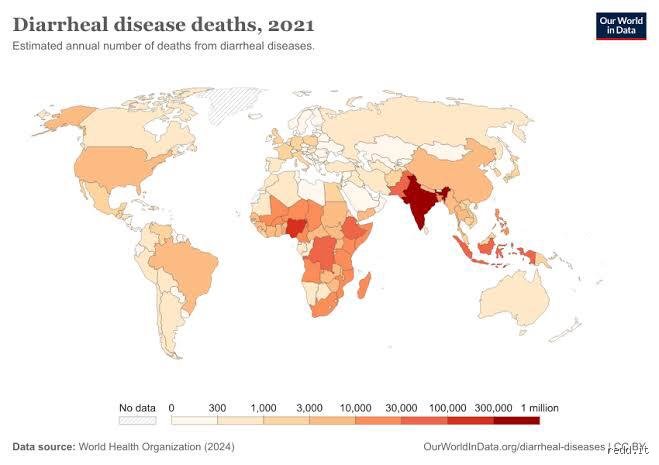
To understand the demographics of those who perish, one must first grasp the sheer magnitude of the global burden. According to data compiled by public health authorities such as the World Health Organization (WHO) and UNICEF, diarrheal diseases consistently rank among the leading causes of morbidity and mortality worldwide.
Across all age groups, over a million deaths are attributed to diarrheal diseases each year.
The primary mechanism of death from acute diarrhea is not the infection itself, but the rapid, profound loss of fluids and electrolytes leading to severe hypovolemic shock and multi-organ failure. When access to clean drinking water or medical-grade rehydration fluids is absent, a severe bout of gastroenteritis can prove fatal within a matter of hours.
Primary Demographic Focus: Children Under Five
The single most heavily impacted demographic group is young children, particularly infants and toddlers under the age of five.
1. Infants and Toddlers (Ages 0 to 59 Months)
The WHO and UNICEF data indicate that hundreds of thousands of children under five die from diarrheal diseases annually.
The Neonatal and Post-Neonatal Vulnerability: Infants under one year of age face elevated risks because their immune systems are immature, and their smaller body mass means they can succumb to dehydration much faster than adults.
The Malnutrition-Infection Cycle: A critical dynamic among young victims is the vicious cycle between diarrhea and malnutrition. Repeated episodes of diarrhea strip the child's body of essential nutrients, leading to stunting and wasting. Conversely, a malnourished child has a compromised intestinal lining and a weaker immune system, making subsequent bouts of diarrhea far more severe and likely to result in death.
2. Early Childhood (Ages 5 to 9)
While the risk drops significantly after a child's fifth birthday as their immune system matures and physiological resilience increases, a notable number of children aged 5 to 9 still succumb to severe diarrheal pathogens—typically in settings characterized by ongoing humanitarian crises, natural disasters, or complete lack of potable water systems.
Geographic and Socioeconomic Disparities
The mortality profile of diarrhea is tightly coupled with geography and socioeconomic status. Death from diarrhea is overwhelmingly a disease of poverty.
Sub-Saharan Africa and South Asia: These two regions bear the heaviest burden of childhood diarrhea mortality. Disparities in healthcare access, medical infrastructure, and water purity mean that children born in these regions are exponentially more likely to experience fatal outcomes from treatable pathogens than their peers in Europe or North America.
Rural versus Urban Divides: Even within developing nations, mortality rates are starkly higher in rural and peri-urban informal settlements (slums). These areas often lack municipal water grids, forcing populations to rely on untreated surface water or contaminated shallow wells.
High-Risk Medical Subgroups Across All Ages
Beyond young children in developing regions, several distinct clinical subgroups face a dramatically elevated risk of death from diarrhea regardless of geographic location:
1. Immunocompromised Individuals (HIV/AIDS and Oncology Patients)
For individuals with compromised immune systems, common enteric pathogens (such as Cryptosporidium, Microsporidia, Isospora, and atypical strains of E. coli) can cause chronic, unyielding, and ultimately fatal diarrhea.
Historical data shows that before the widespread availability of antiretroviral therapy (ART), chronic diarrhea ("slim disease") was one of the most common terminal manifestations of advanced HIV/AIDS.
Even today, individuals with untreated HIV suffer from diarrhea mortality rates many times higher than the general population.
2. The Elderly and Frail Populations
Older adults, particularly those residing in long-term care facilities or in areas affected by infrastructure collapse, are highly susceptible to severe complications from bacterial and viral outbreaks (such as Clostridioides difficile or Norovirus). Reduced baseline physiological reserve, chronic kidney disease, and cardiovascular vulnerabilities make elderly patients much less tolerant of acute electrolyte shifts caused by severe fluid loss.
Pathogens Most Frequently Associated with Fatal Outcomes
While many microorganisms can cause loose stools, a select few are responsible for the vast majority of fatal cases worldwide:
Rotavirus: Historically the leading cause of severe, dehydrating diarrhea in infants globally before the introduction of rotavirus vaccines.
Escherichia coli (Pathogenic strains like ETEC): A primary driver of traveler's diarrhea and endemic childhood diarrhea in developing nations.
Vibrio cholerae: The causative agent of cholera, capable of inducing massive, fatal fluid loss (up to a liter per hour) through "rice-water" stools, leading to death within hours if untreated.
Shigella species: Responsible for bacillary dysentery, characterized by bloody stools, high fever, and systemic toxicity, carrying a high case-fatality rate in malnourished children.
Cryptosporidium: A parasitic infection that poses life-threatening risks to infants and immunocompromised persons due to the lack of completely effective broad-spectrum pharmaceutical cures.
Conclusion of Part 1
The question of who dies from diarrhea opens a window into the stark inequalities of global public health. Far from being a simple domestic inconvenience, fatal diarrhea targets the most defenseless populations among us: infants in impoverished regions, children trapped in cycles of malnutrition, and individuals with weakened immune defenses.
In the second part of this expert analysis, we will examine the physiological mechanisms of how dehydration kills, the systemic failures in medical intervention, and the proven public health strategies—ranging from sanitation infrastructure to modern vaccines—that are actively working to eliminate preventable deaths from diarrheal diseases.
What specific aspect of global diarrheal prevention or treatment protocols would you like to explore further in the upcoming sections?
<h2>Common mistakes and stubborn misconceptions</h2> <p>Let's be clear from the start: perfection is a toxic trap. (We have all fallen prey to its sleek promises at some point.) You seriously believe you need every single condition perfectly aligned before taking a single step. Yet, messy reality laughs out loud at your meticulous spreadsheets. Why do we constantly sabotage our own budding momentum? The problem is an unhealthy obsession with flawless execution rather than embracing messy, iterative progress. Which explains why digital folders fill up with unexecuted masterplans while actual, breathing skills quietly gather digital dust.</p> <h3>Believing intensity beats consistency</h3> <p>You decide to completely overhaul your entire routine, burning out within three days of frantic, unsustainable effort. As a result: total exhaustion follows closely behind, killing any lingering enthusiasm. But true longevity matters infinitely more than short-lived heroics. The issue remains that cinematic overnight transformations only happen in Hollywood scripts, not in the real world.</p> <h3>Ignoring the inevitable plateau phase</h3> <p>Stagnation terrifies most learners, making them abandon ship right when the groundwork is finally taking root. Except that flat lines are mandatory biological and psychological markers of actual, deep-seated growth. In short, if you refuse to tolerate the boring stretches of practice, you will never witness the breakthrough.</p> <h3>Chasing shiny objects and endless tools</h3> <p>Buying another productivity app feels like actual work. Because dopamine tricks your brain into thinking you are making progress when you are merely procrastinating in style. We admit our own weakness here; fancy software cannot fix a lack of raw discipline.</p>