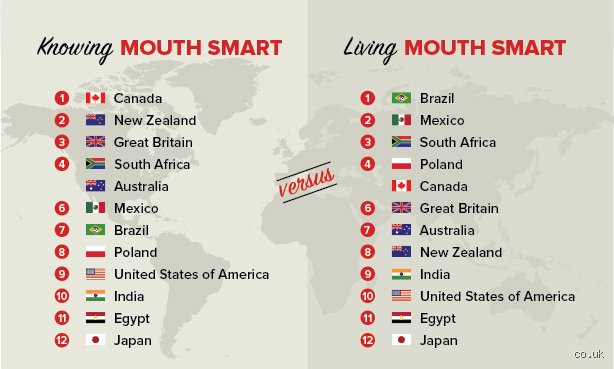
Strictly speaking, no sovereign nation exists where tooth-cleaning habits are entirely non-existent. Humans have engaged in some form of oral hygiene for thousands of years, utilizing primitiveToothbrushing is widely regarded as a cornerstone of modern personal hygiene, deeply ingrained in daily routines across much of the industrialized world. From a very young age, children in many nations are taught that brushing twice a day with fluoride toothpaste is essential for maintaining oral health, preventing cavities, and ensuring fresh breath. However, when examining global public health statistics, cultural practices, and socio-economic disparities, the assumption that everyone brushes their teeth—or even has access to a toothbrush—becomes problematic. In reality, oral hygiene practices vary dramatically across the globe.
To answer the question of "how many countries don't brush their teeth," it is first necessary to correct a common misconception: countries as a whole do not "not brush." Rather, oral hygiene habits differ significantly across populations, influenced by factors such as economic development, geographic isolation, access to clean water, cultural traditions, and the availability of modern dental products. Therefore, rather than pointing to specific nations where toothbrushing is entirely nonexistent, public health researchers examine the prevalence of traditional dental hygiene methods versus modern ones, as well as the segments of global populations that lack access to basic oral care tools.
The Global landscape of Oral hygiene: Modern vs. Traditional practices
When exploring how different societies care for their teeth, anthropologists and public health experts categorize oral hygiene into modern commercial practices and traditional, indigenous methods. The absence of a plastic toothbrush and commercial toothpaste does not automatically mean a population neglects its oral health. For centuries, human beings have devised ingenious methods to clean their teeth and gums using materials provided by their local environments.
One of the most widespread traditional oral hygiene tools in the world is the chewing stick, often derived from trees with natural antiseptic, antibacterial, or abrasive properties. In many parts of West Africa, the Middle East, and the Indian subcontinent, the Salvadora persica tree, commonly known as the miswak or siwak, is extensively used. Scientific studies have shown that miswak contains natural compounds such as fluoride, silica, tannins, and resins that help reduce plaque, strengthen tooth enamel, and combat gingivitis. For millions of people in these regions, the miswak is not a primitive fallback, but a culturally preferred, highly effective method of maintaining oral hygiene.
Similarly, in various rural parts of Asia, Africa, and South America, people utilize twigs from specific trees, charcoal powder, ash, neem branches, or salt mixtures to clean their teeth. While these methods lack the fluoride concentration found in modern commercial toothpastes, which is a critical component in the widespread prevention of dental caries, they nevertheless serve a cleansing and hygienic function. Thus, when assessing global populations who do not use conventional "toothbrushes," it is vital to distinguish between communities that practice traditional hygiene and those with a total absence of dental care.
The impact of Economic disparity and Global poverty
The most significant factor determining whether a population or community lacks access to basic dental hygiene tools is extreme poverty. According to the World Health Organization (WHO), oral diseases are among the most common non-communicable diseases globally, disproportionately affecting vulnerable and disadvantaged populations. In low-income countries, particularly in parts of Sub-Saharan Africa and rural South Asia, commercial toothbrushes and toothpastes represent a recurring financial expense that many impoverished households simply cannot afford.
In extreme poverty, basic survival needs, such as clean drinking water, food security, and shelter, take absolute precedence over preventative health measures like purchasing toothbrushes. When families live on less than a few dollars a day, spending money on personal care products is often out of the question. In many remote or impoverished rural regions, local markets do not stock modern dental products, making them physically inaccessible even for those who might have spare income. Consequently, millions of people worldwide grow up without ever owning a conventional toothbrush, relying instead on whatever natural materials are locally available, or in some cases, experiencing a complete absence of regular dental cleaning.
The World Health Organization and Global Oral Health data
Quantifying the exact number of countries or people who do not brush their teeth is challenging because national censuses rarely track daily toothbrushing habits on a global scale. However, the WHO Global Oral Health Status Report provides profound insights into the state of dental care worldwide. The report highlights that oral diseases affect close to 3.5 billion people worldwide, with three-quarters of those affected living in middle- and low-income countries.
The burden of untreated dental caries (cavities) is particularly high in regions where modern oral hygiene products are scarce and dental healthcare infrastructure is minimal. In many developing nations, the ratio of dentists to the general population can be as low as one dentist per 150,000 people or more, compared to ratios of one per 1,000 to 2,000 in high-income countries. This immense disparity underscores the reality that preventative tools, including toothbrushes and professional dental care, are luxuries rather than universal norms in vast parts of the developing world.
Socioeconomic barriers and Cultural variations in Dental hygiene
Continuing our exploration into global oral health habits, it becomes clear that the phrase## The Global Dental Divide: Infrastructure, Economics, and Cultural Norms
While the introduction to this global exploration established that absolute abstention from oral hygiene is virtually non-existent, as humans across all cultures have historically used twigs, leaves, charcoal, or friction to clear debris from their teeth, the modern concept of brushing with fluoride toothpaste varies dramatically across borders. Rather than asking which countries "do not brush," researchers and global health economists look at the wide disparities in access, prevalence of dental caries, and the socioeconomic barriers that prevent daily preventative care.
To understand the full scope of global dental health, we must examine how economic development, public health infrastructure, and cultural traditions shape oral hygiene habits worldwide.
Economic barriers and the luxury of prevention
In many industrialized nations, brushing twice a day with fluoride toothpaste is an ingrained habit reinforced by decades of public health campaigns, school programs, and readily available commodities. However, in regions grappling with extreme poverty, oral hygiene tools are often viewed through a different lens, one where they compete directly with basic survival needs like clean water, shelter, and food.
The Cost of Commodities
In parts of Sub-Saharan Africa and rural South Asia, commercial toothbrushes and branded toothpaste are imported luxury goods. A single tube of imported toothpaste can represent a significant percentage of a daily household income. Consequently:
Alternative Materials: Populations frequently rely on traditional implements, most notably chew sticks (derived from trees such as the Salvadora persica, commonly known as the Miswak, or neem trees). While these tools are remarkably effective at mechanical plaque removal and often release natural antiseptic compounds, they do not provide the systemic or topical benefits of modern fluoride formulations.
Frequency of Replacement: Where resources are scarce, a single toothbrush or chew stick may be used by multiple family members or retained long past its functional lifespan, rendering the bristles ineffective at disrupting bacterial biofilms.
The absence of public Infrastructure
Public health infrastructure plays a monumental role in national dental habits. In countries lacking fluoridated municipal water systems or community health clinics, preventative care is virtually nonexistent.
Dental Deserts: In rural pockets of developing nations, the ratio of dentists to citizens can be staggering, sometimes one dentist for every 150,000 to 200,000 people.
Treatment vs. Prevention: When professional dental care is geographically and financially out of reach, oral hygiene is rarely prioritized as a preventative measure. Visits to a practitioner typically occur only as a last resort for excruciating pain, which usually means extractions rather than fillings or cleanings.
Cultural traditions and Alternative hygiene practices
It is a common ethnocentric misconception that populations not using Western-style nylon toothbrushes and paste are practicing "no hygiene." In reality, diverse cultures have developed sophisticated indigenous methods for maintaining oral health that have been passed down for generations.
The Miswak and natural pharmacopeia
In the Middle East, parts of North Africa, and the Sahel region, the Miswak stick is not merely a fallback option; it is a preferred cultural and religious practice deeply rooted in tradition.
Scientific Validation: Modern scientific studies have shown that the bark and wood of the Salvadora persica contain naturally occurring substances that inhibit bacterial growth, reduce plaque formation, and strengthen gums.
The Cultural Gap: While these traditional practices successfully manage mechanical cleaning, the absence of fluoride means that the enamel remains significantly more vulnerable to acid-producing bacteria, especially as diets in these regions shift toward processed sugars and refined carbohydrates.
Diet and enamel resilience
Historically, traditional diets low in processed sugars protected many indigenous populations from rampant tooth decay, regardless of their brushing tools. However, globalization and the widespread influx of processed foods, carbonated soft drinks, and refined sugars have disrupted this natural equilibrium.
The Sugar Epidemic: When modern sugary diets meet traditional or absent brushing habits, the results are catastrophic. Communities that historically experienced very low rates of dental decay are now seeing surges in childhood cavities and periodontal disease because their traditional hygiene habits cannot neutralize the onslaught of modern sugars.
Public Health interventions and Global disparities
The World Health Organization (WHO) and various international dental federations track oral health indicators globally, categorizing nations by their DMFT index (Decayed, Missing, and Filled Teeth) at age 12. The data reveals a stark global divide.
| Region / Economic Status | Primary Cleaning Method | Fluoride Access | General DMFT Trends |
|---|---|---|---|
| High-Income Nations (North America, Western Europe, Japan) | Nylon toothbrushes, electric brushes, commercial toothpaste, floss | Ubiquitous (Water fluoridation, high-fluoride pastes) | Declining or stabilized decay rates; high focus on cosmetics and prevention |
| Rapidly Developing Nations (Urban centers in Latin America, Southeast Asia) | Commercial toothbrushes and paste, supplemented by traditional methods | Moderate (Varies by urban vs. rural infrastructure) | Increasing decay rates due to rapid dietary shifts toward processed sugar |
| Low-Income Nations (Rural Sub-Saharan Africa, parts of Central Asia) | Chew sticks, charcoal powder, finger-brushing with water or salt | Low to Non-existent | High rates of untreated caries, periodontal disease, and tooth loss |
The School-Based intervention model
To combat these disparities, successful public health initiatives have moved away from assuming universal access to individual toothbrushes. Programs such as the WHO's FRESH (Focusing Resources on Effective School Health) framework implement supervised daily group brushing in schools using affordable, locally sourced fluoride toothpaste. By shifting the habit into communal and educational spaces, these programs bypass household economic barriers and establish lifelong preventative routines for children.
Reframing the Global narrative
Framing the conversation around whether entire countries "don't brush their teeth" oversimplifies a complex socio-economic and public health reality. Absolute neglect is exceptionally rare; rather, human ingenuity has always driven communities to clean their teeth using whatever materials are available in their environment.
The true crisis is not a cultural aversion to hygiene, but a global inequality in resources. As economic development expands and public health initiatives bring affordable tools and fluoridated products to underserved regions, the gap is slowly narrowing. However, until clean water, basic dental education, and affordable preventative supplies are universal human rights, millions will continue to navigate oral health without the modern tools that high-income nations take for granted.