Exploring the evolution of modern architecture
The rise of functionalism and industrial materials
The genesis of this architectural shift emerged in the early twentieth century, driven by a philosophy where form strictly follows function. Architects began utilizing unprecedented structural mediums like reinforced concrete and structural steel frames, moving away from load-bearing masonry walls. A prime example is the Bauhaus building in Dessau, Germany, completed in 1925 by Walter Gropius. This masterpiece utilized a curtain wall of glass that defied traditional tectonic logic, functioning almost like a crystalline organism filtering light and air. Similarly, the Villa Savoye in Poissy, France, designed by Le Corbusier in 1931, showcased the five points of architecture, floating above the landscape on slender pilotis like an ocean liner resting on green turf.
The Mid-Century expansion and organic integration
By mid-century, the design paradigm evolved to incorporate surrounding landscapes and human scale more fluidly, creating a dialogue between the built environment and nature. The Guggenheim Museum in New York City, designed by Frank Lloyd Wright and opened in 1959, abandoned traditional box-like gallery configurations. Instead, it deployed a continuous spiraling ramp akin to a nautilus shell, redefining how visitors consume spatial narratives. Concurrently, regional variations flourished, merging clean modern lines with local climates and tactile textures.
Modern structures function much like living ecosystems, regulating internal climate and human movement through pure geometry rather than decorative veneer.
These iconic interventions permanently altered global skylines, turning structural engineering into an expressive artistic medium that continues to inspire contemporary design innovation today.
The turning point: Sulfonamides and the first real cures
For centuries, medical practitioners could do little more than watch as bacillary dysentery ran its devastating course through armies, refugee camps, and crowded cities (1.1.1). Mortality rates frequently hovered between twenty and twenty-five percent, with infants and the elderly bearing the heaviest burden (1.1.1, 1.1.4). Even after Kiyoshi Shiga successfully isolated Shigella dysenteriae in 1898 and Simon Flexner identified related strains shortly after, identifying the pathogen did not immediately yield a cure (1.1.1). Patients were subjected to a litany of ineffective, often brutal remedies ranging from heavy metal tonics and opium derivatives to astringents and herbal purges, while the underlying cause of death—rapid, catastrophic dehydration and electrolyte collapse—remained unaddressed.
The paradigm shifted dramatically in the late 1930s and early 1940s with the advent of sulfonamides, the world’s first systemic, broad-spectrum antimicrobial drugs (1.2.3). For the first time in human history, physicians had a pharmaceutical agent that could directly target and suppress bacterial infections within the gastrointestinal tract. During World War II, compounds like sulfadiazine transformed the prognosis of bacillary dysentery (1.1.3), drastically reducing military mortality rates compared to previous global conflicts (1.1.1).
The hydra of Antimicrobial resistance
While sulfonamides and subsequent antibiotics like chloramphenicol, tetracycline, and ampicillin offered a profound breakthrough, they did not permanently vanquish the disease. Bacteria are remarkably adaptable organisms. As broad-spectrum antibiotics became widely deployed across post-war populations and developing regions, Shigella strains rapidly developed resistance mechanisms (1.1.1, 1.1.3).
By the late 1960s and 1970s, multi-drug resistant (MDR) strains of dysentery emerged globally, exemplified by severe epidemics in Central America and South Asia, that shrugged off older, inexpensive antibiotics (1.1.1, 1.1.3). Physicians found themselves in an escalating evolutionary arms race: just as pharmaceutical chemistry synthesized a new class of antimicrobial drug, the pathogen mutated or acquired plasmid-mediated resistance genes, rendering the treatment obsolete. Consequently, relying solely on antibiotics proved to be an incomplete solution, particularly in impoverished regions lacking clean water and sanitation infrastructure.
Oral Rehydration Therapy: Saving millions
While antibiotics attacked the bacteria, patients were still frequently dying from profound hypovolemic shock before the drugs had time to take effect. The definitive turning point in global dysentery survival came not from a pill or an injection, but from a simple physiological realization regarding how the human gut absorbs water and salt.
In the late 1960s, researchers working at the SEATO Cholera Research Laboratory in Dhaka (now ICDDR,B in Bangladesh) unlocked a breakthrough: Oral Rehydration Therapy (ORT) (1.2.1, 1.2.2). Scientists demonstrated that the sodium-glucose cotransporter protein in the small intestine remains fully functional even during severe diarrheal illness (1.2.1). By administering a precise, low-cost mixture of glucose, sodium chloride, potassium chloride, and trisodium citrate dissolved in clean water, patients could actively absorb water and electrolytes straight through the intestinal wall, effectively reversing dehydration without requiring complex intravenous setups (1.2.1, 1.2.2).
Celebrated by medical historians as one of the most important medical advancements of the 20th century, ORT transformed dysentery from a terrifying death sentence into a manageable condition. When deployed during humanitarian crises, such as the massive refugee displacement during the 1971 Bangladesh Liberation War, ORT plummeted mortality rates from over 50% down to under 5% (1.2.2).
Modern management and ongoing challenges
Today, curing and managing dysentery relies on a multifaceted, dual-pronged strategy combining precise microbial identification with supportive care:
Targeted Antimicrobial Therapy: When bacillary dysentery is diagnosed, modern physicians utilize targeted antibiotics, most commonly fluoroquinolones (such as ciprofloxacin) or azithromycin, guided by local antimicrobial susceptibility testing to combat emerging resistance patterns (1.1.3).
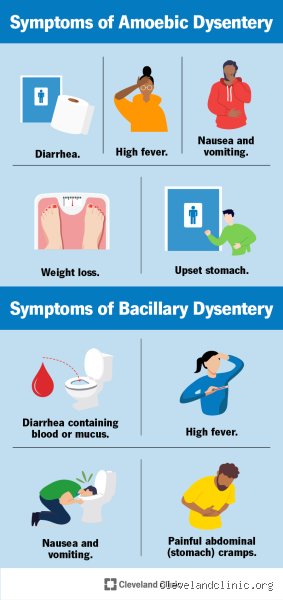
Amoebic Protocols: For amoebic dysentery caused by the parasite Entamoeba histolytica, antibacterial drugs are entirely ineffective; instead, specific amoebicidal medications like metronidazole followed by a luminal agent are required (1.1.2).
Hydration and Nutritional Support: ORT remains the cornerstone of immediate fluid resuscitation, supplemented by micronutrients like zinc (particularly for pediatric patients) to shorten illness duration and strengthen intestinal repair (1.2.1).
Dysentery became curable in stages: pharmacologically in the 1940s with the introduction of sulfonamides (1.1.1), and logistically and globally in the late 1960s through the deployment of oral rehydration therapy (1.2.1, 1.2.2). Yet, the disease remains a potent reminder of the fragility of public health, continuing to pose risks in regions affected by poverty, infrastructure collapse, and persistent antimicrobial resistance.
What specific historical outbreak or geographic region would you like to explore next regarding the medical management of gastrointestinal diseases?