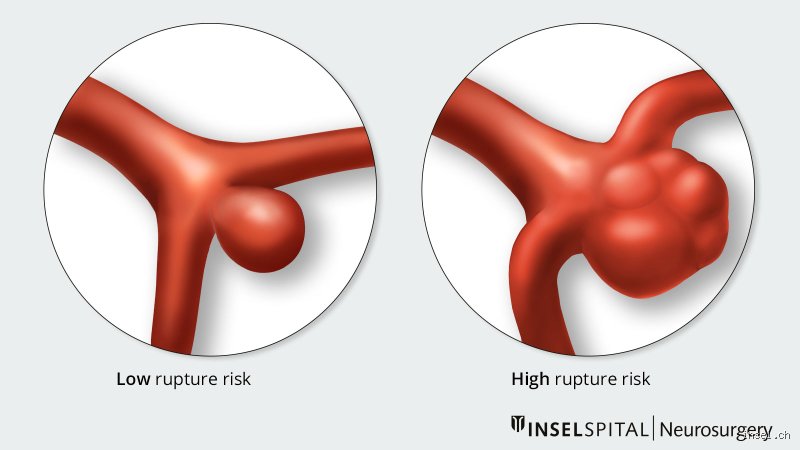
The invisible architecture and hidden dangers
The discovery of an unruptured aneurysm introduces a profound psychological and clinical dilemma for both patients and medical teams. The central question, "Can you treat an unruptured aneurysm?", elicits a nuanced, highly individualized answer. The short response is an unequivocal yes: modern neurosurgery and interventional neuroradiology offer highly sophisticated, minimally invasive, and microsurgical techniques capable of securing or obliterating these vascular lesions before they can rupture. However, the more critical clinical inquiry is not merely can it be treated, but should it be treated?
Balancing the lifetime rupture risk of an unruptured aneurysm against the inherent procedural risks of elective intervention requires a meticulous, multi-disciplinary risk-benefit calculus. This comprehensive guide explores the anatomical nature of UIAs, the diagnostic protocols used to evaluate them, the established thresholds for intervention, and the cutting-edge therapeutic modalities available in modern medicine.
Part I: Understanding the anatomy and pathology of UIAs
To comprehend how unruptured aneurysms are managed, one must first understand how they form, where they typically reside, and why their structural composition dictates their clinical behavior.
1.1 Vascular Pathophysiology
Cerebral arteries differ from other systemic blood vessels. They possess a significantly thinner tunica media (the middle muscular layer of the vessel wall) and lack an external elastic lamina. The brain's major feeding arteries navigate through the subarachnoid space, suspended in cerebrospinal fluid rather than being firmly anchored in dense connective tissue.
Aneurysms predominantly develop at arterial bifurcations, the branching points of the circle of Willis at the base of the brain. At these junctions, hemodynamic stress, chronic hypertension, turbulent blood flow, and localized wall shear stress induce gradual degradation of the internal elastic lamina and smooth muscle cells. Over time, the vessel wall thaws under this relentless mechanical pressure, forming a localized outpouching.
1.2 Morphological Classifications
UIAs vary significantly in shape, size, and anatomical configuration, all of which heavily influence rupture vulnerability:
Saccular Aneurysms ("Berry Aneurysms"): The most common type, accounting for the vast majority of intracranial aneurysms. They resemble spherical or multilobed berries attached to the parent artery by a distinct "neck."
Fusiform Aneurysms: Characterized by a circumferential widening and elongation of the parent vessel segment without a distinct neck. These are typically atherosclerotic or dolichoectatic in origin and present distinct surgical challenges.
Mycotic and Traumatic Aneurysms: Less common types resulting from infection-induced wall weakening or direct physical trauma, respectively.
1.3 epidemiological context and prevalence
Autopsy and advanced neuroimaging studies indicate that unruptured intracranial aneurysms affect roughly 3% to 5% of the general population. Despite this relatively high prevalence, the vast majority of UIAs never rupture during a person's lifetime. The annual rupture rate for incidental, small (under 7 millimeters) anterior circulation aneurysms is historically low, often estimated between 0.05% and 1% per year. However, cumulative lifetime risk, combined with specific high-risk morphological or clinical markers, transforms an incidental finding into a condition requiring rigorous medical surveillance or definitive intervention.
Part II: Risk stratification – who needs treatment?
Because every intervention carries a baseline risk of procedural morbidity and mortality, treating every single unruptured aneurysm is neither clinically sound nor practical. Neurosurgeons, interventional neuroradiologists, and vascular neurologists rely on comprehensive risk stratification models, most notably derived from landmark international studies such as the ISUIA (International Study of Unruptured Intracranial Aneurysms) and the PHASES score, to determine whether the natural history risk of the aneurysm outweighs the treatment risk.
2.1 key determinants of rupture Risk
When evaluating an unruptured aneurysm, clinicians examine a constellation of anatomical, clinical, and demographic risk factors:
| Risk Factor Category | High-Risk Characteristics | Lower-Risk Characteristics |
|---|---|---|
| Size & Geometry | Size ≥7 mm, high aspect ratio (height-to-neck ratio), daughter blebs, irregular contours | Size <5 mm, smooth, regular spherical morphology |
| Anatomical Location | Posterior circulation (basilar apex, vertebral artery) and posterior communicating artery | Internal carotid artery (cavernous/paraclinoid) and middle cerebral artery branches |
| Clinical History | Personal history of prior subarachnoid hemorrhage from another aneurysm, active cigarette smoking, poorly controlled chronic hypertension | No prior aneurysm rupture, non-smoker, well-controlled blood pressure |
| Genetics & Connective Tissue | Autosomal dominant polycystic kidney disease (ADPKD), Ehlers-Danlos syndrome type IV, Marfan syndrome, strong family history (≥2 affected first-degree relatives) | Sporadic presentation with no family history of cerebrovascular disease |
2.2 the PHASES scoring system
To provide an individualized, evidence-based estimate of 5-year rupture risk, modern clinical practice frequently utilizes the PHASES score, which integrates:
Population (North American, European, vs. Japanese/Finnish cohorts)
Hypertension status
Age of the patient
Size of the aneurysm
Earlier history of subarachnoid hemorrhage from another site
Site (location) of the aneurysm
By summing these weighted variables, clinicians can generate a concrete percentage representing the patient's specific 5-year rupture probability, guiding the shared decision-making process between conservative observation and proactive intervention.
Part III: Diagnostic evaluation and imaging modalities
Before any treatment strategy can be formulated, precise characterization of the aneurysm's architecture, relation to adjacent cranial nerves, and parent vessel dynamics is mandatory.
3.1 Non-Invasive screening: CTA and MRA
Computed Tomography Angiography (CTA): Utilizing rapid intravenous contrast injection and high-resolution multi-detector CT scanners, CTA provides exceptional spatial resolution for bony landmarks and vascular anatomy. It is frequently the first-line imaging modality in emergency settings and is exceptionally reliable for detecting aneurysms down to 2–3 millimeters.
Magnetic Resonance Angiography (MRA): Utilizing time-of-flight (TOF) sequences without the need for exogenous gadolinium contrast, MRA is ideal for serial non-invasive surveillance of small, untreated UIAs over time, eliminating cumulative radiation exposure.
3.2 the gold standard: Digital Subtraction Angiography (DSA)
Despite the utility of cross-sectional imaging, Digital Subtraction Angiography (DSA) remains the definitive diagnostic gold standard. Performed via catheter angiography, typically accessing the femoral or radial artery, DSA offers real-time hemodynamic visualization, sub-millimeter spatial resolution, and dynamic assessment of collateral flow. This imaging modality is crucial for surgical and endovascular planning, accurately delineating the exact dimensions of the aneurysm neck, its orientation relative to perforating vessels, and the presence of any associated vasospasm or structural irregularities.
Part IV: Therapeutic options for Unruptured Aneurysms
Once a clinical consensus establishes that an unruptured aneurysm warrants treatment, the therapeutic arsenal bifurcates into two primary modalities: endovascular (catheter-based) interventions and open surgical microsurgery. Over the past three decades, endovascular techniques have evolved from simple coil embolization into highly sophisticated reconstructive and deconstructive technologies, shifting the paradigm of neurovascular care.
4.1 Endovascular interventions (minimally invasive approaches)
Endovascular techniques are performed entirely from within the lumen of the blood vessels, typically accessed via a microcatheter introduced through the femoral or radial artery under general anesthesia or conscious sedation.
Endovascular Coil Embolization: The pioneer of modern endovascular aneurysm treatment, coiling involves navigating a microcatheter directly into the aneurysm sac and packing it with detachable platinum microcoils. These coils induce localized thrombosis within the sac, permanently excluding the aneurysm from the active blood circulation. Coiling is particularly favored for elderly patients, aneurysms located in deep or difficult-to-reach surgical locations (such as the basilar apex), and patients with significant medical comorbidities.
Balloon-Assisted and Stent-Assisted Coiling: For wide-necked aneurysms where standard coils might herniate back into the parent artery, interventionalists utilize adjunct devices. Balloon-assisted coiling temporarily inflates a compliant balloon across the neck during coil deployment to maintain patency. Stent-assisted coiling deploys an intracranial microstent across the neck to act as a permanent scaffold, retaining coils within the sac while preserving blood flow through the main vessel.
Flow Diversion (Endoluminal Reconstruction): A revolutionary advancement in vascular neurosurgery, flow diverters are ultra-dense, braided metallic mesh tubes deployed within the parent artery across the aneurysm neck. Rather than entering the aneurysm sac, the flow diverter mechanically redirects blood flow straight down the parent vessel, dampening intra-aneurysmal hemodynamic pressure. This stagnant flow environment inside the sac promotes progressive, natural thrombosis and subsequent endothelialization (healing) of the parent artery wall over months. Flow diversion has transformed the management of complex, giant, wide-necked, or fusiform UIAs that were previously untreatable or carried prohibitively high surgical risks.
Intrasaccular Flow Disruption: More recent innovations include web-like devices (such as the WOLF or Woven EndoBridge system) placed directly inside wide-necked bifurcation aneurysms to disrupt inflow and encourage intra-sac thrombosis without requiring systemic stenting or dual antiplatelet therapy.
4.2 open Surgical microsurgery (Surgical Clipping)
While endovascular techniques have gained widespread prevalence, open microsurgical clipping remains a cornerstone of cerebrovascular neurosurgery, offering superior long-term durability rates in specific anatomical subsets.
Micro-Surgical Clipping: Performed via a craniotomy (surgical opening of the skull), the neurosurgeon navigates through the subarachnoid spaces using an operating microscope to expose the base of the aneurysm. A specialized, spring-loaded titanium clip is placed directly across the aneurysm neck, permanently occluding blood flow into the sac while preserving the lumen of the parent artery.
Anatomical Suitability and Advantages: Surgical clipping is frequently selected for young patients with long life expectancies (due to its exceptional long-term durability and lower recurrence rates compared to coiling), middle cerebral artery (MCA) aneurysms (which often feature complex branching anatomy well-suited for direct visualization), and aneurysms with mass effect causing compression on adjacent cranial nerves (where surgical decompression of the nerve can be performed concurrently).
Complex Surgical Adjuncts: In cases of exceptionally complex or giant aneurysms, open surgery may involve vascular bypass procedures (e.g., superficial temporal artery to middle cerebral artery bypass) or proximal parent artery occlusion/sac excision.
Part v: Conservative management and lifestyle modification
Not all unruptured aneurysms require immediate intervention. For small, low-risk UIAs, a strategy of conservative surveillance combined with rigorous risk-factor modification is often the most prudent clinical pathway.
5.1 the role of medical management
Hypertension Control: Chronic high blood pressure exerts continuous mechanical wall stress on the cerebral vasculature. Strict pharmacological blood pressure control is the single most effective modifiable intervention to reduce rupture risk in patients with untreated UIAs.
Smoking Cessation: Cigarette smoking promotes chronic systemic inflammation, endothelial dysfunction, and vascular degeneration. Cessation is aggressively counseled for all patients harboring intracranial aneurysms.
Substance and Stimulant Regulation: The avoidance of illicit sympathomimetic stimulants (such as cocaine or high-dose amphetamines), which trigger acute, dangerous spikes in systemic blood pressure, is critical.
5.2 Surveillance Protocols
When an aneurysm is managed conservatively, serial imaging (typically via non-invasive MRA or CTA) is scheduled at predetermined intervals (e.g., 6 months post-initial discovery, then annually or biennially) to monitor for interval growth, morphological changes, or instability that would trigger a shift toward active intervention.
Conclusion and future directions
The management of an unruptured intracranial aneurysm represents a triumph of modern neurovascular medicine, demanding a sophisticated synthesis of advanced diagnostic imaging, precise hemodynamic risk stratification, and individualized therapeutic selection. Whether through minimally invasive endovascular reconstruction or meticulous open microsurgical clipping, effective treatments exist to neutralize these silent vascular threats before they manifest catastrophically.
As imaging technologies continue to advance with high-resolution 7-Tesla MRI, artificial intelligence-driven hemodynamic modeling, and next-generation biomaterials, the future of UIA management promises even greater precision, lower procedural risks, and increasingly personalized care pathways for patients worldwide.
Evaluating intervention pathways: Surgical Clipping versus Endovascular Coiling
When the clinical consensus leans toward proactive intervention for an unruptured intracranial aneurysm, two primary modalities dominate modern neurosurgical practice: microsurgical clipping and endovascular coiling. Selecting between these methodologies requires a granular evaluation of the aneurysm’s morphology, its anatomical location within the cerebrovascular tree, and the patient’s overall physiological reserve.
Microsurgical Clipping
Pioneered decades ago and continually refined with modern microscopic and neuro-monitoring technologies, microsurgical clipping remains a cornerstone of cerebrovascular treatment.
The Mechanism: The procedure involves a craniotomy, temporarily removing a precise section of the skull, to allow the neurosurgeon to dissect along the arachnoid planes and expose the aneurysm. A specialized metal clip (typically titanium or high-grade alloy) is placed directly across the neck of the aneurysm. This permanently halts blood flow into the sac while preserving patency in the parent artery.
Advantages: Clipping offers exceptional long-term durability, with lower rates of aneurysm recurrence or recanalization over multi-year follow-ups. It is frequently preferred for complex, wide-necked aneurysms or those accompanied by an accessible intracerebral hematoma or specific anatomical configurations (such as middle cerebral artery branches).
Considerations: As an open surgical procedure, it entails a longer physical recovery time, a brief stay in the intensive care unit, and a localized scalp and skull healing period.
Endovascular Coiling
Emerging as a less invasive alternative, endovascular therapy is performed entirely from within the blood vessels, typically utilizing access through the femoral artery in the groin or the radial artery in the wrist.
The Mechanism: Guided by real-time fluoroscopic imaging, a microcatheter is navigated through the tortuous arterial network up into the cerebral vasculature and directly into the aneurysm sac. Detachable, soft platinum coils are deployed into the sac. These coils induce localized thrombosis (blood clotting), effectively sealing off the aneurysm from the main circulation. In more complex cases, supportive devices such as balloons or mesh stents (including flow-diverting structures) may be deployed to retain coils or redirect hemodynamic forces away from the aneurysm neck.
Advantages: Because it avoids a traditional craniotomy, endovascular coiling generally translates to a shorter hospital stay, reduced initial discomfort, and a faster return to baseline daily activities.
Considerations: While minimally invasive, endovascular approaches carry a potential risk of long-term coil compaction or recanalization, occasionally necessitating follow-up imaging or secondary retreatment interventions.
Conservative management and surveillance protocols
For many patients diagnosed with small, incidentally discovered, low-risk unruptured aneurysms, active intervention carries a higher statistical risk profile than watchful waiting. Consequently, structured conservative management paired with rigorous surveillance is a widely endorsed medical strategy.
+-------------------------------------------------------------------------+
| CONSERVATIVE MANAGEMENT ARCHITECTURE |
+-------------------------------------------------------------------------+
│
┌───────────────────────────┴───────────────────────────┐
▼ ▼
┌──────────────────┐ ┌─────────────────┐
| MODIFIABLE RISK | | SURVEILLANCE |
| REDUCTION | | IMAGING MATRIX |
+──────────────────+ +─────────────────┤
| • Strict BP Ctrl | | • Baseline MRA |
| • Smoking Cess. | | • 6-12 Mo. Scan |
| • Diet & Exercise| | • Annual/Bien. |
+──────────────────+ +─────────────────┘
Modifiable Risk Factor mitigation
The physiological stress placed on an unruptured aneurysm wall is directly linked to systemic hemodynamics and vessel wall integrity. Clinical guidelines emphasize two primary modifiable targets:
Hypertension Control: Maintaining strict, consistent control over blood pressure minimizes repetitive hydrostatic stress on the fragile aneurysm dome.
Smoking Cessation: Tobacco use damages endothelial linings, accelerates atherosclerosis, and independently increases both the formation and rupture risk of intracranial aneurysms. Total cessation is a clinical imperative.
Imaging surveillance schedules
When a patient and their clinical team choose observation, serial non-invasive imaging is deployed to track stability. Magnetic Resonance Angiography (MRA) or Computed Tomography Angiography (CTA) is typically scheduled at 6 to 12 months post-diagnosis, followed by periodic intervals (such as annually or biennially) if the lesion remains stable. Any documented morphological change, interval growth, or development of new symptoms prompts a re-evaluation for potential surgical or endovascular intervention.
Balancing Personal factors and Long-Term outlook
Answering whether you can treat an unruptured aneurysm involves navigating a complex spectrum of medical probabilities. Treatment is entirely possible and often highly successful, but it is never a one-size-fits-all prescription. The decision-making framework relies on synthesizing quantifiable risk calculators (such as PHASES scores), morphological indicators, multidisciplinary neurosurgical expertise, and individual patient values.
Whether a patient embarks on a path of careful monitoring or undergoes targeted interventional repair, modern neurovascular medicine provides robust pathways designed to safeguard neurological health, mitigate catastrophic risks, and secure long-term well-being.