The Double-Edged sword of host defense
However, viewing inflammation as a monolithic block fails to capture its sophisticated orchestration. Acute inflammation is not a chaotic flare-up; it is a meticulously regulated, highly ordered biological sequence. To truly understand how the body defends, repairs, and restores homeostasis, medical science breaks down this acute response into four distinct stages: Initiation, Amplification, Destruction, and Termination (Resolution).
In this comprehensive first part of our exploration, we will dissect the foundational framework of inflammation, examine the historical and physiological context of the classic cardinal signs, and dive deep into the first two stages—Initiation and Amplification, uncovering the molecular and vascular mechanisms that transform a silent microscopic injury into a vibrant, active immune theater.
The pathophysiological foundations: Why the body inflames
Before examining the sequential stages, it is essential to establish what triggers this cascade and why it manifests the way it does. The primary goals of acute inflammation are threefold:
To wall off the injured or infected site, preventing the systemic spread of pathogens or toxins.
To clear out necrotic (dead) tissue, foreign debris, and invading microorganisms.
To pave the way for tissue repair, regeneration, and functional restoration.
For centuries, medical practitioners have recognized the external manifestation of this process through the five cardinal signs of inflammation (four originally cataloged by Aulus Cornelius Celsus in the 1st century AD, with the fifth added later by Rudolf Virchow):
Rubor (Redness): Caused by the engorgement of local capillaries with blood due to intense vasodilation.
Calor (Heat): The localized increase in temperature resulting from the increased influx of warm blood from the body’s core.
Tumor (Swelling / Edema): The accumulation of fluid and cellular exudate in the interstitial spaces due to altered vascular permeability.
Dolor (Pain): The mechanical stretching of tissue and chemical stimulation of local nociceptors (pain receptors) by mediators like bradykinin and prostaglandins.
Functio Laesa (Loss of Function): The ultimate behavioral adaptation where pain and physical swelling force the organism to rest the affected part, protecting it from further damage.
These signs are not random symptoms of disease; they are the external signatures of microscopic warfare unfolding across four precise phases.
Stage 1: The Initiation Phase (detection and the microvascular alarm)
The inflammatory journey begins the exact microsecond tissue integrity is breached or foreign entities are detected. The Initiation Phase is defined by the immediate recognition of danger signals and the rapid conversion of a passive tissue matrix into an active signaling center.
Sentinel Cells and PAMPs/DAMPs
Residing quietly within every healthy tissue are specialized sentinel cells, primarily mast cells, tissue-resident macrophages, and dendritic cells. These cells act as the body’s border patrol. They are heavily equipped with pattern recognition receptors (PRRs), such as Toll-like receptors (TLRs), which are fine-tuned to recognize two major classes of molecular signatures:
PAMPs (Pathogen-Associated Molecular Patterns): Universal molecular structures found on microbes, such as bacterial lipopolysaccharides (LPS) or viral nucleic acids.
DAMPs (Damage-Associated Molecular Patterns): Internal molecules released by stressed, dying, or ruptured host cells (e.g., nuclear proteins, extracellular matrix fragments, or intracellular ATP).
When a mechanical trauma or infection ruptures cell membranes, DAMPs and/or PAMPs flood the local microenvironment. Sentinel cells bind these molecules, instantly shifting from a resting state to an activated, pro-inflammatory phenotype.
The immediate vascular shift
Upon activation, mast cells undergo a process called degranulation, violently discharging pre-formed chemical mediators stored within their cytoplasmic granules. The most prominent of these initial mediators is histamine, alongside serotonin and early-stage cytokines (such as Tumor Necrosis Factor-alpha [TNF-α\alphaα] and Interleukin-1 [IL-1]).
Histamine acts directly on the smooth muscle cells lining local blood vessels, specifically targeting arterioles and post-capillary venules. This triggers a swift, brief microvascular reaction:
Transient Vasoconstriction: Lasting mere seconds, the local vessels constrict momentarily to minimize immediate blood loss.
Pronounced Vasodilation: Following this brief pause, smooth muscle relaxation causes the arterioles to dilate widely, opening up previously dormant capillary beds. This sudden surge of blood inflow accounts directly for rubor (redness) and calor (heat).
As blood flow slows down in the expanded capillary network (a phenomenon known as hemodynamic stasis), the stage is expertly set for the next phase of the cascade.
Stage 2: The Amplification Phase (vascular permeability and leukocyte recruitment)
With the initial alarm sounded and blood flow redirected to the battleground, the inflammatory response rapidly scales up. The Amplification Phase bridges the gap between simple vascular changes and a full-scale cellular mobilization.
Altering vascular permeability and exudate formation
Vasodilation alone is not enough; the immune system needs its microscopic combatants, white blood cells (leukocytes), to cross from the inside of blood vessels out into the infected or injured tissue interstitium. To achieve this, the physical architecture of the blood vessel wall must be modified.
Chemical mediators, including histamine, leukotrienes, bradykinin, and activated complement proteins (such as C3a and C5a), act on the endothelial cells that line the blood vessels. These mediators cause the endothelial cells to contract and pull apart from one another, creating intercellular gaps in the post-capillary venules.
This dramatic spike in vascular permeability allows protein-rich fluid (known as an exudate) to leak out of the intravascular space into the surrounding tissue. The loss of fluid concentrates the remaining blood cells inside the vessel (increasing blood viscosity), while the leaked fluid in the tissue creates the classic tumor (swelling) and triggers dolor (pain) by physically compressing local nerve endings and exposing them to sensitizing chemicals like prostaglandins.
The cellular recruitment cascade: Margination, rolling, and Adhesion
Simultaneously, the cellular phase of amplification begins. Normally, blood cells (primarily erythrocytes and leukocytes) flow rapidly down the center of blood vessels in a streamlined axial column. As fluid leaks out during inflammation and blood flow slows (stasis), a brilliant logistical choreography unfolds:
Margination: Leukocytes are pushed out of the central stream and toward the inner walls of the endothelium.
Rolling: Specialized adhesion molecules on endothelial cells (such as selectins) transiently grab onto complementary ligands on the surface of leukocytes, causing the white blood cells to tumble or "roll" slowly along the inner vessel wall.
Firm Adhesion: As rolling slows the leukocytes down, chemokines activate integrins on the leukocyte surface. These integrins lock firmly onto adhesion molecules expressed on the activated endothelium, bringing the leukocyte to a complete standstill.
Diapedesis (Emigration): Firmly anchored, the leukocyte extends pseudopods and squeezes itself between the tight junctions of the endothelial cells, exiting the blood vessel and entering the interstitial tissue matrix. Guided by a trail of chemical scent molecules, a process known as chemotaxis, these cells march directly toward the epicenter of the injury.
The primary cellular vanguard of this wave is the neutrophil, a voracious, short-lived phagocyte designed to arrive rapidly and neutralize immediate threats.
Looking ahead to part 2
At this juncture, having successfully detected the injury, sounded the vascular alarm, increased local permeability, and ushered an army of neutrophils into the tissue matrix, the body is fully prepared to enter the third stage: Destruction.
In the upcoming second part of our expert analysis, we will explore how these recruited neutrophils and secondary macrophages execute targeted phagocytosis, deploy reactive oxygen species and enzymatic weapons to eradicate pathogens, and how the inflammatory cascade eventually pivots toward resolution and tissue remodeling.
Anatomical Overview of the Inflammatory Response
This video provides a helpful visual overview of how the body initiates the inflammatory response following tissue damage.
As an expert exploration of the body's dynamic defense mechanism continues, understanding the complete arc of the inflammatory response requires moving beyond the initial alarm bells, vasodilation, increased vascular permeability, and leukocyte recruitment, into the critical phases of clearance, tissue proliferation, and ultimate remodeling.
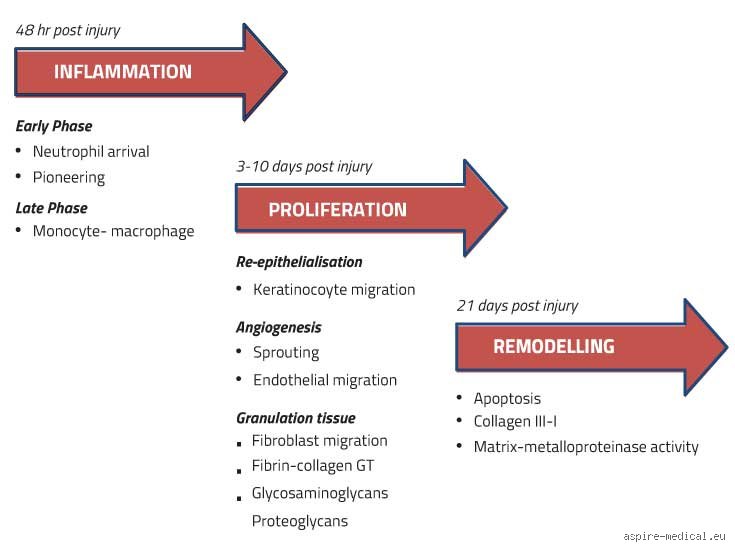
Stage 3: The clearance and proliferative Phase (rebuilding the Matrix)
Once neutrophils and macrophages have infiltrated the site of injury and neutralized the invading pathogens or cleared necrotic debris, the local microenvironment undergoes a profound metabolic shift. This transition is essential to prevent unchecked tissue destruction and lay the groundwork for repair.
1. Phagocytosis and cellular debridement
Neutrophils, which arrive first during the acute phase, have a relatively short lifespan (undergoing apoptosis within 24 to 48 hours). Macrophages succeed them, clearing out apoptotic neutrophils along with foreign particulate matter and damaged extracellular matrix (ECM) components. This clearance is mediated by specialized receptors on macrophages that recognize "eat-me" signals on dying cells.
2. Transition from Pro-Inflammatory to Anti-Inflammatory signaling
To stop the inflammatory cascade from destroying healthy bystander tissue, macrophages undergo a phenotypic switch:
M1 Macrophages (Pro-inflammatory): Dominate early on, releasing cytokines like TNF-α\alphaα, IL-1β1\beta1β, and IL-6 to drive pathogen destruction and recruit more immune cells.
M2 Macrophages (Anti-inflammatory/Repair): Take over during Stage 3, secreting transforming growth factor-beta (TGF-β\betaβ), interleukin-10 (IL-10), and vascular endothelial growth factor (VEGF) to dampen inflammation and stimulate tissue healing.
3. Angiogenesis and granulation tissue formation
With the threat neutralized, the focus shifts to restoring blood supply and structural integrity.
Angiogenesis: Under the influence of VEGF and fibroblast growth factor (FGF), new blood vessels sprout from existing microvasculature to supply oxygen and nutrients to the high-demand healing tissues.
Fibroblast Proliferation: Fibroblasts migrate into the wound bed, proliferating and synthesizing provisional extracellular matrix rich in fibronectin and type III collagen. This creates granulation tissue, characterized by its pink, granular appearance.
Stage 4: Tissue remodeling, Resolution, and fibrosis
The final stage of the inflammatory and healing continuum is remodeling. This phase can last anywhere from weeks to months or even years, depending on the severity and depth of the original injury.
| Aspect | Stage 3: Proliferation | Stage 4: Remodeling & Resolution |
|---|---|---|
| Primary Cells | M2 Macrophages, Fibroblasts, Endothelial cells | Fibroblasts, Myofibroblasts, Mature Macrophages |
| Key Molecules | VEGF, FGF, TGF-β, Type III Collagen | Matrix Metalloproteinases (MMPs), Type I Collagen |
| Structural Goal | Establish vascularized granulation tissue | Restore biomechanical tensile strength |
| Outcome | Provisional matrix filling the defect | Matured extracellular matrix or scar tissue |
1. Collagen maturation and Cross-Linking
During remodeling, the delicate, hastily laid down Type III collagen is progressively degraded by enzymes called matrix metalloproteinases (MMPs) and replaced by much stronger Type I collagen. Myofibroblasts, specialized fibroblasts containing contractile smooth muscle actin, pull the wound edges together (wound contraction), significantly reducing the surface area that needs to be re-epithelialized.
2. Apoptosis of repair Cells
Once the structural defect is filled and tensile strength is recovered, the excess fibroblasts, myofibroblasts, and newly formed blood vessels undergo programmed cell death (apoptosis). The cellular density of the healed tissue returns close to baseline, shifting the tissue from a hyper-cellular repair state back into a quiescent, durable state.
3. Resolution vs. Fibrosis
The ideal outcome of inflammation is complete resolution, where normal architecture and function are entirely restored (e.g., superficial skin scrapes or lobular pneumonia where alveolar architecture is preserved). However, if tissue destruction is extensive, if the inflammatory stimulus persists, or if regenerative capacity is limited, resolution fails. This leads to fibrosis or scarring, where structural integrity is prioritized over functional restoration, resulting in collagen-dense scar tissue (such as in myocardial infarctions or deep dermal burns).
Clinical implications of dysregulated Inflammation
While acute inflammation is a life-saving, tightly orchestrated biological masterpiece, system-wide dysregulation carries severe clinical consequences:
"Inflammation is the common soil of modern disease. When acute responses fail to resolve, they transition into smoldering, chronic states that drive tissue degradation across diverse organ systems."
Chronic Inflammation: Occurs when the triggers cannot be easily eliminated (e.g., persistent infections, autoimmune reactions, or toxic environmental exposures like silica or asbestos). This leads to continuous tissue destruction, ongoing fibrosis, and compromised organ function (seen in rheumatoid arthritis, atherosclerosis, and inflammatory bowel disease).
Systemic Inflammatory Response Syndrome (SIRS) and Sepsis: An exaggerated, unregulated systemic acute inflammatory response where widespread cytokine release leads to capillary leak, profound hypotension, multiple organ dysfunction syndrome (MODS), and potentially fatal shock.
Conclusion
The four stages of inflammation, spanning initial vascular alterations, cellular recruitment, debris clearance, and final tissue remodeling, represent an intricate continuum of biological checks and balances. By understanding how the body signals, attacks, cleans up, and reconstructs itself, medical science continues to develop targeted therapeutics that can halt runaway autoimmune reactions, accelerate wound healing, and mitigate the long-term impacts of chronic inflammatory disease.