Navigating Medication Safety in Lewy Body Dementia: The Hidden Dangers of Standard Prescriptions
When managing a neurodegenerative condition like Lewy body dementia (LBD), finding the right balance of care can feel like walking a tightrope. The symptoms are complex, overlapping, and often unpredictable, shifting between profound cognitive fluctuations, vivid visual hallucinations, and rigid motor difficulties akin to Parkinson's disease. Because these clinical signs mimic other conditions, people don't think about this enough when standard pharmaceutical treatments are prescribed in routine clinical settings. The reality is that prescribing the wrong medication can trigger catastrophic, life-threatening reactions that change everything for patients and their families.
Understanding which pharmaceutical agents to avoid requires a deep dive into the unique neurochemistry of LBD. Unlike Alzheimer's disease, where treatments are tailored primarily to address cholinergic deficits, LBD involves widespread accumulations of alpha-synuclein protein aggregates—known as Lewy bodies—inside the brain's neurons. This pathology severely compromises the dopaminergic and cholinergic pathways. When foreign chemical agents interfere with these fragile systems, the consequences are immediate and severe.
The Looming Threat of Antipsychotic Medications
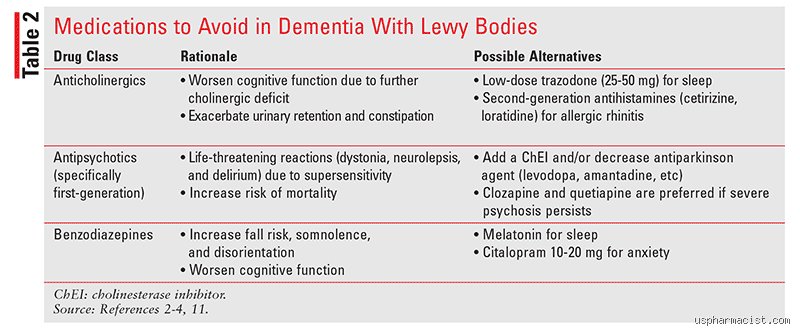
The single most dangerous category of drugs for individuals with LBD comprises neuroleptic agents, commonly referred to as antipsychotics. In many psychiatric disorders or other forms of dementia, standard or atypical antipsychotics are routinely utilized to manage behavioral disturbances, agitation, or psychosis. However, in the context of Lewy body dementia, introducing these drugs can be profoundly hazardous.
Traditional first-generation antipsychotics—such as haloperidol, chlorpromazine, and fluphenazine—work by heavily blocking dopamine D2 receptors in the brain. Because an LBD patient's dopaminergic pathways are already heavily depleted and dysfunctional due to underlying disease pathology, further blocking these receptors triggers severe neuroleptic sensitivity. That is where it gets tricky: even a single standard dose given in an emergency room or surgical ward can precipitate a rapid, terrifying decline. Patients may experience profound catatonia, extreme rigidity, inability to swallow, and devastating motor locking that resembles end-stage Parkinsonism.
Furthermore, this hypersensitivity can culminate in Neuroleptic Malignant Syndrome (NMS), a rare but medical emergency characterized by extreme hyperthermia, autonomic instability, altered mental status, and skeletal muscle breakdown. NMS associated with neuroleptic exposure in LBD can be fatal. Even second-generation (atypical) antipsychotics, which are often marketed as safer alternatives, carry significant risks of severe sedation, accelerated cognitive worsening, and increased mortality rates from stroke. While a select few atypical agents like quetiapine or clozapine are occasionally trialed at the absolute lowest possible dosages under strict specialist supervision, the default clinical stance must remain one of extreme caution.
Anticholinergic Drugs and Everyday Over-The-Counter Hazards
Beyond powerful neuroleptics, a wide array of medications with anticholinergic properties pose a hidden and pervasive threat to individuals living with LBD. Acetylcholine is a neurotransmitter heavily involved in memory, attention, and cognitive alertness. Because LBD inherently strips the brain of its natural cholinergic supply, administering drugs with anticholinergic side effects acts like adding fuel to a fire.
This danger is not restricted to prescription drugs; it frequently lurks in common over-the-counter remedies that families purchase without a second thought. Medications containing diphenhydramine—found in standard allergy formulations, nighttime cold medications, and sleep aids—are notorious for crossing the blood-brain barrier and blocking cholinergic transmission. For an LBD patient, taking a simple over-the-counter antihistamine for a runny nose or insomnia can instantly provoke acute confusional states, severe delirium, worsening hallucinations, and accelerated long-term cognitive decline. Other culprits include certain urinary incontinence medications, older anti-nausea drugs, and tricyclic antidepressants. Caregivers and clinicians must meticulously vet every single substance entering the patient's system, ensuring that hidden anticholinergic burdens do not quietly dismantle day-to-side cognitive stability.
The Hidden Dangers: Other High-Risk Drug Classes
Beyond classic neuroleptics, individuals with Lewy body dementia (LBD) are exceptionally vulnerable to several other pharmacological categories. Navigating these requires strict vigilance from caregivers, primary care doctors, and specialists alike.
1. Anticholinergic Medications
Anticholinergics block acetylcholine, a vital neurotransmitter already severely depleted in the brains of people with LBD.
Common Culprits: Over-the-counter sleep aids (like diphenhydramine), allergy medications, certain urinary incontinence drugs (such as oxybutynin), and tricyclic antidepressants.
The Consequences: Introducing these agents can instantly precipitate acute delirium, profound memory worsening, severe constipation, urinary retention, and blurred vision, rapidly accelerating cognitive decline.
2. Sedatives and Hypnotics (Benzodiazepines and Z-Drugs)
Anxiety and sleep disturbances are common in LBD, but turning to sedatives poses massive risks.
Common Culprits: Benzodiazepines (e.g., lorazepam, diazepam) and non-benzodiazepine sleep aids ("Z-drugs" like zolpidem).
The Consequences: Because patients already experience autonomic instability and balance deficits, these drugs trigger extreme sedation, deep cognitive fog, paradoxical agitation, and a drastically heightened risk of injurious falls and hip fractures.
3. Dopamine-Depleting Antiemetics
Gastrointestinal distress, nausea, and reflux frequently accompany neurodegenerative disorders, but standard remedies can be disastrous.
Common Culprits: Metoclopramide and prochlorperazine.
The Consequences: These antiemetics function by blocking dopamine receptors in the periphery and central nervous system. In an LBD brain, this blockade mimics the catastrophic effects of typical antipsychotics, rapidly provoking severe extrapyramidal symptoms, muscle rigidity, and immobility.
Safe Management Strategies and Best Practices
Managing symptoms in LBD requires prioritizing non-pharmacological interventions first and practicing extreme caution when medications are unavoidable.
+-----------------------------------------------------------------+
% SAFE PRESCRIBING PRINCIPLES %
+-----------------------------------------------------------------+
| * Start Low and Go Slow: Always use minimal therapeutic doses. |
| * Non-Drug First: Environmental modifications for behaviors. |
| * Regular Review: Consistently audit and prune polypharmacy. |
| * Specialist Oversight: Consult a movement disorders expert. |
+-----------------------------------------------------------------+
Navigating Necessary Exceptions
When psychiatric symptoms or movement disorders become entirely unmanageable or dangerous, certain medications may be utilized under strict specialist supervision:
Atypical Antipsychotics: If an antipsychotic is absolutely mandatory for severe psychosis or distress threatening safety, quetiapine or clozapine are generally favored due to their lower affinity for extrapyramidal side effects, though they still demand intense clinical monitoring.
Cholinesterase Inhibitors: Drugs like rivastigmine or donepezil are often utilized to help manage cognitive fluctuations and visual hallucinations.
Parkinsonian Agents: If motor symptoms severely impair daily functioning, low-dose levodopa may be introduced cautiously, keeping in mind that high doses can aggravate hallucinations or confusion.
Conclusion
Understanding which medications to avoid in Lewy body dementia is quite literally a matter of life and safety. Because the neurochemical architecture in LBD is fundamentally fragile—characterized by severe deficits in both acetylcholine and dopamine pathways—introducing incompatible drugs can trigger rapid, catastrophic declines, permanent immobility, or life-threatening hypersensitivity syndromes.
By fostering close collaboration between families, caregivers, and expert neurologists, and by adhering strictly to the mantra to start low, go slow, and question every prescription, we can protect vulnerable patients from avoidable harm and optimize their quality of life.
What specific behavioral or movement symptoms in LBD are you or your care team currently trying to manage safely?