The paradox of micronutrients in neurodegeneration
However, the administration of levodopa is famously fraught with pharmacokinetic challenges, peripheral side effects, and long-term motor complications. To optimize its therapeutic window, levodopa is invariably co-formulated with peripheral aromatic L-amino acid decarboxylase (AADC) inhibitors, such as carbidopa or benserazide. These inhibitors prevent the premature, peripheral conversion of levodopa into dopamine in the bloodstream, ensuring that a sufficient concentration crosses into the central nervous system where it can be converted into the active neurotransmitter.
It is within this delicate biochemical ecosystem that micronutrients—specifically vitamins—exert profound, and sometimes perilous, influences. Among these, Vitamin B6 (pyridoxine and its active coenzyme forms, primarily pyridoxal 5'-phosphate, or PLP) occupies a position of notorious duality. While Vitamin B6 is an essential water-soluble vitamin vital for general human health, cellular metabolism, amino acid transamination, and neurotransmitter synthesis, its unmonitored or excessive intake in patients with Parkinson’s disease can have disastrous clinical consequences.
For decades, movement disorder specialists have cautioned against the indiscriminate supplementation of Vitamin B6 in patients undergoing levodopa therapy. Yet, patients frequently encounter conflicting advice from popular health literature, wellness blogs, and over-the-counter multivitamin marketing that touts B-complex vitamins as universal boosters of energy and neurological health. This first part of our comprehensive expert analysis explores the biochemical architecture of Vitamin B6, its direct interaction with dopaminergic pathways, the historical evolution of clinical findings regarding pyridoxine and levodopa, and the acute risks associated with its concurrent use in Parkinson’s disease management.
The biochemical architecture of Vitamin B6 and its role in neurotransmission
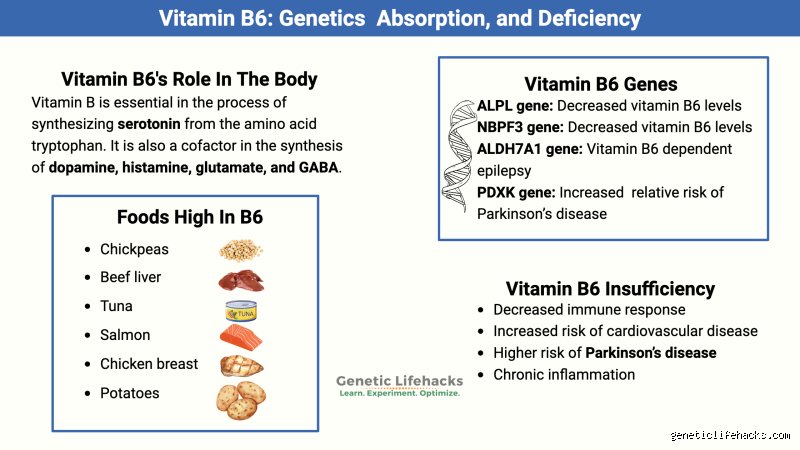
To understand why Vitamin B6 must be managed with extreme caution in Parkinson's disease, one must first examine its physiological functions at the molecular level. Vitamin B6 is not a single chemical entity but rather a collective term for a group of closely related pyridine derivatives: pyridoxine (PN), pyridoxal (PL), and pyridoxamine (PM), along with their respective phosphorylated counterparts. The biologically active coenzyme form is pyridoxal 5'-phosphate (PLP), which serves as a critical cofactor for over 140 enzymatic reactions cataloged in human metabolism, predominantly involving amino acid transformations such as decarboxylation, transamination, racemization, and elimination.
In the central and peripheral nervous systems, PLP plays an indispensable role in the biosynthesis of major neurotransmitters. It acts as an obligatory coenzyme for:
Aromatic L-amino acid decarboxylase (AADC): The enzyme responsible for converting levodopa into dopamine, as well as 5-hydroxytryptophan into serotonin.
Glutamate decarboxylase (GAD): The enzyme that catalyzes the conversion of excitatory glutamate into the primary inhibitory neurotransmitter, gamma-aminobutyric acid (GABA).
Histidine decarboxylase: Essential for the synthesis of histamine.
Tryptophan hydroxylase and other steps in monoamine synthesis pathways.
Given its role as an essential cofactor for AADC, one might intuitively hypothesize that higher levels of Vitamin B6 would enhance dopamine production and therefore benefit patients with Parkinson’s disease. However, this simplistic view ignores the crucial physiological compartmentalization between the peripheral circulation and the central nervous system, as well as the pharmacokinetics of exogenous levodopa therapy.
The Peripheral vs. Central dilemma: How Vitamin B6 sabotages levodopa efficacy
The fundamental reason why Vitamin B6 poses a threat to Parkinson’s disease patients receiving levodopa lies in the site of enzymatic activation. When a patient takes an oral dose of levodopa, it is absorbed in the small intestine and enters the bloodstream. In the absence of a peripheral AADC inhibitor, a vast majority of circulating levodopa is rapidly decarboxylated into dopamine outside the blood-brain barrier by the enzyme AADC.
Because dopamine itself cannot cross the blood-brain barrier efficiently, this peripheral conversion results in two major problems:
Reduced Bioavailability: Only a tiny fraction (typically 1–5%) of the administered levodopa reaches the brain, drastically diminishing its therapeutic antiparkinsonian effect.
Severe Peripheral Side Effects: High concentrations of peripheral dopamine stimulate dopamine receptors in the chemoreceptor trigger zone and the cardiovascular system, triggering severe nausea, vomiting, orthostatic hypotension, and cardiac arrhythmias.
To circumvent this, modern medicine introduced peripheral AADC inhibitors (carbidopa or benserazide). These compounds do not cross the blood-brain barrier in significant amounts; instead, they selectively inhibit peripheral AADC, leaving central AADC free to convert the remaining levodopa into dopamine inside the brain parenchyma.
The catalytic enhancement of Peripheral decarboxylation
Vitamin B6 (specifically as PLP) is the natural coenzyme required for AADC activity. When a patient ingests excessive amounts of Vitamin B6 through high-dose supplements or fortified products, the plasma concentration of PLP rises significantly. This surplus of coenzyme enhances the catalytic efficiency of any uninhibited peripheral AADC enzymes that manage to escape blockade by carbidopa, or it can effectively overwhelm sub-optimal doses of peripheral inhibitors.
Consequently, excess Vitamin B6 accelerates the peripheral decarboxylation of levodopa before it has the opportunity to traverse the blood-brain barrier. The clinical manifestation of this biochemical sabotage is swift and severe:
Rapid Onset of "Wearing-Off" and "Off" Periods: Patients experience a sudden loss of motor control, return of rigidity, bradykinesia, and disabling tremors because insufficient dopamine is being generated within the striatum.
Increased Fluctuations: Motor fluctuations become erratic and unpredictable, severely compromising the patient's daily functioning and quality of life.
Amplified Peripheral Toxicity: With increased peripheral breakdown comes a surge in peripheral dopamine and its metabolites, precipitating severe gastrointestinal distress and hemodynamic instability.
Historical context: The landmark studies and the evolution of clinical guidelines
The antagonistic relationship between Vitamin B6 and levodopa therapy is not a modern theoretical discovery; it has been documented in clinical literature for over half a century. Following the breakthrough introduction of levodopa into clinical neurology in the late 1960s by George Cotzias and colleagues, researchers quickly observed erratic therapeutic responses in patients receiving dietary supplements or multi-vitamins containing pyridoxine.
During the early 1970s, several landmark pharmacological studies investigated the exact mechanics of this interaction. Investigators demonstrated that the intravenous or oral administration of pyridoxine hydrochloride in doses as low as 10 to 25 milligrams could completely reverse the therapeutic benefits of oral levodopa in patients who were not concurrently taking a peripheral decarboxylase inhibitor.
In a classic series of experiments, researchers showed that patients with Parkinson’s disease whose motor symptoms were well-controlled on levodopa experienced a catastrophic relapse of akinesia and rigidity within minutes to hours of receiving supplemental Vitamin B6. This phenomenon was so robust and reproducible that it was initially utilized as a diagnostic challenge or warning indicator in clinical pharmacology.
The advent of combination therapy and residual risks
The introduction of carbidopa-levodopa combination drugs (such as Sinemet) in the 1970s and 1980s significantly mitigated, but did not entirely eliminate, the risk posed by Vitamin B6. Carbidopa acts as a competitive inhibitor of AADC, protecting circulating levodopa. However, the inhibition provided by carbidopa is dose-dependent and saturable.
If a patient consumes massive quantities of Vitamin B6, such as high-potency "megadose" supplements marketed for neuropathy, energy, or general wellness containing 100 mg to 500 mg or more of pyridoxine, the massive influx of coenzyme can partially overcome the competitive block established by carbidopa. Many older or generic formulations of combination therapies, as well as specific dietary regimens, lacked standardized nutritional oversight, leading to inadvertent fluctuations in B6 intake that destabilized patients' finely tuned motor regimens.
Consequently, movement disorder consensus guidelines established a firm clinical rule: routine multivitamin supplementation for Parkinson's disease patients must be carefully scrutinized, and high-dose Vitamin B6 supplements must be strictly avoided unless specifically indicated for a documented deficiency under close neurological supervision.
Acute and chronic clinical consequences of B6-Induced levodopa failure
To fully appreciate why clinicians maintain such vigilance regarding Vitamin B6, one must examine the clinical cascade that occurs when a Parkinson’s disease patient is exposed to excessive pyridoxine. The consequences extend far beyond a temporary inconvenience; they strike at the heart of patient independence and safety.
1. Motor destabilization and Severe akinesia
The most immediate and distressing consequence of B6-induced levodopa antagonism is the sudden resurgence of parkinsonian motor symptoms. For a patient whose mobility depends on precise timing and steady brain levels of dopamine, a sudden drop in central dopamine availability translates into:
Profound Bradykinesia: Complete slowness of movement that can render patients unable to feed, dress, or ambulate independently.
Rigidity and Freezing of Gait: Sudden "freezing" episodes dramatically increase the risk of falls, leading to fractures, head trauma, and subsequent loss of functional independence.
Resting Tremor Breakthrough: Tremors that were previously suppressed return with heightened intensity.
2. The illusion of disease progression
In clinical practice, a sudden worsening of Parkinson's symptoms often triggers alarm bells for both the patient and the physician, raising fears that the underlying neurodegenerative disease has suddenly accelerated or that the current levodopa dosage has permanently failed (tolerance). Patients may undergo unnecessary and aggressive adjustments to their antiparkinsonian medications, such as increasing levodopa frequency or adding dopamine agonists, when the root cause is simply an over-the-counter B-complex vitamin or a newly introduced nutritional shake fortified with pyridoxine. Recognizing dietary and supplemental B6 intake as a confounding variable is therefore a vital diagnostic competency for clinicians.
3. Peripheral autonomic and gastrointestinal distress
Because accelerated peripheral decarboxylation shunts levodopa degradation outside the central nervous system, the peripheral tissues are flooded with dopamine. This manifests clinically as:
Intractable nausea and vomiting.
Epigastric distress and anorexia.
Marked orthostatic hypotension, increasing the incidence of syncopal episodes, dizziness, and fall-related injuries.
Nutritional nuances: Distinguishing dietary intake from megadosing
A common point of confusion for patients and caregivers is whether they must eliminate all foods containing Vitamin B6. It is important to draw a sharp scientific distinction between normal physiological dietary intake and pharmacological megadosing.
Vitamin B6 is naturally present in a wide variety of foods, including poultry, fish, whole grains, potatoes, bananas, and chickpeas. A balanced, whole-food diet provides physiological amounts of pyridoxine that are generally processed efficiently by the body without causing dramatic spikes in plasma PLP that would overwhelm standard carbidopa-levodopa regimens.
The danger arises almost exclusively from:
Over-the-Counter Multivitamins: Many standard adult multivitamins contain 100% to 500% of the Recommended Daily Allowance (RDA) of Vitamin B6. While low-dose standard multivitamins are often well-tolerated by patients taking stable carbidopa-levodopa regimens, cumulative intake from multiple fortified products can creep into problematic ranges.
High-Potency B-Complex Supplements: Supplements marketed for "nerve health," "energy metabolism," "stress reduction," or "peripheral neuropathy" frequently contain massive pharmacological doses of Vitamin B6 (ranging from 50 mg to 500 mg per serving), doses that are hundreds of times higher than the daily physiological requirement (which is typically around 1.3 to 1.7 mg for healthy adults).
Fortified Functional Foods and Energy Drinks: Modern dietary trends have led to the widespread fortification of protein powders, meal replacement shakes, and energy beverages with high levels of B-vitamins, often consuming unsuspecting patients.
Interim summary and transition to part II
As this examination demonstrates, the interaction between Vitamin B6 and Parkinson’s disease management is a textbook example of biochemical antagonism where well-intentioned supplementation can severely compromise clinical stability. By accelerating the peripheral decarboxylation of levodopa, Vitamin B6 robs the brain of its required neurotransmitter precursor, plunging patients back into debilitating motor states and introducing distressing peripheral side effects.
However, the clinical narrative surrounding Vitamin B6 in neurodegeneration does not end with its interaction with levodopa. Beyond its role as an AADC cofactor, Vitamin B6 metabolism intersects with other critical neurochemical pathways, including homocysteine metabolism, oxidative stress, inflammation, and potential neuroprotective or neurotoxic mechanisms independent of levodopa.
In the second part of this expert analysis, we will explore the complex interplay between Vitamin B6, homocysteine, and cardiovascular risk in Parkinson's disease, examine genetic and individual metabolic variations in B6 processing, review clinical management protocols for patients with concurrent nutritional deficiencies, and outline evidence-based guidelines for safe dietary and supplemental practices in movement disorder care.
Common mistakes to avoid when starting out
Starting a new creative project can be exciting, but it is easy to trip over a few common hurdles. Knowing what to watch out for helps you save time and keeps your energy focused on the right things.
Trying to make everything perfect right away
Many beginners spend hours fixing tiny details before the core work is even finished. This habit often leads to burnout and a feeling that you are making no progress. Perfectionism at the early stage stops you from seeing the bigger picture. It is much better to build a rough version first and refine it later.
Skipping the planning phase
Jumping straight into action without a basic roadmap can leave you feeling lost halfway through. You might realize that key pieces do not fit together, forcing you to start over from scratch. Taking a few minutes to outline your thoughts keeps your direction clear and steady.
Ignoring feedback from others
It can be hard to hear criticism, especially when you have put a lot of effort into something. However, fresh eyes often catch mistakes or confusing parts that you missed. Listening to outside perspectives helps you grow much faster than trying to figure everything out entirely on your own.