Introduction: The Quest for Neuroprotection and Symptom Management
When individuals and their families receive a diagnosis of Parkinson's disease (PD), the medical journey immediately centers on established pharmacological mainstays, most notably levodopa and dopamine agonists. However, as patients navigate the complexities of living with a progressive neurodegenerative condition, attention inevitably turns toward complementary strategies that can optimize health, enhance cellular resilience, and potentially alter the trajectory of the disease. Among these, micronutrients and vitamins occupy a place of intense public interest and ongoing scientific scrutiny.
The question of what constitutes the "best" vitamin for Parkinson's disease is deceptively complex. Unlike infectious diseases where a specific deficiency points directly to a single curative agent, Parkinson's disease is a multifaceted disorder characterized by mitochondrial dysfunction, oxidative stress, neuroinflammation, and the pathological aggregation of alpha-synuclein proteins.
Understanding the Landscape: Why Vitamins Matter in Parkinson's Disease
To appreciate why certain vitamins are frequently recommended for individuals with Parkinson's disease, one must first understand how the pathology of the condition intersects with human nutrition. Neurodegeneration within the substantia nigra—the region of the brain responsible for producing dopamine—does not occur in a vacuum. It is heavily influenced by systemic cellular health, metabolic efficiency, and the body's ability to clear toxic byproducts.
1. Oxidative Stress and Mitochondrial Impairment
At the core of Parkinsonian pathology is the breakdown of cellular energy production. Mitochondria, the powerhouses of our cells, begin to malfunction, leading to a surge in reactive oxygen species (oxidative stress) that damages dopaminergic neurons. Vitamins that act as antioxidants or support mitochondrial enzyme complexes have therefore formed the cornerstone of nutritional research in neurology. While high-profile antioxidant trials involving substances like Vitamin E or massive doses of Coenzyme Q10 have yielded mixed or ultimately disappointing results in large-scale clinical trials, the underlying principle remains valid: maintaining adequate cellular defenses is vital.
2. The Intersection of Diet, Absorption, and Medication
People with Parkinson's disease frequently face gastrointestinal challenges, including delayed gastric emptying, dysmotility, and chronic constipation. These physiological hurdles can severely impair the intestinal absorption of vital nutrients. Furthermore, standard pharmacological treatments like levodopa can actively alter metabolic pathways—for instance, increasing the body's demand for or altering the processing of certain B vitamins, which can lead to secondary deficiencies that worsen fatigue, neuropathy, and cognitive slowing.
Therefore, identifying the "best" vitamin often translates to identifying and correcting the specific nutritional vulnerabilities that are statistically or biochemically amplified in the Parkinson's population.
The Leading Contenders: Vitamin B12 and Neurological Health
When clinical literature evaluates which vitamin holds the most robust and clinically relevant association with Parkinson's disease, Vitamin B12 (cobalamin) frequently emerges at the forefront.
The B12 and Homocysteine Connection
Vitamin B12 is essential for maintaining the health of nerve tissues, facilitating neurological function, and producing red blood cells and DNA. In the context of Parkinson's disease, B12 plays a critical role in regulating homocysteine levels. Homocysteine is an amino acid that, when elevated in the blood and cerebrospinal fluid, acts as a potent neurotoxin.
Patients taking levodopa often experience an elevation in homocysteine because the metabolic processing of levodopa (via the enzyme catechol-O-methyltransferase or COMT) utilizes methyl groups donated by SAMe, a process heavily reliant on adequate stores of Vitamin B12 and Vitamin B6. When B12 levels are suboptimal, homocysteine spikes. Elevated homocysteine is independently associated with:
Accelerated cognitive decline and memory impairment
Increased severity of motor symptoms and more rapid disease progression
Peripheral neuropathy, which can dangerously overlap with and compound Parkinson-related balance and gait disturbances
Clinical Insights on B12 Deficiency
Research indicates that a significant percentage of older adults, particularly those with neurodegenerative conditions, suffer from subclinical or overt Vitamin B12 deficiencies.
Vitamin D: Bone Health, Fall Prevention, and Beyond
While Vitamin B12 targets cellular metabolism and homocysteine control, Vitamin D occupies a different yet equally critical tier of management for people with Parkinson's disease. Often referred to as a neurosteroid hormone rather than just a simple vitamin, Vitamin D receptors are densely distributed throughout the human brain, including areas heavily impacted by Parkinson's.
Mitigating Motor Risks and Skeletal Vulnerability
The practical justification for prioritizing Vitamin D in Parkinson's management is profoundly tied to safety and mobility. Parkinson's disease fundamentally impacts balance, posture, and coordination, rendering individuals vulnerable to bradykinesia, freezing episodes, and sudden falls.
When a fall occurs, the presence of underlying osteoporosis or osteopenia drastically increases the likelihood of severe fractures, particularly of the hip. Vitamin D is indispensable for calcium absorption and bone density maintenance. Clinical observations consistently show that individuals with Parkinson's disease have a high prevalence of Vitamin D deficiency, driven by factors such as reduced outdoor mobility, limited sun exposure, and altered metabolism.
Emerging Immunomodulatory and Neuroprotective Roles
Beyond skeletal health, basic science research highlights Vitamin D's role in modulating neuroinflammation. Chronic, low-grade inflammation within the central nervous system is known to accelerate the degeneration of neurons. Vitamin D exhibits anti-inflammatory and immunomodulatory properties that may help calm glial cell overactivation in the brain. Although large-scale trials investigating Vitamin D as a disease-modifying agent that halts motor decline have shown mixed results, its role in supporting overall neurological homeostasis and physical stability makes it an undisputed priority in comprehensive care regimens.
(This concludes the first part of the expert analysis on vitamins and Parkinson's disease. The subsequent part explores the targeted roles of other B-complex vitamins, the controversies surrounding antioxidant megadoses, practical diagnostic frameworks, and essential safety guidelines regarding medication interactions.)
Integrating Micronutrient Strategies into a Holistic Parkinson's Management Plan
While identifying the most promising individual vitamins—such as Vitamin D for bone mineral density and neuroprotection, Coenzyme Q10 for mitochondrial support, and the B-vitamin complex for homocysteine regulation—forms a crucial foundation, selecting and using these supplements in daily life requires a structured, clinical approach. Micronutrient supplementation should never be viewed as a standalone cure or a replacement for standard dopaminergic therapy (such as levodopa or dopamine agonists). Instead, it must be integrated seamlessly into a comprehensive, multidisciplinary management framework.
Successfully navigating vitamin therapy for Parkinson's disease (PD) involves understanding optimal dosing windows, potential drug-nutrient interactions, lifestyle synergies, and future horizons in clinical research.
1. Navigating Drug-Nutrient Interactions and Absorption Challenges
One of the most critical aspects of managing Parkinson’s disease alongside vitamin supplementation is accounting for how medications interact with nutrients in the gastrointestinal tract. Parkinson's medications, particularly Levodopa/Carbidopa, share absorption pathways in the small intestine with certain amino acids and micronutrients.
Levodopa and Dietary Protein Competition
Levodopa is a large neutral amino acid (LNAA). Because dietary proteins are broken down into amino acids that utilize the same active transport mechanisms to cross both the intestinal wall and the blood-brain barrier, high-protein meals can directly compete with Levodopa, leading to reduced drug efficacy, "off" periods, or motor fluctuations. While this is primarily a dietary protein issue, patients taking amino acid supplements, multi-vitamins containing high-dose protein constituents, or heavy nutritional shakes must time them carefully—typically taking Levodopa 30 to 60 minutes before meals or consulting a dietitian to redistribute protein intake toward the evening.
The Role of Iron and Calcium
Iron Supplementation: Iron is frequently prescribed for anemia or restless legs syndrome, both of which can overlap with Parkinson's disease. However, free ferrous iron can react with hydrogen peroxide in the brain via the Fenton reaction, generating oxidative stress and reactive oxygen species. Furthermore, iron can bind directly to Levodopa in the gut, forming an insoluble chelate that drastically reduces the medication's absorption. If iron supplementation is medically necessary, it must be separated from Levodopa doses by at least two hours.
Calcium and Bone Health: Because patients with Parkinson’s face an elevated risk of osteopenia and osteoporosis due to mobility limitations and frequent Vitamin D deficiency, calcium supplementation is common. However, excessive calcium carbonate can alter gastric pH and bind to other micronutrients. Pairing calcium intake with adequate Vitamin D3 and magnesium ensures proper deposition into bone matrix rather than soft tissue calcification.
2. Personalization: Testing, Biomarkers, and Dosage Guidelines
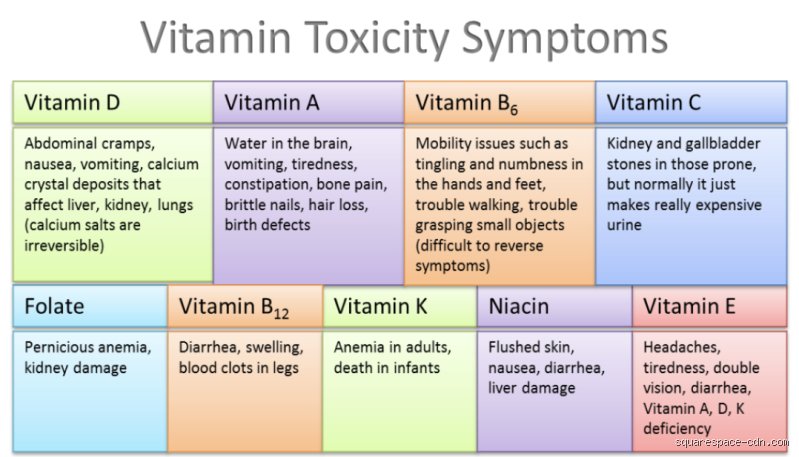
Blindly supplementing with high doses of every available vitamin can lead to adverse effects, toxicity, or wasted financial resources. A personalized, biomarker-driven strategy managed by a movement disorder specialist or a clinical nutritionist is essential.
Essential Baseline Blood Panels
Before initiating high-dose regimens, patients should undergo comprehensive nutritional screening, including:
25-Hydroxyvitamin D (): To accurately diagnose deficiency and monitor the efficacy of Vitamin D3 supplementation, aiming for optimal neuro-immune ranges (typically between 30 and 50 ng/mL).
Serum Homocysteine, Vitamin B12, and Folate: Essential for detecting subclinical B-vitamin deficiencies, elevated homocysteine (which accelerates cognitive decline and vascular risk), and methylmalonic acid (MMA) levels.
Complete Metabolic Panel and Liver Function Tests: To ensure that fat-soluble vitamins (like Vitamin D) and high-dose antioxidants do not stress hepatic pathways.
Tailored Dosing Frameworks (General Clinical Benchmarks)
Note: The following ranges represent standard clinical study parameters and general guidelines; individual dosages must always be tailored by a qualified physician.
3. Synergistic Lifestyle Interventions: Beyond the Pill Bottle
Vitamins do not operate in a vacuum. Their efficacy in slowing neurodegeneration and improving quality of life in Parkinson's disease is significantly amplified when combined with targeted lifestyle modifications.
Structured Exercise and Physical Therapy
Exercise is currently the only non-pharmacological intervention clinically proven to potentially alter the disease trajectory of Parkinson's disease through neuroplasticity and the upregulation of brain-derived neurotrophic factor (BDNF).
Aerobic Training: Enhances mitochondrial biogenesis, working synergistically with mitochondrial cofactors like Coenzyme Q10 and B-complex vitamins.
Resistance and Balance Training: Combines with optimal Vitamin D and calcium levels to fortify bone mineral density, reducing the incidence of fractures following falls.
High-Intensity Forced Exercise: Programs such as cycling cadence-matching or Rock Steady Boxing improve motor coordination and dopaminergic signaling efficiency.
Nutritional Synergy: The Mediterranean-DASH Intervention for Neurodegenerative Delay (MIND Diet)
Rather than relying on isolated vitamin supplements alone, adopting an anti-inflammatory dietary pattern provides a rich matrix of antioxidants, polyphenols, and essential minerals. The MIND diet—which emphasizes leafy greens, berries, nuts, whole grains, fish, poultry, and olive oil—naturally supplies many of the micronutrients required to combat oxidative stress and systemic inflammation inherent in Parkinson’s pathology.
4. Future Horizons in Nutritional Neuroprotection
As clinical research advances, the scientific community is moving beyond generalized vitamin supplementation toward precision neurology.
Gut-Brain Axis and Microbiome-Targeted Vitamins
Emerging data highlights the gut microbiome's role in Parkinson's disease. Pathological alpha-synuclein aggregation is hypothesized by the Braak hypothesis to often begin in the enteric nervous system before spreading to the brain via the vagus nerve. Certain gut bacteria synthesize B vitamins (such as biotin, folate, and riboflavin) and short-chain fatty acids that maintain intestinal barrier integrity. Future clinical trials are increasingly exploring targeted prebiotics, probiotics, and microbial metabolite optimization alongside traditional vitamin therapy to reduce neuroinflammation at its root.
Advanced Delivery Systems
Bioavailability remains a persistent hurdle in neuropharmacology. Many potent antioxidants and vitamins—such as curcumin, Coenzyme Q10, and certain B vitamins—suffer from poor oral bioavailability, rapid hepatic first-pass metabolism, or inability to cross the blood-brain barrier efficiently. Innovative pharmaceutical engineering, including liposomal encapsulation, nanoparticle delivery systems, and sublingual or transdermal formulations, is currently being evaluated in clinical settings to ensure therapeutic concentrations reach central nervous system tissues safely and effectively.
Conclusion
Determining the "best" vitamin for Parkinson's disease reveals a nuanced reality: there is no single magic bullet, but rather a strategic matrix of essential micronutrients tailored to an individual's biochemical profile.
Vitamin D3 stands out as vital for bone health, neuro-immune modulation, and fall prevention.
Coenzyme Q10 and high-dose Thiamine offer promising avenues for supporting failing cellular energy systems and mitigating fatigue.
B-complex vitamins (B6, B12, and folate) are indispensable for homocysteine control and protecting neurological integrity.
Ultimately, successful management requires a collaborative partnership between the patient, movement disorder specialists, and clinical dietitians. By combining biomarker testing, careful timing around dopaminergic medications, targeted supplementation, and rigorous lifestyle interventions like exercise and anti-inflammatory nutrition, individuals with Parkinson's disease can optimize their neurological health, preserve physical function, and enhance their overall quality of life.
What specific vitamin or supplement regimen is your healthcare team currently considering for your Parkinson's management plan?