Understanding the condition requires shifting our focus toward the subtle, often overlooked early indicators that can manifest years—or even decades—before a formal clinical diagnosis. Recognizing these early signs can transform patient outcomes, opening windows for early intervention, neuroprotective research, and proactive disease management.
1. The complex neurological landscape of Early-Stage Parkinson’s
To appreciate why early signs are so diverse, it is essential to understand what happens inside the central nervous system during the preclinical and prodromal phases of Parkinson's disease. Pathologically, the condition is characterized by the accumulation of misfolded proteins called alpha-synuclein, forming aggregates known as Lewy bodies inside neurons.
For a long time, medical science viewed Parkinson’s strictly as a movement disorder originating in the substantia nigra, a localized region of the midbrain responsible for producing dopamine. However, landmark staging models, such as those proposed by neurologist Heiko Braak, demonstrate that alpha-synuclein pathology often begins elsewhere. It frequently targets the enteric nervous system (the gut's nervous network) and the lower brainstem (including areas that regulate olfaction, sleep cycles, and autonomic function) long before ascending to the motor centers.
This neuropathological trajectory explains why the earliest manifestations of Parkinson’s are frequently non-motor in nature. Patients may experience digestive slowdowns, olfactory loss, or sleep disturbances years before a physician notices any rigidity or tremors.
2. Olfactory dysfunction: The loss of smell (anosmia or hyposmia)
One of the most robust yet frequently overlooked prodromal signs of Parkinson’s disease is a diminished or completely lost sense of smell, clinically known as hyposmia or anosmia. Research suggests that olfactory dysfunction affects up to 90% of individuals with Parkinson's disease and can precede motor symptoms by anywhere from two to ten years.
Why smell fails early
The olfactory bulb and the anterior olfactory nucleus are among the very first brain structures impacted by Lewy body pathology. Because these areas have direct exposure to the external environment and dense interconnections with limbic structures, they appear uniquely vulnerable to early protein aggregation.
Clinical Implications
A declining sense of smell is easy to dismiss as a normal consequence of aging, chronic sinus issues, or a history of past viral infections. However, when an individual experiences a progressive, unexplained reduction in their ability to detect subtle scents, such as coffee, cinnamon, vanilla, or gas leaks, without any localized nasal blockage, it warrants medical attention. Interestingly, while olfactory loss is a high-risk marker for developing Parkinson's, not everyone with hyposmia will develop the disease, making it a critical piece of a larger clinical puzzle rather than a standalone diagnostic tool.
3. REM Sleep Behavior Disorder (RBD): Acting out dreams
Sleep architecture is profoundly disrupted in the early phases of neurodegeneration. While common insomnia or general sleep fragmentation can stem from stress, lifestyle, or aging, a specific parasomnia called Rapid Eye Movement (REM) Sleep Behavior Disorder (RBD) shares a deeply established link with alpha-synucleinopathies.
Understanding normal vs. Disrupted REM Sleep
During normal REM sleep, the brain actively inhibits the body's major skeletal muscles, inducing a state of temporary paralysis (atonia) that prevents us from physically acting out our dreams. In patients with RBD, this physiological protective mechanism fails.
Consequently, individuals physically enact vivid, often unpleasant, or action-packed dreams. This behavior can manifest as:
Sudden limb jerking, flailing, or punching during sleep
Kicking or thrashing violently
Shouting, talking, screaming, or emotional outbursts in bed
Accidental self-injury or injury to a bedpartner
The Predictive Value
Long-term longitudinal studies tracking patients with idiopathic RBD have revealed that a staggering percentage, sometimes estimated at over 50% to 75% over a decade or more, eventually go on to develop Parkinson’s disease, dementia with Lewy bodies, or multiple system atrophy. Identifying RBD early provides a unique window for researchers to study neuroprotection before motor disability begins.
4. Autonomic dysfunction: Constipation and Gastrointestinal slowdown
The connection between the gut and the brain, often referred to as the gut-brain axis, plays a starring role in the early chapters of Parkinson's disease. Long before dopamine depletion causes muscular rigidity, the digestive tract frequently exhibits signs of dysfunction.
Chronic Constipation
Chronic, unexplained constipation that resists standard dietary adjustments, hydration, and over-the-counter interventions is one of the earliest non-motor symptoms of Parkinson's. It can manifest upwards of 10 to 20 years before a motor diagnosis. This occurs because alpha-synuclein pathology accumulates in the enteric nervous system, disrupting the complex neural circuits that coordinate regular bowel motility.
Other early autonomic signs
Beyond the gastrointestinal tract, early autonomic nervous system involvement can present as:
Orthostatic hypotension: A sudden drop in blood pressure upon standing up, causing lightheadedness or dizziness.
Urinary urgency or frequency: Unexplained bladder overactivity not entirely attributable to urological pathology.
Seborrheic dermatitis: Excessive skin oiliness or persistent flaking, particularly around the scalp and face.
5. Mood alterations: Depression, anxiety, and apathy
Neurological changes in the brain's chemical signaling networks do not occur in isolation. Alongside dopamine pathways, circuits governing mood, reward, and emotional regulation, such as norepinephrine and serotonin pathways, are frequently disrupted early in the disease process.
Disentangling reaction from pathology
It is entirely natural for an individual to feel anxious or depressed upon receiving a major medical diagnosis, but in Parkinson's, mood disturbances often appear as prodromal symptoms. This means depression, generalized anxiety, or profound apathy (a severe lack of motivation or emotional expression) can emerge years before any physical motor signs appear.
Apathy, in particular, is frequently misdiagnosed as clinical depression or simple laziness. However, true neurogenic apathy stems from a disruption in the frontal-subcortical circuits, leaving patients feeling indifferent toward hobbies, social interactions, or daily goals, even when they report not feeling explicitly sad or blue.
The progression and complex interplay of early symptoms
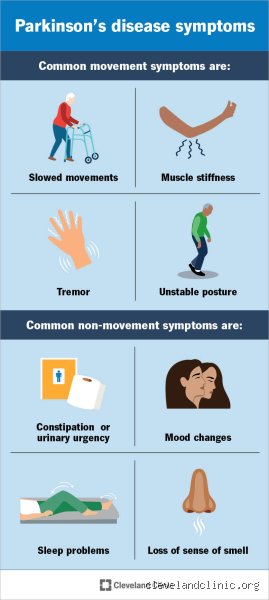
While individual signs like a reduced sense of smell or a minor resting tremor often appear in isolation, the clinical picture of early Parkinson’s disease typically involves a constellation of overlapping changes. Because these symptoms manifest gradually, often over months or years, they are frequently dismissed as normal aspects of aging or attributed to unrelated physical strains. However, understanding how non-motor and motor indicators interact provides crucial context for early identification.
To better grasp how these manifestations cluster and evolve, consider the following breakdown of interconnected bodily changes:
Autonomic and Gastrointestinal Shifts: Chronic constipation and subtle drops in blood pressure upon standing (orthostatic hypotension) stem from early disruptions in the autonomic nervous system. These signs often predate motor symptoms by over a decade, signaling that internal regulatory systems are affected long before voluntary movement appears.
Sensory and Sleep Disturbances: The loss of smell (anosmia or hyposmia) and REM Sleep Behavior Disorder (RBD), where individuals physically act out vivid dreams, frequently point toward early brainstem involvement.
Asymmetric Motor Indicators: When physical signs do emerge, they are usually asymmetric, meaning they affect only one side of the body initially. A slight decrease in arm swing on one side, a faint resting tremor in a single thumb or finger, or early stiffness in one shoulder are classic hallmarks of this phase.
Navigating the diagnostic process
Recognizing these early signs is only the first step; obtaining an accurate clinical evaluation is essential. Because no single laboratory or blood test can definitively diagnose Parkinson's disease on its own, neurologists rely on a comprehensive physical and neurological examination.
During an evaluation, a specialist will closely assess:
Medical History and Symptom Timeline: Documenting when non-motor changes (such as sleep disruptions or digestive shifts) and motor signs (such as bradykinesia or rigidity) first manifested.
Physical Responsiveness: Observing gait, posture, and coordination, and occasionally utilizing specialized brain imaging scans (such as a DaTscan) to evaluate dopamine transporter levels.
Medication Response: Evaluating how well symptoms respond to specific dopaminergic medications, which can serve as a supportive diagnostic indicator.
Proactive management and next steps
An early awareness of Parkinson’s markers opens the door to proactive lifestyle adjustments and therapeutic interventions that can significantly enhance long-term quality of life. While a diagnosis can feel daunting, modern medical therapies, specialized physical exercise regimens, and targeted nutritional strategies offer powerful ways to maintain mobility and independence.
If you or someone you know is navigating unexplained, persistent changes like those outlined above, consulting a primary care physician for a referral to a movement disorder specialist is the most effective path forward.