Decoding the anatomy of chronic Post-Viral exhaustion
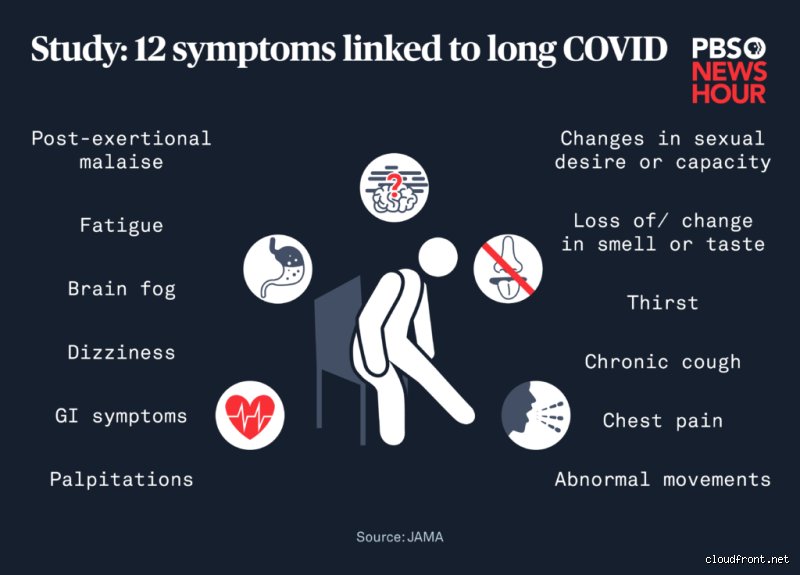
Differentiating ordinary lifestyle burnout from clinical exhaustion involves examining the specific qualities of the fatigue itself. When someone pushes through a demanding work week or experiences a period of intense stress, standard tiredness sets in, responding predictably to downtime. By contrast, the exhaustion associated with post-acute infection syndromes features a stark reduction in baseline vitality that does not improve with rest. Individuals often describe feeling as though their internal battery has permanently capped at a fraction of its former capacity, transforming routine daily tasks like showering, preparing a meal, or walking down the hallway into major physiological hurdles.
The role of baseline energy depletion
The primary marker of this condition is a severe drop in functional capacity that persists for months following the initial infection. People note that tasks they once completed effortlessly now require careful rationing of energy throughout the day. This constraint forces individuals to make difficult choices about which activities to prioritize, as engaging in one social or professional task might completely exhaust their available physical reserves for the remainder of the day.
Cognitive impacts and mental fatigue
Alongside physical heaviness, mental exhaustion—frequently referred to as brain fog—plays a major role in how the condition presents. Processing complex information, maintaining focus during a conversation, or recalling words can become unexpectedly difficult. This mental weariness is distinct from ordinary distraction; it feels like operating behind a heavy cognitive veil, where logical reasoning and memory retrieval require vastly more mental energy than they did prior to infection.
Unpacking the mechanism of Post-Exertional malaise
A defining element that sets long-term post-viral fatigue apart from ordinary tiredness is a phenomenon known as post-exertional malaise, or PEM. This reaction occurs when physical, mental, or even emotional exertion triggers a delayed, disproportionate worsening of symptoms. Rather than experiencing a normal level of muscle soreness or mild tiredness after activity, an individual dealing with PEM may face a severe physical and cognitive crash hours or even days later.
The delayed crash cycle
The temporal aspect of PEM can make recognition challenging because the worsening of symptoms does not always happen immediately during the activity. A person might feel fine while completing a light task, only to experience a sudden surge of flu-like achiness, severe weakness, and cognitive clouding twenty-four to forty-eight hours later. This delay creates a confusing cycle where cause and effect are difficult to link without careful tracking, as everyday movements inadvertently cross the invisible threshold of what the body can currently handle.
Triggers beyond physical exercise
While physical exertion like walking or lifting is a common trigger, cognitive and emotional stressors can provoke the exact same crash. Lengthy phone calls, managing household finances, navigating a crowded environment, or dealing with an emotionally charged situation can all demand enough energy to induce a severe post-exertional setback. Recognizing these non-physical triggers is essential for understanding why routine daily life remains disrupted even for individuals who limit physical movement.
Exploring overlapping syndromes and autonomic signs
Beyond fatigue and post-exertional crashes, long COVID exhaustion frequently intersects with other physiological disturbances, adding another layer of complexity to identification. Many individuals report accompanying autonomic symptoms, such as rapid heart rate changes, dizziness upon standing, or temperature dysregulation. These overlapping patterns share striking similarities with conditions like myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) and postural orthostatic tachycardia syndrome (POTS), suggesting that persistent post-viral fatigue involves systemic regulatory issues rather than simple psychological stress or physical deconditioning.
Evaluating persistent exhaustion requires looking beyond standard sleep deprivation or everyday burnout, focusing instead on how the body handles physical, cognitive, and emotional demands over extended periods. Clinical presentations frequently highlight a profound mismatch between energy expended and recovery achieved, pointing toward systemic disruptions that persist long after the initial viral clearance. Recognizing these patterns involves mapping out specific physiological triggers and monitoring how daily tasks alter overall functional capacity.
Decoding Post-Exertional malaise and energy limits
A defining feature of long-term post-viral fatigue is post-exertional malaise, often abbreviated as PEM. This phenomenon occurs when routine physical or mental exertion results in a disproportionate, delayed worsening of symptoms. Unlike standard tiredness that resolves with a good night of rest, post-exertional malaise can trigger a multi-day crash characterized by deep physical weakness, cognitive dysfunction, and widespread muscle aches. Activities as simple as grocery shopping, answering work emails, or taking a short shower can provoke this severe reaction. The onset is frequently delayed by twelve to forty-eight hours, making it difficult for individuals to immediately connect their current collapse to the specific activity that triggered it.
Evaluating this vulnerability requires examining the concept of an energy envelope. Every person operates within a finite daily reserve, but post-viral conditions drastically shrink that boundary. Crossing this threshold does not lead to healthy fatigue that adapts and builds resilience through exercise. Instead, overexertion damages cellular energy production pathways and worsens baseline health status. Clinicians emphasize tracking symptom flares relative to exertion levels to differentiate this condition from ordinary exhaustion or unconditioned deconditioning.
Distinguishing viral exhaustion from standard exhaustion
Standard fatigue typically stems from acute stressors like poor sleep hygiene, heavy workloads, or temporary lifestyle imbalances, and it reliably improves with restorative downtime. In contrast, post-COVID fatigue operates independently of sleep quality. Individuals can sleep for ten hours and wake up feeling as though they have run a marathon or worked a multi-day shift without rest. This unrefreshing sleep cycle remains a cornerstone of clinical evaluation.
Cognitive burdens frequently accompany physical exhaustion. Patients describe a persistent mental friction often termed brain fog, characterized by word-finding difficulties, short-term memory lapses, and an inability to sustain concentration during complex tasks. When physical exhaustion and cognitive slowing occur concurrently and persist for months following a confirmed or suspected viral infection, the clinical picture shifts away from ordinary burnout toward a distinct post-viral syndrome.
Navigating clinical assessment and diagnostic challenges
Because no single laboratory test can definitively diagnose post-viral fatigue syndromes, medical evaluation relies heavily on thorough symptom mapping and the exclusion of other treatable pathologies. Healthcare providers typically order comprehensive blood panels to check for thyroid dysfunction, iron deficiency anemia, autoimmune markers, and systemic inflammation. These diagnostics ensure that symptoms are not being driven by secondary complications or concurrent conditions that mimic chronic fatigue.
Documenting symptom patterns over time provides the most reliable framework for identification. Keeping a detailed daily log tracking activities, cognitive loads, sleep quality, and subsequent symptom intensity helps uncover hidden triggers. Healthcare professionals use these logs to assess functional impairment and guide management strategies. Rather than prescribing aggressive physical training regimens, clinical guidelines increasingly point toward energy conservation techniques, structured resting intervals, and careful pacing to prevent severe symptom relapses.
Charting a path through chronic uncertainty
dealing with post-viral exhaustion demands a fundamental shift in how individuals measure productivity and physical output. Listening closely to biological feedback rather than pushing through physical warnings prevents prolonged systemic crashes and preserves remaining functional capacity. Comprehensive clinical support coupled with rigorous daily pacing strategies offers the most reliable framework for stabilizing health when recovery timelines remain uncertain.