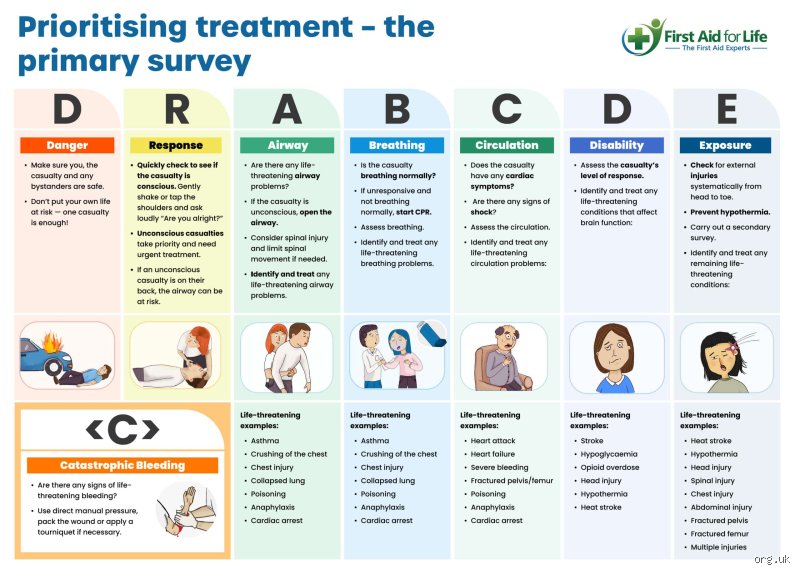
Let us be real here for a second. The textbook clinical world loves neat, linear progressions, but actual trauma bays and chaotic roadsides in places like Baltimore or rural Texas are anything but orderly. The primary assessment is not a gentle stroll through a diagnostic checklist. Instead, it is a violent, necessary interruption of the dying process. I have seen seasoned medics freeze because they looked at a broken leg instead of an occluded trachea. You have to look past the dramatic, bloody distractions. The core philosophy hinges on a simple truth: if you do not fix the hypoxia or the catastrophic hemorrhage right now, the patient will not live long enough for the orthopedic surgeon to matter anyway.
Understanding the true blueprint and evolution of Emergency stabilization
Historically, the concept of a structured initial evaluation emerged from military medicine and the early iterations of the Advanced Trauma Life Support framework established in 1978. Before this standardized approach, emergency medicine was a bit of a Wild West where physicians treated whatever looked the worst. That matters most when you realize that the most lethal killers are often invisible from across the room. The primary assessment forces a provider to treat the most immediate threat to life based on predictable physiological timelines. If oxygen fails to reach the brain, cellular death begins within four to six minutes, making the evaluation of oxygen pathways the undisputed starting line.
The dynamic shift from linear ABC to the aggressive MARCH protocol
The complication is that the traditional order is no longer sacred. In recent years, tactical combat casualty care data from conflicts in Iraq and Afghanistan flipped the script, proving that massive, exsanguinating arterial bleeding kills faster than a partial airway obstruction. This realization gave birth to the MARCH protocol, placing massive hemorrhage at the very front of the line. Because why bother clearing an airway if the patient’s entire blood volume is pooling on the tarmac? A standard adult can bleed to death from a severed femoral artery in about three minutes. The traditional ABC sequence still dominates medical wards, yet high-threat trauma environments demand this hyper-aggressive modification because exsanguination remains the leading cause of preventable death on the battlefield.
The technical anatomy of the airway and breathing evaluation
When answering what should be assessed during the primary assessment, the physical patency of the upper respiratory tract is your first geometric checkpoint. You are looking for actual mechanical blockages, which means opening the mouth, sweeping for foreign objects, and listening for telltale sounds like stridor or gurgling. A snoring sound typically indicates the tongue has dropped backward against the posterior pharyngeal wall due to loss of consciousness. But what if there is a suspected cervical spine injury? That is where the standard head-tilt, chin-lift becomes a dangerous liability, forcing providers to master the jaw-thrust maneuver to maintain spinal alignment while opening the airway.
Advanced patency verification and mechanical interventions
Establishing patency is only half the battle; you must secure it. If the patient lacks a gag reflex, an oropharyngeal airway is indicated, whereas a conscious patient requires a nasopharyngeal tube to avoid inducing vomiting. In 2022, a multicenter study published in the Annals of Emergency Medicine highlighted that first-pass success rates for endotracheal intubation drop by 22 percent when facial trauma is present. This is precisely where clinical judgment becomes strained. Experts disagree on exactly when to abandon non-invasive metrics and move to a surgical cricothyroidotomy, demonstrating that managing a compromised airway is more of an unpredictable art than a rigid science.
Quantifying ventilation and recognizing pulmonary catastrophes
Once you prove the pipe is open, you must assess if air is actually moving. This requires observing chest rise and fall, checking the respiratory rate, and checking for bilateral breath sounds. You are hunting for specific killers like a tension pneumothorax, which shifts the mediastinum and collapses thoracic venous return. If you notice asymmetrical chest expansion or tracheal deviation—though it's unclear why textbooks still push tracheal deviation since it is a late, rare sign, you need to act. A needle decompression in the second intercostal space at the midclavicular line must happen immediately, bypassing the wait for a chest X-ray.
Circulatory dynamics and perfusion metrics
Circulation is not just about counting a pulse rate; it is a holistic evaluation of end-organ perfusion. You need to assess the quality, regularity, and location of palpable pulses immediately. A missing radial pulse with a palpable carotid pulse typically signals a systolic blood pressure below 80 mmHg. Skin condition provides an immediate window into the sympathetic nervous system. Pale, cool, clammy skin tells you the body is actively shunting blood away from the periphery to protect the heart and brain, a classic sign of hypovolemic shock.
The critical nuances of capillary refill and intravascular volume
Evaluating capillary refill time by compressing the nail bed for five seconds remains a staple, but it is notoriously unreliable in cold environments or ambient lighting. We are far from a perfect metric here. The trouble is that subtle shifts in circulatory status can mask massive internal blood loss, especially in young, healthy athletes whose compensatory mechanisms keep blood pressure stable until they suddenly crash. Therefore, checking for pelvic stability and scanning the abdomen for distension are vital components of this phase, as the pelvis can easily hide two liters of concealed blood after blunt force trauma.
Divergent methodologies: Medical versus Trauma contexts
The execution of what should be assessed during the primary assessment changes dramatically based on whether your patient is a trauma victim or a medical code. In a pure medical scenario, such as an acute myocardial infarction or an ischemic stroke, the timeline stretches slightly, allowing for a more analytical approach. The focus shifts away from physical deformities toward subtle neurological deficits and metabolic presentations. Yet, the core mandate of preventing cellular hypoxia remains identical.
Contrasting the ABCDE framework against the unified cardiac arrest algorithm
Consider the stark contrast between a multi-vehicle accident and a sudden cardiac arrest in a suburban shopping mall. In the trauma scenario, you meticulously work through ABCDE to catch occult bleeding and thoracic injuries. But when a patient collapses from ventricular fibrillation, the American Heart Association dictates a complete reversal to the CAB sequence. High-quality chest compressions take precedence over everything else to keep the coronary arteries perfused. This dualist methodology proves that the primary assessment is not a monolithic religious text, but a fluid tactical strategy that adapts to the mechanism of injury.
Common pitfalls and fatal flashes of misunderstanding
The tunnel vision trap
You arrive at a chaotic scene and a mangled limb immediately commands your gaze. Human nature forces your eyes toward the blood. Yet, fixating on a dramatic compound fracture while ignoring a silent, collapsing airway is a classic rookie blunder. Experienced clinicians know that catastrophic external hemorrhage must be plugged instantly, but ordinary fractures can wait. The problem is that gory injuries trigger an adrenaline surge that narrows your cognitive field.
Because of this psychological trap, providers frequently scramble the established sequence. They check a pulse before ensuring chest wall expansion. If you deviate from the rigid algorithm, you will miss occult trauma. A patient can look perfectly conscious right before their respiratory drive completely disintegrates.
Misinterpreting the "normal" vital sign
A normal heart rate means the patient is fine, right? But young, athletic individuals can lose up to 35% of their circulating blood volume before their blood pressure plummets. Their robust compensatory mechanisms mask internal bleeding beautifully. Then, they crash off a cliff. Another misconception involves counting respirations. Clinicians often glance at a chest and write down a fictional, standard number like sixteen breaths per minute. They completely ignore the shallow depth or the accessory muscle use. If you fail to genuinely look, listen, and feel, your baseline documentation becomes dangerous fiction.The myth of the One-And-Done check
What should be assessed during the primary assessment is never a static, single-point evaluation. This is a dynamic loop. You do not just check the box and move on to secondary head-to-toe reviews permanently.
If you roll a patient onto a backboard, you have altered their spinal alignment and respiratory mechanics. Guess what? You must re-evaluate everything from the top. Believing that a stable airway at minute two guarantees a stable airway at minute ten is pure fantasy.
The chronological blindspot: Dynamic Micro-Shifts
Chronemic re-evaluation and environmental interferences
The ticking clock modifies your findings. Experienced providers understand that what should be assessed during the primary assessment fluctuates based on ambient temperature and transport times. Hypothermia silently derails the coagulation cascade. A trauma patient exposed to cold asphalt for merely nine minutes can develop severe coagulopathy, which increases mortality by nearly 40%. Therefore, assessing the environment and exposing the patient must be balanced with aggressive re-warming tactics. The trouble is that the initial physical exam is just a blurry snapshot. You must transform it into a continuous movie.The silent autonomic shift
Do not trust an elderly patient’s baseline response. Polypharmacy ruins your classic shock indicators. A patient taking beta-blockers will not show tachycardia, even if they are bleeding out into their peritoneum.
This is why you have to look for subtle signs like pale conjunctiva or delayed capillary refill in the fingers instead of relying on the cardiac monitor. Have we become too reliant on digital screens? Absolutely. Your eyes and hands are far more reliable than a pulse oximeter flickering under bright ambulance lights.
Frequently asked questions
Does the primary exam sequence change for pediatric patients?
Yes, the fundamental priorities remain identical, but your physiological thresholds shift dramatically when managing infants. A pediatric heart rate below 60 beats per minute accompanied by poor perfusion requires immediate cardiopulmonary resuscitation, unlike an adult counterpart who might simply be bradycardic. Their respiratory rates are naturally higher, meaning an infant breathing at 45 breaths per minute is perfectly normal, whereas that same rate indicates imminent respiratory failure in an adult. Children possess highly compliant chest walls that easily mask massive internal thoracic trauma without presenting rib fractures. As a result, you must rely heavily on the pediatric assessment triangle, evaluating appearance, work of breathing, and circulation to the skin from across the room before you even touch the patient.How long should a clinician spend on the initial assessment phase?
The entire primary survey should ideally be completed in fewer than 60 seconds, assuming no immediate life threats are discovered. If you encounter an obstructed airway or a tension pneumothorax, you must halt the sequence and intervene immediately before moving to the next letter of the algorithm. The gold standard for trauma systems dictates that the total on-scene time for critical patients should not exceed 10 minutes, famously known as the golden half-hour baseline. Spending too much time looking for minor details during this phase directly correlates with increased morbidity. In short, you are hunting for immediate killers, not cataloging every bruise and abrasion.What should be assessed during the primary assessment when dealing with chemical or hazardous materials?
When hazardous substances are suspected, your absolute first priority shifts completely to personal safety and patient decontamination before the standard physical survey begins. Performing a jaw-thrust or checking a carotid pulse while covered in organophosphates will simply create two casualties instead of one. Once decontamination is verified, you must pay hyper-specific attention to the airway and pupillary responses, as many chemical agents induce massive bronchoconstriction or miosis. Data from industrial emergency protocols show that 82% of secondary contamination events occur because teams rushed the primary evaluation without neutralizing external chemical threats first.A final reckoning on initial lifesaving priorities
We must stop treating medical protocols like mindless bureaucratic checklists. The primary assessment is a high-stakes, fluid triage art form that demands your full cognitive presence. If you treat it as a passive chore, patients die on your watch. Our collective clinical hubris often leads us to believe we can spot systemic failure at a glance, (an assumption that has been proven wrong in emergency rooms worldwide). Commit to the sequence with religious discipline. Force yourself to look past the obvious, bloody distractions. Protect the airway, secure the breathing, stabilize the perfusion, and never stop re-evaluating the human being lying broken in front of you.