The Core confusion: Why PDA gets mistaken for Social phobia
Untangling the overlap between autistic profiles and phobic Avoidance
At first glance, an individual with a PDA profile can look remarkably similar to someone experiencing severe social anxiety or avoidant personality traits. Both groups may withdraw from group settings, struggle with standard interpersonal workflows, and display high baseline nervousness. Because traditional clinical frameworks historically over-relied on external behaviors rather than internal motivations, many neurodivergent individuals experiencing demand-based panic have been incorrectly funneled into social phobia diagnoses.
The Little-Known aspect: Social strategies as a defense Mechanism
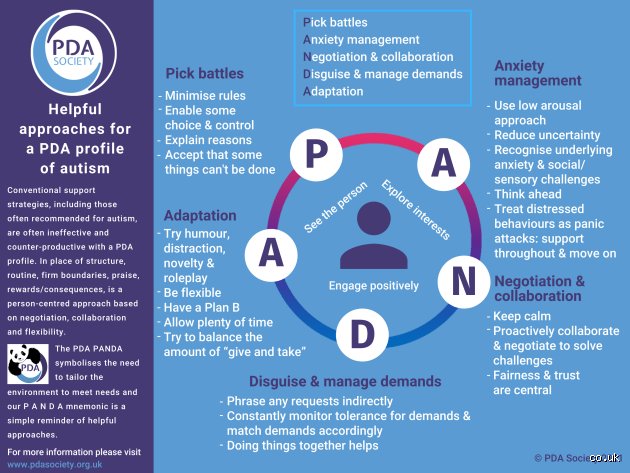
A fascinating and frequently overlooked nuance of the PDA profile is its distinct social style. Unlike classic social anxiety, which typically drives a person to shrink away, hide, or avoid interpersonal contact altogether, individuals with PDA often use complex social strategies, such as joking, role-play, distracting, or negotiating, to deflect demands. They can appear outwardly charming, highly verbal, and socially adept while experiencing catastrophic internal panic. This creates a clinical illusion that they are socially confident, masking the reality that their entire nervous system is treating an everyday request as an existential threat.
How it works: The nervous system under siege
The threat response vs. The Fear of evaluation
To understand why PDA is fundamentally distinct from social anxiety, one must look closely at what triggers the body’s fight-or-flight response. Social anxiety is fundamentally social-evaluative; it flares up because the individual worries about being humiliated, scrutinized, or found lacking by peers. PDA, by contrast, is demand-evaluative. The trigger does not have to involve other people at all. An internal desire, such as wanting to eat, sleep, or complete a hobby, can trigger the exact same threat response if it is perceived as an obligation, a loss of autonomy, or an external expectation.
The role of executive dysfunction and Autonomy drives
The Illusion of Defiance: When faced with a demand, a person with PDA does not choose to be oppositional; rather, their brain hits an involuntary emergency brake.
The Need for Equality: PDAers often struggle fundamentally with hierarchical structures. Traditional social anxiety bends toward appeasing authority to avoid judgment, whereas a PDA profile revolts against authority because perceived imbalance threatens psychological safety.
Intolerance of Uncertainty: Both profiles feature high baseline anxiety, but in PDA, that anxiety specifically zeroes in on the loss of personal agency and control over one's immediate environment.
Why standard Exposure Therapy fails PDAers
When clinicians treat social anxiety, they typically rely on cognitive behavioral therapy (CBT) and gradual exposure to feared social scenarios. However, applying direct exposure techniques to a PDA profile often backfires disastrously. Because every forced compliance step acts as a fresh demand, exposure therapy reinforces the nervous system's belief that the environment is hostile and controlling.
Key differences in presentation and daily impact
Triggers and Boundaries
The operational boundaries of both conditions dictate entirely different daily challenges.
| Feature | Social Anxiety Disorder | PDA (Autism Spectrum Profile) |
|---|---|---|
| Core Fear | Negative evaluation, embarrassment, or judgment. | Loss of autonomy, control, and freedom. |
| Social Interaction | Often causes distress due to scrutiny; benefits from predictability. | Can be used as a tool or diversion strategy to deflect demands. |
| Solitary Demands | Usually well-tolerated if self-directed. | Can still trigger severe avoidance if perceived as a "must-do" task. |
Internal monologues and emotional processing
The internal dialogue of someone experiencing social anxiety is centered on self-criticism ("Everyone is looking at me; I sound foolish"). Conversely, the internal monologue of a person experiencing a PDA meltdown revolves around self-preservation and trapped panic ("I can't breathe, I'm being cornered, I have to escape this control").
Comparing options and alternatives for support
Navigating misdiagnosis risks
Because diagnostic overlap is common, distinguishing between social anxiety, generalized anxiety, and a PDA profile is critical for long-term well-being. Misdiagnosing PDA as purely social anxiety leads to behavior modification programs that increase shame, trauma, and chronic nervous system burnout.
Moving toward Low-Demand frameworks
Collaborative Problem Solving: Shifting away from direct commands toward declarative language (e.g., "It's getting dark outside" instead of "Turn on the lights").
Autonomy-Affirming Environments: Creating spaces where individuals retain maximum choice over how, when, and if tasks are accomplished
Deconstructing the overlap: Why PDA is mistaken for Social Anxiety
While social anxiety disorder (SAD) is fundamentally anchored in a fear of negative evaluation, humiliation, or social scrutiny by others, the Pervasive Drive for Autonomy or Pathological Demand Avoidance (PDA) profile, frequently understood as a neurodivergent presentation within the autism spectrum, orbits around an entirely different axis: the preservation of equality and safety through control.
Yet, clinicians, educators, and parents frequently mistake one for the other because the outward presentation can look remarkably similar. Both conditions commonly manifest as social withdrawal, school refusal, elective mutism, and a visible spike in distress when a person is thrust into unstructured group dynamics.
To untangle these two distinct psychological profiles, we must look past surface-level avoidance and examine the internal neurobiology driving the behavior.
Core differentiating factors: Fear of judgment vs. Threat to Autonomy
| Feature | Social Anxiety Disorder (SAD) | PDA (Autism Spectrum Profile) |
|---|---|---|
| Primary Driver | Fear of negative evaluation, embarrassment, or being judged unfavorably. | Threat to autonomy, loss of equality, and nervous system panic triggered by direct demands. |
| Social Functioning | Often features high surface compliance coupled with internal dread; desires connection but fears rejection. | Often features surface sociability, role-play, or masking, but collapses when faced with expectations or hierarchies. |
| Response to Structure | Structured rules and predictability often reduce anxiety by clarifying social expectations. | Direct, routine demands or arbitrary rules escalate anxiety because they feel like an oppressive loss of control. |
| Underlying Mechanism | Hyperactivity in threat-detection circuits (like the amygdala) specifically linked to social evaluation cues. | Generalized autonomic nervous system arousal (fight/flight/freeze/fawn) triggered by everyday expectations. |
The Social dimensions of PDA
A common misconception is that individuals with a PDA profile lack social interest. In reality, people with PDA often possess sophisticated social awareness and can appear superficially charming, chatty, or confident. They use social navigation, such as humor, role-play, distraction, and elaborate negotiation, as protective strategies to deflect demands.
However, their relationships are frequently complicated by an intense, underlying need for equality and control. Traditional social hierarchies, such as teacher-student, boss-employee, or even peer dynamics where one person dictates the activity, are interpreted by a PDA nervous system as an imminent threat.
When a person with social anxiety avoids a party, it is usually because they are terrified that people are looking at them, judging their outfit, or evaluating their conversation skills. When an individual with a PDA profile avoids a social invitation or group gathering, it is frequently because the event feels packed with hidden expectations, unwritten rules, and demands on their time and energy that strip away their sense of agency.
Clinical implications: Why misdiagnosis matters
Mistaking a PDA profile for standard social anxiety can lead to well-intentioned but harmful intervention strategies. Standard treatments for social anxiety rely heavily on Cognitive Behavioral Therapy (CBT), exposure therapy, and behavioral reinforcement.
The Pitfall of Exposure and Compliance: For someone with a PDA profile, standard behavioral token economies, reward charts, and direct exposure hierarchies are often experienced as coercive demands. Rather than reducing anxiety, pushing compliance-based treatment models typically triggers a severe nervous system escalation, reinforcing the cycle of burnout, meltdowns, or school avoidance.
The Low-Demand Paradigm: Effective support for a PDA profile shifts away from behavioral compliance and toward a low-demand, collaborative framework. This involves reframing language (using declarative, non-directive phrasing), prioritizing emotional connection over behavioral control, and protecting the individual's autonomy.
Moving forward: Holistic understanding
While an individual can certainly experience both social anxiety and a PDA profile simultaneously, PDA itself is not simply a severe variant of social anxiety. It is a distinct neurodivergent profile rooted in an intolerance of everyday demands and a profound need for systemic safety. Recognizing these differences allows caregivers, educators, and clinicians to move away from punitive or ineffective compliance models and toward neuroaffirming environments where true emotional regulation can take root.
How do these distinctions align with what you have observed in educational or clinical settings regarding demand avoidance and anxiety?