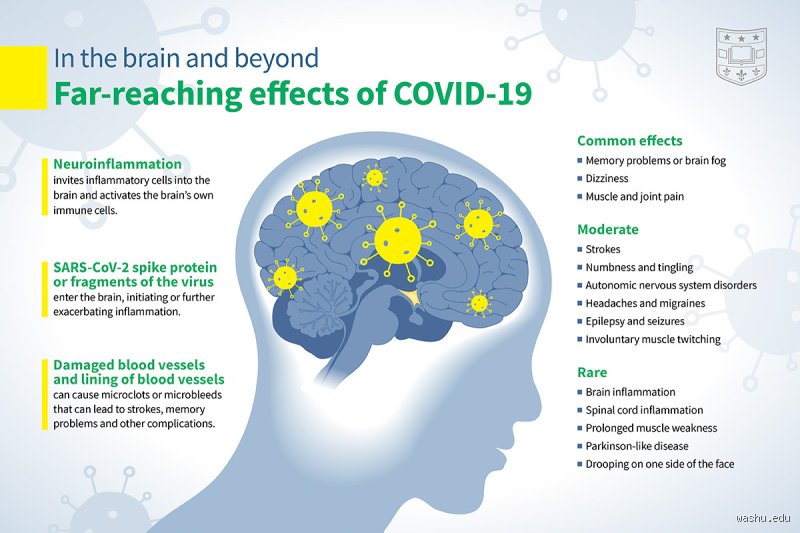
These subjective complaints have driven an unprecedented wave of neurological research. Advanced neuroimaging, longitudinal cohort tracking, and cellular-level autopsies have confirmed what patients have argued for years: COVID-19 can induce measurable structural and functional alterations in the brain. Naturally, this realization sparks an urgent, anxious question for those affected and their families: Is COVID-related brain damage permanent, or is it reversible?
To answer this complex question, neurologists, neuroscientists, and physiatrists are moving past simple alarmism and looking closely at the mechanisms of viral neuropathology, chronic neuroinflammation, and the brain’s intrinsic capacity for repair. The reality of neurological recovery after COVID-19 is not a simple binary of permanent damage versus complete cure; rather, it is a nuanced landscape governed by neuroplasticity, ongoing immune modulation, and targeted rehabilitation.
The nature of the injury: How SARS-CoV-2 affects the Brain
Before evaluating whether the brain can heal, we must first understand how it is injured. Early hypotheses often debated whether the virus directly invaded brain tissue (neurotropism) or whether neurological symptoms were secondary consequences of systemic illness, hypoxia (low oxygen), and severe systemic inflammation. Current consensus points to a multifactorial origin.
While direct viral replication within neurons appears relatively rare or restricted compared to other neurotropic viruses, SARS-CoV-2 triggers a profound systemic inflammatory response. Circulating cytokines—inflammatory signaling molecules, can compromise the blood-brain barrier (BBB), making it "leaky." Once this protective barrier is breached, inflammatory agents flood into the central nervous system. This activates the brain's resident immune cells, the microglia.
Under normal circumstances, microglia protect neural tissue. However, during chronic post-acute infection or long COVID, these cells can enter a state of hyperactivation, creating a persistent, low-grade neuroinflammatory state. Research comparing post-COVID brain changes to other respiratory infections, like influenza, reveals that COVID-19 leaves a uniquely persistent inflammatory and microvascular footprint. This involves microscopic blood vessel damage, disruptions in neurotransmitter signaling pathways (such as dopaminergic and serotonergic networks), and accelerated structural alterations in regions like the olfactory cortex, hippocampus, and basal ganglia.
Longitudinal imaging studies utilizing large cohorts, such as the UK Biobank project, have demonstrated that even mild COVID-19 cases can result in longitudinal reductions in gray matter thickness and markers of tissue damage in brain regions connected to smell and memory. These structural shifts occur at a pace significantly faster than normal, healthy aging, fueling initial fears of permanent neurodegeneration.
Shifting paradigms: From static damage to dynamic trajectories
The label "brain damage" carries a frightening connotation, implying a permanent scar or dead tissue akin to the aftermath of a severe stroke or traumatic brain injury. However, neurologists emphasize that many of the structural and functional changes observed post-COVID are not classic fixed necrotic lesions.
Instead, much of the pathology reflects metabolic suppression, microvascular dysfunction (neurovascular coupling abnormalities), synaptic stripping, and persistent functional dysregulation. Because these processes are dynamic rather than static, they theoretically carry the potential for reversal or substantial mitigation.
Recent longitudinal data tracking patients over extended periods, spanning up to three years post-infection, provide encouraging insights. While a subset of patients exhibits persistent structural alterations, such as subtle ventricular enlargement or volume shifts in subcortical structures like the thalamus and putamen, extended follow-ups show that these trajectories often stabilize. Crucially, longitudinal markers of active neurodestruction typically return to normal reference ranges, indicating that the acute neurodestructive phase burns out rather than continuously compounding.
Clinical recovery often outpaces structural normalization. Many patients experience a gradual amelioration of cognitive fog and fatigue over multi-year timelines, demonstrating that the human brain possesses remarkable compensatory mechanisms. Over 80% of individuals in long-term cohorts eventually perform within normal ranges across standard neuropsychological testing domains, even if subjective fatigue or intermittent cognitive stamina remains a challenge.
The role of neuroplasticity and natural healing
The cornerstone of hope in reversing neurological symptoms lies in neuroplasticity, the brain’s lifelong ability to reorganize itself by forming new neural connections, rerouting signals around damaged areas, and adapting to functional deficits.
When a viral infection disrupts the delicate networks governing attention, processing speed, and executive function, the brain does not simply sit passively. Just as skeletal muscle adapts to stress through repair and strengthening, neural circuits can be stimulated to forge alternative pathways. Functional MRI (fMRI) studies of recovering long COVID patients reveal distinct patterns of brain adaptation. For instance, patients often show increased neuronal activation or recruitment in compensatory regions, such as the basal ganglia and prefrontal networks, to achieve the same cognitive output as they did pre-infection.
This spontaneous healing process, however, is variable. While some individuals experience swift resolution of symptoms within months, others remain trapped in a chronic loop of neuroinflammation and autonomic nervous system dysfunction (dysautonomia). For these patients, passive waiting is insufficient, prompting the medical community to actively investigate therapeutic interventions designed to accelerate neuroplastic recovery and extinguish lingering inflammation.
Medical and Non-Pharmacological interventions: Can we speed up recovery?
As clinical trials mature, researchers are beginning to map out evidence-based protocols aimed directly at reversing or managing the neurological footprint of long COVID. Major multi-site initiatives, such as the RECOVER-NEURO clinical trials, have started evaluating structured, non-drug interventions tailored to cognitive impairment. These strategies include:
Cognitive Rehabilitation and Brain Training: Structured virtual and group therapy programs (such as PASC-CoRE) combined with targeted computerized cognitive training (like BrainHQ) help patients retrain attention, working memory, and processing speed. These protocols rely on neuroplastic principles, actively challenging compromised neural pathways to rebuild synaptic strength.
Neuromodulation Techniques: Non-invasive brain stimulation methods, including transcranial direct current stimulation (tDCS), are being deployed to modulate cortical excitability, reduce localized neuroinflammation, and support the restoration of normal neural network firing patterns.
Cardiovascular and Autonomic Pacing: Because brain health is intimately tied to vascular tone and autonomic stability, specialized physical and occupational therapies focus on regulated exertion, pacing strategies, and cardiovascular conditioning designed to improve cerebral blood flow without triggering post-exertional malaise (PEM) crashes.
(This exploration continues in Part 2, where we will examine emerging pharmacological targets, the role of dopamine pathway restoration, lifestyle medicine, and what patients can realistically expect from their long-term recovery journey.)
Navigating the path of neural recovery: Therapeutic interventions and prognosis
As longitudinal tracking and neuroimaging studies continue to map the post-acute sequelae of SARS-CoV-2 infection, the clinical focus has shifted from merely documenting cerebral alterations to actively facilitating neurological healing. The core question, Is COVID-19 brain damage reversible?, does not yield a simple binary answer. Instead, modern neuroscience points toward a nuanced reality: while certain structural shifts and persistent neuroinflammatory processes can exert long-lasting effects, the human brain possesses a remarkable capacity for functional reorganization, metabolic repair, and structural adaptation.
The role of neuroplasticity and functional reorganization
At the microscopic level, the brain’s primary tool for overcoming injury is neuroplasticity, its ability to reorganize itself by forming new neural connections, bypassing damaged pathways, and strengthening alternative networks.
Clinical observations of individuals recovering from persistent cognitive deficits (frequently described as "brain fog") reveal that recovery is rarely instantaneous. Longitudinal assessments tracking patients years after initial infection indicate that slow, progressive clinical and cognitive improvements are entirely possible. Even when subtle gray matter volume reductions or microstructural alterations are detected via high-resolution neuroimaging, these changes do not automatically equate to permanent, irreversible cell death. In many cases, they reflect transient neuroinflammation, glial activation, or metabolic suppression that can gradually resolve as systemic immune homeostasis is restored.
Targeted Rehabilitation and behavioral interventions
Because cognitive symptoms often stem from disruptions in large-scale functional networks, such as those governing attention, working memory, and executive function, targeted therapies have emerged as vital catalysts for recovery.
Recent randomized clinical trials evaluating structured cognitive rehabilitation (CR) have demonstrated profound clinical utility. Tailored, goal-oriented cognitive therapies, focusing on individualized functional goals, pacing strategies, and compensatory network training, yield statistically significant and sustained improvements in daily functioning. Participants undergoing structured rehabilitation report substantial gains in goal attainment and task performance compared to standard care pathways, proving that active cognitive scaffolding helps the brain route around persistent deficits.
Simultaneously, large-scale initiatives like the RECOVER-NEURO program have explored diverse non-pharmacological modalities, including computerized cognitive training programs and non-invasive brain stimulation techniques (such as transcranial direct current stimulation), aiming to stimulate neuroplastic adaptation and alleviate persistent cognitive fatigue.
Pharmacological horizons and mechanistic targets
Beyond behavioral therapy, biomedical research increasingly targets the underlying biological drivers of neurological Post-Acute Sequelae of COVID-19 (PASC). Recent breakthroughs highlight specific mechanisms, such as long-term viral persistence in regions like the brainstem or localized dopaminergic dysregulation linked to motivational and motor slowing.
By identifying these precise pathophysiological pathways, such as inflammatory signaling cascades, microglial hyperactivity, or neurotransmitter imbalances, scientists are laying the groundwork for mechanism-driven therapeutics. Drug repurposing trials assessing anti-inflammatory agents, antivirals, and compounds that support dopaminergic function offer a promising horizon for arresting ongoing neuro-immune damage and accelerating biochemical recovery.
A framework for hope and management
Current evidence suggests that neurological impacts from COVID-19 are frequently dynamic rather than static. While the recovery timeline can be frustratingly protracted, the convergence of natural neuroplastic healing, sophisticated cognitive rehabilitation protocols, and emerging targeted medical interventions provides a strong foundation for clinical optimism. Recovery is rarely a passive waiting game; rather, it represents an active partnership between time, cellular healing, and dedicated neuro-rehabilitative strategies.