Unpacking the intersection of identity and Clinical psychology
However, as psychological science has advanced—and as marginalized communities have successfully advocated for self-determination—major medical institutions have shifted their stances. Today, the consensus within professional psychiatric and psychological organizations is unequivocal: asexuality is not a mental illness, a mental disorder, or a medical pathology. Instead, it is recognized as a valid, natural variation in human sexual orientation.
To truly understand why asexuality occupies its current status in modern science, we must explore how psychology defines sexual orientation, how diagnostic manuals have evolved to protect rather than pathologize diverse identities, and the critical distinction between a lack of sexual attraction and psychological distress.
Defining asexuality: Orientation vs. Pathology
To answer whether asexuality is a mental condition, one must first precisely define what asexuality actually is. In the lexicon of human sexuality, asexuality is generally defined as experiencing little to no sexual attraction to others. It is crucial to separate sexual attraction from sexual behavior or romantic attraction.
Asexuality is an orientation: Just as heterosexuality describes an attraction to a different gender, and homosexuality describes an attraction to the same gender, asexuality describes a general lack of intrinsic sexual attraction toward any gender.
The Spectrum (The "Ace" Umbrella): Asexuality is not a monolithic label. It exists on a broad spectrum that includes demisexuals (who only experience sexual attraction after forming a deep emotional bond) and gray-asexuals (who experience sexual attraction rarely or only under specific, limited circumstances).
Behavioral Independence: An asexual person may still choose to engage in sexual activity for various reasons, such as a desire to bond with a partner, curiosity, or for reproductive purposes, even in the absence of innate sexual attraction. Conversely, some asexual individuals are completely sex-repulsed or uninterested in participating in sexual acts.
Crucially, none of these variations imply a broken psychological mechanism. Much like being left-handed or having brown eyes, asexuality is an intrinsic characteristic of an individual's makeup rather than a symptom of a dysfunctional mind.
The historical context: Pathologizing normal variation
Historically, the medical establishment struggled to accommodate individuals who did not fit into standard sexual paradigms. For much of the 20th century, psychoanalytic and behavioral traditions viewed sex as essential to physical and mental health. Consequently, any individual who reported a lifelong absence of sexual desire was frequently subjected to diagnostic labels aimed at "fixing" or "curing" them.
For many years, conditions that mirrored low or absent sexual desire were blanketed under broad diagnostic categories. Patients, particularly women, were often diagnosed with frigidity, a deeply pejorative term that inherently framed a lack of sexual responsiveness as a personal failure or a psychological defect.
As empirical research grew and the asexual community gained visibility through digital platforms and grassroots activism in the late 1990s and early 2000s, researchers began to take a closer look at the data. Landmark studies spearheaded by psychologists and sexologists, such as Lori Brotto and Morag Yule, demonstrated that asexual individuals did not show higher rates of general psychopathology, personality disorders, or past trauma than the general population. In fact, when psychological distress or anxiety was present in asexual cohorts, follow-up research heavily correlated it with the social alienation, minority stress, and discrimination they faced in a hyper-sexualized society, rather than the asexuality itself.
The modern Diagnostic landscape: The DSM-5 and DSM-5-TR
The clearest institutional validation of asexuality's status as a non-pathological orientation can be found in the Diagnostic and Statistical Manual of Mental Disorders (DSM-5 and its text revision, the DSM-5-TR), published by the American Psychiatric Association (APA).
When clinicians evaluate disorders related to sexual desire, most notably Female Sexual Interest/Arousal Disorder (FSIAD) and Male Hypoactive Sexual Desire Disorder (HSDD), they look for a persistent reduction or absence of sexual interest. However, the modern diagnostic criteria explicitly carve out an exception for asexuality.
The text of the DSM explicitly mandates that clinicians must rule out alternative explanations before assigning a diagnosis of HSDD or FSIAD. Specifically, if a person’s low or absent sexual desire is better explained by their self-identification as asexual, a diagnosis of a sexual dysfunction cannot and must not be made.
This distinction introduces two vital safeguards for mental health diagnostics:
The Principle of Ego-Syntonicity: In psychology, a trait or identity is "ego-syntonic" when it aligns with the core needs, self-image, and desires of the individual. For an asexual person, their lack of sexual attraction feels natural and comfortable. They do not experience internal distress or a desire to change it.
The Requirement of Distress: A core criterion for any mental disorder in modern psychiatry is that the condition must cause "clinically significant distress or impairment" in social, occupational, or other important areas of functioning. Because asexuality in itself causes no intrinsic psychological harm, it fails the baseline definition of a mental disorder.
Navigating the nuances: Distinguishing asexuality from Sexual dysfunction
To accurately address whether asexuality is a mental condition, modern clinical psychology and sexology draw a sharp boundary between identity and dysfunction. The Diagnostic and Statistical Manual of Mental Disorders (DSM-5-TR) explicitly clarifies that a lack of sexual attraction or desire does not constitute a mental disorder if it does not cause marked personal distress or interpersonal difficulty.
When an individual identifies as asexual, their lack of sexual attraction is experienced as a stable, intrinsic orientation rather than a distressing loss. Conversely, conditions like Female Sexual Interest/Arousal Disorder (FSIAD) or Male Hypoactive Sexual Desire Disorder (HSDD) are defined by an unwanted, distressing change or deficit from a person's baseline, often accompanied by frustration, anxiety, or grief. Understanding this distinction safeguards individuals from harmful, pathologizing misdiagnoses.
The evolution of psychological and Psychiatric consensus
Historically, psychiatry was quick to pathologize any departure from conventional allosexual (non-asexual) behavior. Early psychoanalytic frameworks frequently viewed celibacy or lack of sexual desire as symptoms of neurosis, unresolved trauma, or arrested psychosexual development.
However, empirical research over the past two decades has thoroughly dismantled these outdated assumptions. Landmark studies by researchers such as Dr. Anthony Bogaert demonstrated that asexuality exists on a distinct spectrum of human sexual orientation, occurring independently of personality disorders, depression, or hormonal imbalances. Today, major psychological associations worldwide recognize asexuality as a normal, healthy variation of human diversity.
The intersection of asexuality, Mental health, and minority stress
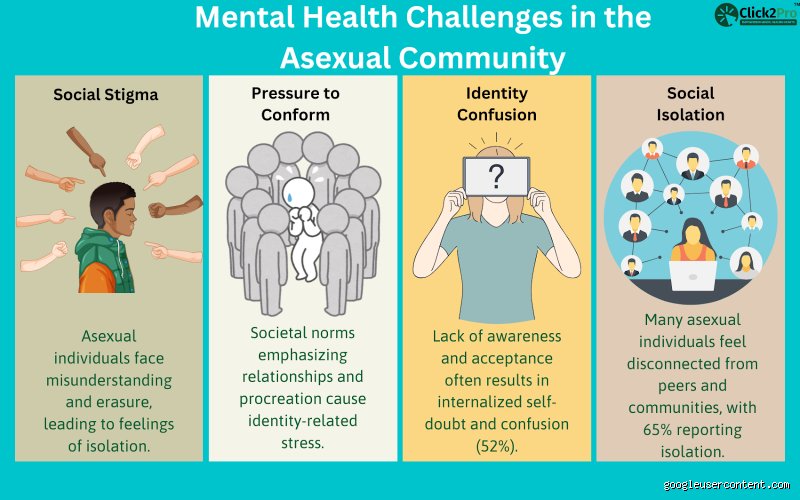
While asexuality is not a mental illness, asexual individuals frequently navigate unique mental health challenges. These struggles rarely stem from asexuality itself, but rather from minority stress, the chronic psychological friction caused by living in a hyper-sexualized society that devalues or erases non-sexual identities.
Invalidation and Erasure: Facing constant skepticism from peers, family members, and medical professionals who mistakenly label asexuality as a "phase" or a medical problem.
Internalized Amatonormativity: Struggling against societal pressures that falsely equate romantic coupling and sexual intimacy with a successful life.
Clinical Misdiagnosis: Encountering well-meaning therapists who attempt to "treat" or "cure" asexuality rather than affirming the client's identity.
Creating truly inclusive healthcare environments requires practitioners to cultivate cultural competency around the asexual spectrum. Affirming care validates the client's self-determination and focuses mental health treatment on coping strategies, community building, and self-acceptance.
Toward a fully inclusive paradigm of human sexuality
Determining whether asexuality is a mental condition is no longer a matter of scientific debate; the consensus is clear. Asexuality is a valid, natural sexual orientation, not a psychological disorder.
As psychological research and societal awareness continue to mature, the focus must shift from questioning the validity of asexual identities to dismantling systemic aphobia. By embracing a truly expansive understanding of human attraction, medicine and psychology can better support individuals across the entire spectrum of identity and experience.