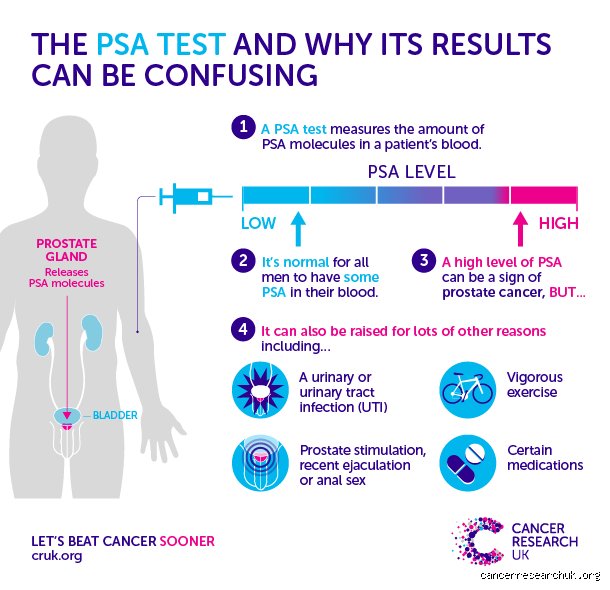
To comprehend the current clinical consensus, one must first examine the historical context of the biomarker's introduction. Discovered and subsequently commercialized in the late twentieth century, the PSA test measured a glycoprotein produced primarily by the epithelial cells of the prostate gland. Clinicians initially celebrated the assay because it offered a non-invasive window into an organ previously shrouded by anatomical obscurity. Before the advent of widespread PSA testing, prostate cancer was frequently detected only at advanced, symptomatic stages—often when bone metastases or severe urinary obstruction had already compromised patient survival. The promise of the PSA assay was intoxicating: catch the tumor while it is microscopic, confine it within the prostatic capsule, and eradicate it completely.
However, this mechanistic optimism overlooked a fundamental biological truth regarding human pathology: not all cancers behave with uniform aggression. The prostate gland is notoriously heterogeneous, harboring a spectrum of neoplastic lesions ranging from dormant, indolent cellular anomalies that will never threaten a patient’s life to highly aggressive, fast-moving adenocarcinomas capable of rapid metastasis. The fundamental flaw of the traditional PSA screening model lay in its inability to distinguish between these two drastically different clinical entities. A single elevated biomarker value merely signals an alteration in prostatic architecture, which can be triggered by benign prostatic hyperplasia, localized inflammation, recent physical friction, or a sluggishly progressive tumor.
As millions of asymptomatic men underwent routine biochemical profiling, the healthcare system encountered a massive surge in overdiagnosis. Overdiagnosis occurs when screening protocols identify histological cancers that are biologically insignificant. Autopsy studies historically demonstrated that a significant percentage of elderly men who die of unrelated causes harbor microscopic prostate carcinomas of which they were entirely unaware during life. When universal PSA screening was aggressively promoted, it cast a wide biochemical net, dragging these harmless cellular anomalies into the clinical spotlight. Patients were subsequently diagnosed with cancer, transforming healthy individuals into terrified oncology patients overnight.
The cascading sequence triggered by an elevated PSA reading frequently culminated in overtreatment. Once labeled with a malignancy, patients faced immense psychological pressure to pursue definitive therapy, whether via radical prostatectomy or localized radiation. These interventions carry substantial physical tolls. The delicate neurovascular bundles governing urinary continence and erectile function run immediately adjacent to the prostate gland. Consequently, radical surgical excision or high-dose radiation frequently resulted in permanent urinary incontinence, chronic bowel dysfunction, and profound erectile impotence. For thousands of men, the ultimate tragedy was that they were subjected to life-altering, debilitating morbidities for a disease that would have remained completely asymptomatic and benign throughout their natural lifespans.
Compounding the crisis of overdiagnosis was the high rate of false-positive results. The biochemical specificity of PSA is notoriously poor. An elevated reading frequently prompts invasive diagnostic follow-up, most notably transrectal or transperineal needle biopsies. These surgical procedures are not benign; they carry genuine risks of severe pelvic infection, sepsis, hemorrhage, and intense procedural anxiety. When multiplied across national screening cohorts, the cumulative toll of unnecessary biopsies revealed a healthcare intervention that was inflicting substantial harm while offering dubious net survival advantages for the general population.
Major health bodies, most notably the United States Preventive Services Task Force (USPSTF), meticulously evaluated large-scale randomized controlled trials, such as the Prostate, Lung, Colorectal, and Ovarian (PLCO) Cancer Screening Trial in the United States and the European Randomized Study of Screening for Prostate Cancer (ERSPC). These monumental studies yielded complex, sobering data. While the ERSPC trial suggested a modest reduction in prostate cancer-specific mortality for certain age brackets, the absolute risk reduction was remarkably small, and it came at an exorbitant price in treatment-related side effects. The PLCO trial, conversely, found no significant mortality benefit between routinely screened cohorts and control groups receiving standard care.
Faced with this unfavorable benefit-to-harm ratio, regulatory agencies issued decisive downgrades to universal screening recommendations, effectively altering the landscape of men's health. The medical establishment recognized that treating every detected anomaly as an emergency was a flawed strategy. Instead, contemporary oncology shifted away from blunt population-wide surveillance toward sophisticated risk stratification, active surveillance protocols for low-risk tumors, and supplementary diagnostic modalities like multiparametric magnetic resonance imaging (MRI) to better characterize suspicious lesions before committing patients to the operating table.
The cascade of interventions: Biopsies, complications, and quality of life
The decision by major health organizations—such as the U.S. Preventive Services Task Force (USPSTF), to step back from recommending routine, population-wide prostate-specific antigen (PSA) screening is rooted in a sobering medical reality: the intervention often inflicts more immediate harm than the disease it aims to prevent.
When a routine PSA blood test returns an elevated result, which can be triggered by benign prostatic hyperplasia (BPH), inflammation (prostatitis), or minor trauma rather than malignancy, it sets off a clinical cascade. The standard next step historically involved a transrectal ultrasound-guided core-needle biopsy.
Prostate biopsies are not benign procedures. They carry tangible medical risks, including:
Severe infections: Bacteria introduced during the biopsy can lead to painful urinary tract infections, acute prostatitis, and life-threatening sepsis requiring hospitalization.
Physical trauma and bleeding: Patients frequently experience persistent hematuria (blood in the urine), rectal bleeding, and hemospermia.
Psychological distress: A false-positive result introduces immense anxiety, casting a shadow of cancer fear over a patient long before any definitive diagnosis is made.
The dilemma of overdiagnosis and overtreatment
Perhaps the most compelling argument against universal PSA screening is the phenomenon of overdiagnosis. Prostate cancer exists on a wide biological spectrum. Many tumors found via elevated PSA are indolent, slow-growing, microscopic abnormalities that would never cause symptoms, metastasize, or threaten a man’s life span. Autopsy studies consistently reveal that a large percentage of older men die with prostate cancer, not from it.
However, once a cancer cell is identified under a microscope, human psychology and clinical momentum make it extraordinarily difficult to ignore. This leads directly to overtreatment, performing aggressive therapies like radical prostatectomy (surgical removal of the prostate) or external beam radiation on indolent cancers.
The side effects of these treatments frequently devastate a patient's quality of life:
Urinary incontinence: Ranging from stress leakage to complete loss of bladder control, requiring lifelong absorbent products.
Erectile dysfunction: Damage to the delicate neurovascular bundles surrounding the prostate often results in permanent or long-term impotence.
Bowel complications: Radiation therapy frequently causes chronic proctitis, rectal bleeding, urgency, and loose stools.
Modern nuance: Shared Decision-Making and risk stratification
Because wholesale abandonment of screening led to a concerning uptick in late-stage, metastatic presentations, modern medical guidelines have evolved away from a blanket "never screen" rule toward a framework of informed, individualized decision-making.
For men aged 55 to 69, health authorities now emphasize shared decision-making. Patients are encouraged to weigh the statistical reduction in prostate cancer mortality against the very real risks of unnecessary biopsies and life-altering treatment side effects, factoring in personal values, family history, and baseline risk (such as African ancestry).
Diagnostic pathways have modernized. Rather than rushing straight to a blind biopsy upon seeing an elevated PSA, clinicians increasingly utilize multiparametric MRI (mpMRI), risk-calculator algorithms, and active surveillance (monitoring low-risk tumors closely rather than treating them immediately). This nuanced approach helps separate aggressive, dangerous malignancies from harmless cellular anomalies, protecting patients from the historical harms of the PSA test while still catching lethal disease before it spreads.