The Nocturnal paradox of the human digestive tract
When this biological design is overridden, and an individual is abruptly jolted awake by the urgent, distressing compulsion to pass loose or watery stools, it signals a significant disruption in normal gastrointestinal homeostasis. Clinically referred to as nocturnal diarrhea or nocturnal stooling, this phenomenon is vastly different from a routine daytime bout of an upset stomach. While daytime diarrhea can frequently be attributed to transient dietary indiscretions, mild viral bugs, or situational stress, true nocturnal diarrhea, episodes that specifically interrupt sleep, demands a much closer medical investigation.
Understanding why diarrhea happens more frequently or intensely at night requires an exhaustive exploration of human gastroenterology, neuro-gastroenterology, endocrinology, and immunology. It involves looking at how the enteric nervous system communicates with the central nervous system, how fluid and electrolyte transport across the intestinal mucosa goes awry, and how systemic health conditions can subvert the body's natural nighttime slowdown. In this comprehensive expert analysis, we will examine the intricate physiological mechanisms, underlying medical pathologies, hormonal fluctuations, and environmental triggers that conspire to turn the resting night into a period of acute gastrointestinal distress.
The normal physiology of nighttime Bowel control
To fully appreciate why nocturnal diarrhea occurs, one must first understand how a healthy gastrointestinal tract maintains continence and dormancy throughout the night hours. The gut is governed by its own extensive, semi-autonomous neural network known as the enteric nervous system (ENS), which is frequently dubbed the body’s "second brain." Containing hundreds of millions of neurons embedded within the lining of the gastrointestinal tract, the ENS manages local blood flow, mucosal transport, and smooth muscle contractions independently, while maintaining constant bidirectional communication with the central nervous system via the vagus nerve and the gut-brain axis.
During the day, the gastrointestinal tract is highly responsive to external stimuli. The ingestion of food triggers the gastrocolic reflex, a physiological response wherein the distension of the stomach and the presence of nutrients in the upper intestine signal the colon to ramp up motor activity, clearing space for incoming meals. This reflex naturally promotes postprandial (post-meal) bowel movements. However, as evening approaches and fasting begins, the central nervous system shifts its autonomic balance. Sympathetic tone diminishes while parasympathetic modulation shifts to support restorative housekeeping functions, but critically, the motor programs driving high-amplitude propagating contractions (the powerful waves that push stool toward the rectum) are heavily suppressed.
Nocturnal fluid regulation in a healthy colon is exceptionally efficient. The primary role of the large intestine is not merely storage, but the aggressive extraction of water and electrolytes. As chyme (partially digested food) moves through the small intestine and enters the colon, specialized epithelial cells absorb sodium, chloride, and water against osmotic gradients. By the time waste reaches the sigmoid colon and rectum, approximately 90% of the water delivered from the upper GI tract has been reclaimed, resulting in a formed, cohesive stool.
At night, this absorptive capacity is optimized because transit time is prolonged. The extended duration that stool remains in contact with the colonic mucosa allows for maximum water extraction. Nocturnal diarrhea represents a catastrophic failure of this delicate orchestration: colonic motility fails to slow down (or conversely, accelerates), fluid secretion swamps absorptive capacity, and the rectal sensory thresholds become hypersensitive, overriding the brain's sleep centers to demand immediate evacuation.
Secretory versus osmotic Mechanisms in the dark
At a cellular level, diarrhea is broadly categorized into two major pathophysiological types that behave quite differently across the 24-hour circadian cycle: osmotic diarrhea and secretory diarrhea. Understanding how these mechanisms operate overnight sheds light on why certain conditions exclusively or predominantly manifest during sleep.
Osmotic diarrhea and Late-Day dietary load
Osmotic diarrhea occurs when osmotically active, poorly absorbed solutes remain within the lumen of the intestine. These solutes draw water out of the body's tissues and into the bowel via osmosis, preventing normal fluid reabsorption and resulting in watery stools.
When osmotic diarrhea presents at night, it is almost invariably linked to late-day ingestion of specific substances that the small intestine or colon fails to digest or absorb. Common culprits include:
Sugar Alcohols (Polyols): Artificial sweeteners such as sorbitol, mannitol, xylitol, and maltitol, frequently found in sugar-free gums, diet candies, and pharmaceutical syrups, are notoriously difficult for the human small intestine to absorb efficiently. When consumed in the late afternoon or evening, these compounds transit slowly through the digestive tract. By the time they reach the colon, their osmotic pull draws massive amounts of water into the bowel lumen, triggering sudden, urgent diarrhea in the middle of the night.
Lactose and Fructose Intolerance: Individuals with lactase deficiency (the inability to break down the sugar in dairy products) or fructose malabsorption who consume trigger foods or beverages close to bedtime will experience fermentation by colonic bacteria overnight. This bacterial breakdown produces short-chain fatty acids and gases, alongside an osmotic shift that liquefies stool contents just as the individual is deep into their sleep cycle.
Bile Acid Malabsorption (BAM): The liver produces bile acids to aid in the digestion of fats. Normally, these acids are reabsorbed in the terminal ileum (the final section of the small intestine). If the terminal ileum is damaged, inflamed, or has been surgically removed (such as in Crohn’s disease or past bowel resections), unabsorbed bile acids spill over into the colon. Bile acids are potent stimulants of colonic secretion; they irritate the mucosal lining and actively force water and electrolytes into the bowel lumen. Because fat digestion often occurs across heavy evening meals, BAM frequently manifests as explosive, watery nocturnal or early-morning diarrhea.
Secretory diarrhea: The autonomous overdrive
Unlike osmotic diarrhea, which typically resolves when the patient fasts (stops eating), secretory diarrhea persists even during complete fasting. This makes secretory processes the primary driver of true, pathological nocturnal diarrhea that wakes a person from a sound sleep regardless of when or what they last ate.
In secretory diarrhea, the epithelial cells of the intestine undergo a pathological shift: instead of absorbing water and electrolytes, they actively and continuously secrete massive quantities of chloride and water into the gut lumen. This process is driven by internal signaling molecules, hormones, bacterial toxins, or localized inflammation. Because secretory mechanisms are entirely independent of food intake, they operate continuously around the clock. When an individual lies down to sleep, the ongoing, unregulated secretion accumulates in the large intestine, rapidly filling the rectal vault and triggering stretch receptors that fire emergency neural signals to the brain, piercing through sleep paralysis and deep sleep stages to force an immediate awakening.
The Gut-Brain axis and circadian rhythms in digestion
The human digestive system does not operate in isolation from the body's master biological clock located in the suprachiasmatic nucleus of the hypothalamus. Circadian rhythms dictate the temporal organization of nearly every physiological parameter, including gastrointestinal motility, gastric acid secretion, mucosal blood flow, and immune cell trafficking within the gut wall.
Disruptions in circadian biology, whether caused by shift work, chronic sleep deprivation, jet lag, or primary sleep disorders like obstructive sleep apnea, have profound cascading effects on gut function. Stress hormones, particularly cortisol, follow a distinct diurnal curve, peaking shortly after waking and reaching their lowest trough around midnight or early sleep phases. However, chronic psychological stress, anxiety disorders, and hyper-arousal states can deregulate this axis, leading to nocturnal surges in corticotropin-releasing hormone (CRH) and autonomic nervous system activation.
CRH receptors are heavily distributed throughout the gastrointestinal tract. When nocturnal anxiety or stress spikes late in the evening, it can stimulate colonic motor activity, effectively bypassing the normal nighttime slowdown. While functional gastrointestinal disorders like Irritable Bowel Syndrome (IBS) are predominantly daytime phenomena, and true IBS rarely wakes a patient from deep sleep, severe somatic anxiety and autonomic dysregulation can sometimes blur these lines, provoking nocturnal bowel urgency that mimics more ominous pathology.
--- [The article continues with detailed sections on specific organic diseases, neurological factors, diagnostic pathways, and management strategies...]
[ ]
[]
This educational video provides a gastroenterologist's perspective on why waking up at night to pass stool is a key clinical signal requiring medical evaluation.
Bridging the gap: Understanding the physiology of Nocturnal Bowel movements
To fully grasp why nocturnal diarrhea occurs, we must look closely at how our autonomic nervous system regulates gastrointestinal activity around the clock. During the day, the sympathetic nervous system ("fight or flight") and the parasympathetic nervous system ("rest and digest") coordinate a continuous dance of nutrient breakdown, water absorption, and peristalsis.
However, as evening transitions into deep sleep, the body undergoes a profound shift. Healthy circadian rhythms dictate that core body temperature drops, melatonin production surges, and the enteric nervous system (often called the body's "second brain") dials down colonic motility by roughly half. This natural braking mechanism is precisely why most healthy humans can sleep uninterrupted for seven to eight hours without experiencing bowel urgency.
When diarrhea breaks through this heavily guarded resting state and forces you awake, it signifies that an underlying pathological process has completely overridden the body's natural nocturnal inhibitors. Instead of resting, the colon continues or even accelerates its wave-like contractions, driving fluid and waste toward the rectum while the internal anal sphincter's resting tone may be temporarily compromised.
Clinical categories and deeper pathologies
Medical professionals generally separate nighttime bowel disruptions into two main categories: acute episodes, which usually stem from sudden infections or dietary indiscretions, and chronic nocturnal diarrhea, which persists for weeks and serves as a classic clinical "alarm symptom".
Secretory Mechanisms: Conditions like bile acid malabsorption or microscopic colitis cause the intestinal lining to continuously pump water and electrolytes into the gut lumen, completely independent of whether you are fasting or sleeping.
Inflammatory Conditions: Inflammatory Bowel Diseases (IBD) such as Crohn's disease and ulcerative colitis introduce chronic immune-mediated inflammation. This active tissue damage prevents proper water reabsorption and triggers persistent secretory activity that does not stop when the lights go out.
Autonomic Neuropathy: In patients with long-standing or poorly controlled diabetes, high blood sugar levels can damage the autonomic nerves governing the gastrointestinal tract. This nerve damage removes the orderly control of transit times, leading to erratic, urgent bowel movements during sleep.
Practical management and diagnostic steps
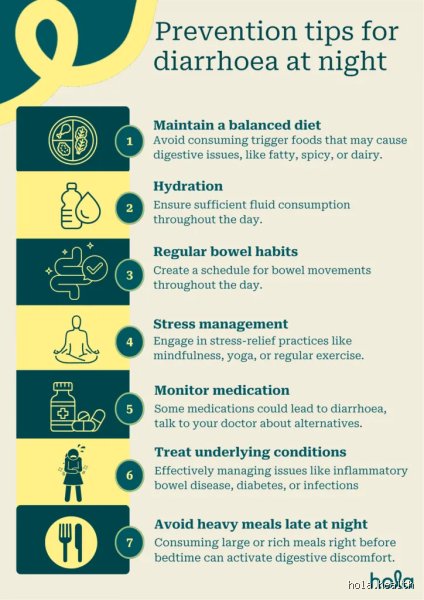
If nighttime diarrhea occurs only rarely after consuming heavy, fatty meals, artificial sweeteners, or excess alcohol late at night, simple lifestyle modifications, such as finishing your last meal two to three hours before bed and limiting late-day caffeine, are often sufficient to restore normal sleep continuity.
However, if nocturnal episodes happen repeatedly, are accompanied by fever, unexplained weight loss, or blood in the stool, it is essential to partner with a healthcare provider. A comprehensive diagnostic workup, ranging from routine blood work and stool cultures to targeted endoscopies or colonoscopies, can unearth the root cause, ensuring you receive the appropriate clinical treatment to quiet your digestive tract and help you reclaim a full night of restful sleep.
A GI Doctor Explains Nocturnal Stooling
This video provides an expert gastroenterologist's breakdown of why nocturnal bowel movements occur and which clinical signs require medical evaluation.