There is perhaps few experiences as universally humbling, disruptive, and downright miserable as the sudden onset of acute gastrointestinal distress. Whether it hits you midway through a workday, wakes you up in the dead of night with violent abdominal cramps, or forces an immediate sprint to the nearest restroom, the immediate aftermath is always the same: a frantic mental rewind of everything you consumed over the past twenty-four to forty-eight hours.
Inevitably, the central question arises: Is this just ordinary diarrhea, or did I contract food poisoning?
At first glance, the two terms are frequently conflated because they share an unmistakable, unpleasant overlap in physical symptoms—most notably loose, watery stools and urgent abdominal discomfort. However, medically speaking, treating them as interchangeable is a mistake that can obscure the true underlying cause of your illness, delay appropriate recovery strategies, and prevent you from recognizing when a condition requires professional medical intervention.
To demystify what is happening inside your digestive tract, we must look beyond the bathroom door and examine the complex intersection of microbiology, clinical timelines, and physiological warning signs.
1. The Core misunderstanding: Symptom versus cause
To properly differentiate between food poisoning and general diarrhea, we must first establish a fundamental medical distinction: diarrhea is a symptom, whereas food poisoning is a specific cause.
Diarrhea is not a disease in its own right. It is a physiological response—a defense mechanism deployed by your gastrointestinal system. When your intestines detect irritation, inflammation, or toxins, they dramatically speed up peristalsis (the wave-like muscle contractions that move food through your gut) and flood the intestinal lumen with water to flush out the offending agent before it can cause deeper systemic harm. Because your gut reacts this way to a wide variety of triggers, general diarrhea can be caused by everything from stress, anxiety, and artificial sweeteners to dietary changes, caffeine sensitivity, irritable bowel syndrome (IBS), or mild viral infections.
Food poisoning (medically referred to as foodborne illness), on the other hand, is a distinct pathology. It occurs specifically when you ingest food or beverages contaminated by infectious organisms, such as bacteria, viruses, parasites, or toxic chemicals and preformed bacterial toxins. While diarrhea is almost always a primary component of food poisoning, food poisoning itself brings along a distinct constellation of systemic symptoms that separate it from a routine, isolated bout of loose stools.
Understanding this relationship shifts the diagnostic framework: you are not choosing between two completely different types of bowel movements; rather, you are trying to determine whether your loose stools are the result of everyday gut irritability or an acute biological assault originating from your last meal.
2. The chronology clock: Why timing is your best diagnostic tool
If you want to play detective with your own stomach bug, the single most valuable piece of evidence at your disposal is not the color or consistency of your stool, it is a clock. The incubation period, the precise amount of time that elapsed between eating a suspect meal and the first appearance of symptoms, serves as a biological fingerprint for what kind of pathogen or toxin has invaded your system.
A. Ultra-Rapid Onset (30 minutes to 6 hours)
If your symptoms explode onto the scene within a mere fraction of a day after eating, you are almost certainly dealing with a preformed bacterial toxin rather than a living, multiplying infection.
Classic culprits here include Staphylococcus aureus or Bacillus cereus. These bacteria can multiply rapidly in food left at improper temperatures (such as picnic salads, buffets, or rice dishes left sitting out). Crucially, the bacteria release toxins directly into the food before you even eat it. Even if the food was subsequently reheated (which might kill the live bacteria), the heat-stable toxins remain intact.
When you ingest them, your body reacts instantly. The hallmark of this rapid-onset category is violent, sudden vomiting accompanied by intense upper abdominal cramping, often appearing within 1 to 6 hours, while diarrhea may follow slightly later.
B. Moderate Onset (6 to 24 hours)
When symptoms manifest within a half-day to a full day, healthcare providers often suspect bacterial agents like Clostridium perfringens. Often dubbed the "buffet germ," C. perfringens thrives in large pots of meat, poultry, or gravies that are cooked and then held at unsafe holding temperatures. Once ingested, the bacteria produce toxins directly inside your intestines.
This category typically presents with severe, sharp abdominal cramps and watery diarrhea, though vomiting and fever are less common. It is frequently mistaken for a sudden case of ordinary indigestion or mild viral gastroenteritis until you notice that others who shared the same meal are experiencing the exact same timeline.
C. Delayed Onset (24 hours to several days)
If your symptoms take a full day, two days, or even longer to appear, the diagnostic picture widens significantly. This timeline can point toward slower-acting bacterial infections like Salmonella, Campylobacter, or Escherichia coli (E. coli), or it can point toward viral pathogens like Norovirus (commonly, though inaccurately, called the "stomach flu").
Bacterial infections like Salmonella (often from undercooked poultry, eggs, or unpasteurized dairy) or E. coli (frequently linked to ground beef or contaminated produce) require time for the ingested bacteria to colonize and invade the lining of your intestinal tract. This delay means you might completely forget the specific meal that made you sick.
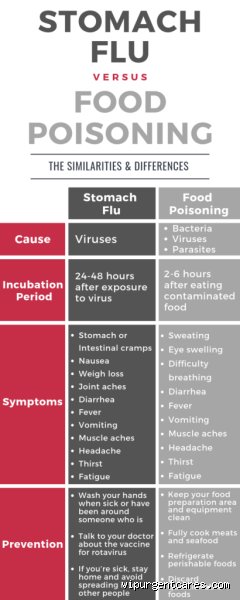
Viral gastroenteritis (Norovirus or rotavirus) typically takes anywhere from 12 to 48 hours to incubate after exposure. Unlike true food poisoning, which usually traces back to a specific contaminated food item, viral bugs are frequently spread directly from person to person or via contaminated surfaces.
3. Deconstructing the clinical presentation: Symptom clustering
Because general diarrhea can present as loose or watery stools on its own without making you feel systematically unwell, true food poisoning almost always announces itself through a cluster of accompanying symptoms. To distinguish between a routine digestive upset and foodborne illness, look closely at how the symptoms group together.
The domination of upper vs. Lower GI Symptoms
Vomiting-Dominant Profiles: If your illness starts with explosive, uncontrollable vomiting that completely overshadows everything else, your body is actively trying to expel a toxin or acute irritant from your upper stomach. This strongly points away from ordinary dietary diarrhea and heavily toward food poisoning or a acute viral pathogen like Norovirus.
Stool-Dominant Profiles: If you have zero nausea, no vomiting, and no fever, but your bowel movements have suddenly turned loose, frequent, and watery, you are more likely looking at general diarrhea. This can be provoked by something as benign as eating too much sugar substitute, consuming an unfamiliar spice, reacting to a mild medication change, or dealing with temporary stress-induced gut motility changes.
The presence (or absence) of Fever
A low-grade or high-grade fever is one of the most reliable discriminators in modern gastroenterology.
Ordinary, non-infectious diarrhea, such as that caused by dietary indiscretion, irritable bowel flare-ups, or mild stress, never causes a fever. Your immune system is not fighting an invader; your gut is simply reacting to an irritant or motility shift.
Conversely, many forms of food poisoning (particularly those caused by invasive bacteria like Salmonella, Campylobacter, or severe strains of E. coli) trigger an immune response that raises your core body temperature. If your loose stools are accompanied by chills, body aches, and a measured fever over 100.4°F (38°C), you are dealing with an infectious process, either foodborne bacteria or a systemic viral gastroenteritis.
Diagnostic clues: Laboratory testing and clinical evaluation
While clinical history and symptom profiling provide a robust foundation for distinguishing food poisoning from routine infectious or functional diarrhea, definitive diagnosis often requires clinical evaluation, especially when symptoms persist or worsen. In standard cases of mild acute gastroenteritis, healthcare providers rarely order immediate laboratory tests because most episodes are self-limiting and resolve within a few days with supportive care. However, when symptoms are severe, prolonged, or accompanied by systemic red flags, diagnostic testing becomes critical.
Stool studies form the cornerstone of investigating persistent or severe diarrheal illnesses. A routine stool culture looks for common bacterial pathogens such as Salmonella, Campylobacter, Shigella, and E. coli. In recent years, multiplex polymerase chain reaction (PCR) stool panels have revolutionized diagnostics. These molecular tests can simultaneously detect a wide array of bacterial, viral (such as norovirus and rotavirus), and parasitic agents (such as Giardia and Cryptosporidium) within hours, often yielding higher sensitivity than traditional culture methods.
Clinicians may order a stool occult blood test or fecal leukocyte analysis to check for inflammation and tissue invasion. The presence of white blood cells or gross blood in the stool strongly points toward an invasive bacterial or inflammatory etiology (classic hallmarks of severe food poisoning or inflammatory bowel flare-ups) rather than a simple osmotic or viral secretory diarrhea. In cases of severe dehydration or systemic toxicity, complete blood counts (CBC), serum electrolytes, and kidney function tests (such as creatinine and BUN) are vital to assess electrolyte imbalances, hemoconcentration, and potential acute kidney injury.
Bacterial, Viral, and Parasitic culprits: What distinguishes them?
Understanding the specific organism involved helps clarify whether an illness stems from a distinct foodborne outbreak or broader gastrointestinal disturbances.
Bacterial Pathogens (Primary Drivers of Food Poisoning): Bacteria are the most notorious culprits behind acute food poisoning. Organisms like Staphylococcus aureus or Bacillus cereus produce pre-formed toxins in improperly stored food, leading to rapid-onset vomiting and diarrhea within hours of ingestion. Conversely, invasive bacteria like Salmonella and Campylobacter have a longer incubation period (12 to 72 hours) and cause inflammatory diarrhea characterized by high fever, severe abdominal cramping, and bloody stools. E. coli O157:H7, often linked to undercooked beef or contaminated produce, produces Shiga toxins that can cause severe hemorrhagic colitis and, in vulnerable populations, hemolytic uremic syndrome (HUS).
Viral Pathogens: Viruses such as norovirus and rotavirus are exceptionally contagious and spread readily via person-to-person contact or contaminated environmental surfaces, making them frequent causes of both community outbreaks and "stomach flu." While viral gastroenteritis can be foodborne (such as an infected food handler contaminating a salad), it typically presents with a balanced mix of nausea, watery diarrhea, and low-grade fever, resolving rapidly within 24 to 72 hours.
Parasitic Pathogens: Parasites like Giardia duodenalis or Cryptosporidium typically result from contaminated water or food and cause subacute to chronic diarrhea. Unlike rapid-onset food poisoning, parasitic infections often feature foul-smelling, greasy stools, profound bloating, and gas that can persist for weeks if left untreated.
Critical red flags: When to seek immediate medical attention
Distinguishing between routine, mild diarrhea and severe food poisoning is vital, but recognizing when either condition crosses the threshold into a medical emergency is paramount. Most cases of acute gastroenteritis improve with rest and hydration at home, but certain "red flag" symptoms demand immediate professional evaluation:
Signs of Severe Dehydration: Inability to keep fluids down due to persistent vomiting, extreme thirst, dry mouth, little to no urination for eight hours or more, severe dizziness, lightheadedness upon standing, or lethargy and confusion.
Blood or Pus in the Stool: The presence of visible blood, black tarry stools, or pus indicates mucosal injury and invasive bacterial infection or severe inflammatory pathology.
High Fever: A persistent oral temperature exceeding 102°F (38.9°C) strongly suggests an invasive bacterial or systemic infection rather than a mild viral bug.
Intense, Localized Abdominal Pain: While generalized cramping is normal with both diarrhea and food poisoning, severe, sharp, or localized abdominal pain (especially in the lower right quadrant) can mimic appendicitis or indicate ischemic colitis, bowel perforation, or toxic megacolon.
Prolonged Duration: Diarrhea that worsens or fails to show signs of improvement after 48 to 72 hours in adults (or 24 hours in infants and children) requires medical assessment.
Neurological Symptoms: Visual disturbances, muscle weakness, tingling sensations, or descending paralysis can indicate rare but life-threatening neurotoxic food poisonings, such as botulism.
Evidence-Based management: Hydration, diet, and medication myths
When managing acute diarrhea or food poisoning, modern evidence-based medicine emphasizes supportive care while debunking several long-standing nutritional and pharmacological myths.
The Foundation: Rehydration
The single most critical intervention is preventing and treating dehydration. Water alone is insufficient for severe fluid losses because diarrhea and vomiting deplete essential electrolytes (sodium, potassium, and chloride). Oral Rehydration Solutions (ORS), formulated with precise ratios of glucose and electrolytes, utilize the sodium-glucose cotransport mechanism in the small intestine to maximize water absorption. For mild cases, diluted broths, electrolyte sports drinks, and clear fluids suffice, but severe volume depletion may require intravenous (IV) fluid resuscitation in an urgent care or hospital setting.
Nutritional protocols: Beyond the BRAT diet
For decades, the BRAT diet (Bananas, Rice, Applesauce, Toast) was universally prescribed for gastrointestinal illness. Modern pediatric and gastroenterological guidelines, however, recommend returning to a normal, age-appropriate diet as soon as hydration is established, typically within 24 hours. Bland, easily digestible foods like lean proteins, oatmeal, cooked vegetables, and crackers can be introduced gradually. Highly sugary foods, dairy products, caffeine, alcohol, and spicy or fatty foods should be avoided temporarily, as they can exacerbate osmotic diarrhea or irritate the recovering intestinal mucosa.
The Role of Medications
Antimotility Agents: Over-the-counter medications like loperamide slow intestinal transit. While safe and effective for mild, non-invasive watery diarrhea, they are strictly contraindicated in cases of suspected invasive bacterial food poisoning or bloody diarrhea. Slowing gut motility traps toxins and invasive pathogens in the gastrointestinal tract, potentially prolonging illness or precipitating severe systemic complications like toxic megacolon.
Antibiotics: Antibiotics are generally not recommended for uncomplicated acute gastroenteritis because the vast majority of cases are viral or self-limiting bacterial infections that resolve without antimicrobial intervention. Inappropriate antibiotic use contributes to antibiotic resistance and can trigger Clostridioides difficile infection. Antibiotics are reserved for laboratory-confirmed bacterial pathogens, high-risk patients (such as the immunocompromised or elderly), or severe systemic illness.
Probiotics: Emerging evidence suggests that specific probiotic strains (such as Saccharomyces boulardii or Lactobacillus rhamnosus GG) may modestly shorten the duration of infectious diarrhea by restoring gut microbiota balance, though they should be used adjunctively rather than as a primary cure.
Post-Infectious sequelae and Long-Term gut health
For most individuals, acute food poisoning or infectious diarrhea resolves completely within a week, leaving no lasting structural damage. However, the gastrointestinal tract can experience temporary or long-term functional changes following a severe bout of gastroenteritis.
Post-infectious irritable bowel syndrome (PI-IBS) is a well-documented phenomenon where individuals develop chronic abdominal pain, bloating, and altered bowel habits (predominantly diarrhea-predominant IBS) long after the initial pathogen has been cleared from their system. This occurs due to lingering low-grade mucosal inflammation, altered gut motility, subtle changes in intestinal permeability (leaky gut), and dysbiosis (an imbalance in the gut microbiome).
Certain bacterial infections can trigger immune-mediated complications. For example, infections caused by Campylobacter jejuni, Salmonella, or Shigella are established triggers for reactive arthritis (formerly known as Reiter's syndrome), an inflammatory joint condition that manifests weeks after the gastrointestinal illness subsides. Recognizing these potential sequelae underscores the importance of prompt diagnosis, appropriate medical management, and careful post-illness dietary recovery to support mucosal healing.
Prevention strategies: Safeguarding your gut health
While distinguishing between food poisoning and general diarrhea is essential for treatment, preventing these illnesses in the first place remains the gold standard of gastrointestinal health. Practicing robust food safety and hygiene protocols drastically reduces the risk of acute infections:
Practice the Four Core Food Safety Steps: Clean hands, utensils, and surfaces frequently; separate raw meats, poultry, seafood, and eggs from ready-to-eat foods to prevent cross-contamination; cook foods to safe internal temperatures verified by a food thermometer; and chill perishable foods promptly within two hours of preparation (or one hour if ambient temperatures exceed 90°F / 32°C).
Maintain Hand Hygiene: Thorough handwashing with soap and water for at least 20 seconds before eating, preparing food, and after using the restroom or handling raw meat is the most effective defense against contagious viral pathogens like norovirus.
Exercise Caution When Traveling: When visiting regions with unfamiliar sanitation standards, adhere strictly to the rule of thumb: "Boil it, cook it, peel it, or forget it." Avoid tap water, ice cubes made from tap water, raw street vendor foods, and unpasteurized dairy products.
Conclusion
Navigating the spectrum between food poisoning and routine diarrhea requires careful observation of onset timelines, accompanying symptoms, and clinical context. While food poisoning typically strikes abruptly after a suspect meal with prominent nausea and vomiting, general diarrhea can stem from a vast array of infectious, dietary, or functional triggers with more variable presentations. By understanding the underlying pathophysiology, recognizing critical red flags, prioritizing evidence-based hydration, and practicing diligent food safety, patients and healthcare providers alike can ensure swift recovery and long-term gastrointestinal resilience.