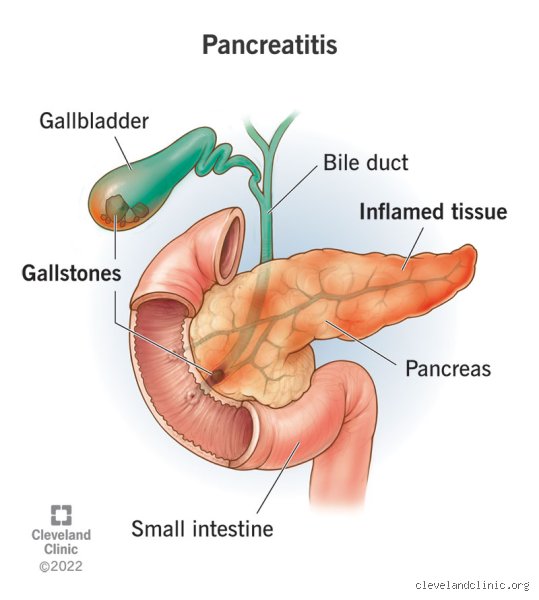
The pancreas is an extraordinary, dual-purpose organ tucked deeply behind the stomach in the upper abdomen. Balancing both exocrine duties—secreting powerful digestive enzymes into the small intestine—and endocrine functions—producing vital hormones like insulin and glucagon to regulate blood sugar—the pancreas operates as a metabolic powerhouse.
However, when this delicate gland becomes inflamed, a condition known as pancreatitis, its own digestive enzymes can prematurely activate inside the tissue. Instead of traveling safely to the gut to break down food, these enzymes begin to digest the pancreas itself, sparking a cascade of localized tissue destruction, severe pain, and systemic inflammation.
Bringing down pancreas inflammation requires a multi-layered clinical approach. Whether addressing acute attacks triggered by gallstones or managing the chronic, smoldering burn of long-term tissue damage, modern medical strategy focuses on interrupting autodigestion, restoring systemic homeostasis, and removing the underlying triggers.
1. The Anatomy of Pancreatic Inflammation: Understanding the Trigger Cascade
To understand how to calm pancreatic inflammation, one must first comprehend how the fire starts. Under normal physiological conditions, the acinar cells of the exocrine pancreas synthesize digestive enzymes in an inactive form, known as zymogens (such as trypsinogen). These are packaged securely and transported down the pancreatic duct system, only becoming active when they reach the alkaline environment of the duodenum.
When a noxious stimulus disrupts this cellular compartmentalization, the intracellular activation of trypsinogen into trypsin triggers a catastrophic domino effect:
Autodigestion: Active trypsin unleashes other proteolytic and lipolytic enzymes (like elastase and phospholipase A2), which degrade cell membranes, vascular walls, and surrounding fat tissue.
The Cytokine Storm: Damaged pancreatic cells release alarmins and pro-inflammatory cytokines (such as tumor necrosis factor-alpha and interleukins), recruiting neutrophils and macrophages into the gland.
Systemic Inflammatory Response Syndrome (SIRS): If unmitigated, local inflammation spills into the systemic circulation, potentially leading to multi-organ dysfunction syndrome (MODS), acute respiratory distress syndrome (ARDS), and hemodynamic instability.
Interrupting this dangerous cycle requires rapid medical stabilization, physiological rest, and targeted nutritional and pharmacological interventions.
2. Early Physiological Rest and Fluid Resuscitation
The foundational step in resolving acute pancreatic inflammation is shifting the gland into a state of metabolic and functional rest. For decades, strict "nil per os" (nothing by mouth) orders were enforced to prevent the pancreas from being stimulated by food intake. Contemporary clinical guidelines emphasize a more nuanced, physiology-guided approach.
The Role of Balanced Fluid Resuscitation
In the earliest stages of acute pancreatitis, massive capillary leak and third-spacing of fluids can cause profound hypovolemia. This results in hypoperfusion of the pancreas, worsening ischemia and converting mild inflammation into localized necrosis.
Goal-Directed Resuscitation: Early, targeted administration of balanced crystalloids—specifically lactated Ringer's solution—helps correct intravascular volume deficits and mitigate systemic acidosis more effectively than normal saline.
Avoiding Hypervolemia: Current consensus cautions against aggressive, unmonitored fluid loading, which is linked to increased rates of pulmonary edema, abdominal compartment syndrome, and higher mortality. Instead, clinicians utilize moderate, continuous fluid titration guided by clinical markers such as mean arterial pressure, urine output, and hematocrit normalization.
Enteral Nutrition vs. Bowel Rest
While traditional protocols kept patients fasting for extended periods, modern evidence demonstrates that early enteral nutrition (feeding via the gut) preserves intestinal mucosal integrity, prevents bacterial translocation from the gut into pancreatic necrosis collections, and significantly shortens hospital stays. For mild cases, oral feeding with a low-fat, solid diet can be resumed safely as soon as abdominal pain subsides and appetite returns. In severe or necrotizing cases, nasoenteric tube feeding is initiated early to bypass gastric stimulation while maintaining nutritional support.
3. Pharmacological Interventions and Pain Management
Controlling agonizing upper abdominal pain is not merely a matter of patient comfort; it is a physiological necessity. Severe pain triggers a neuroendocrine stress response that exacerbates systemic inflammation and causes abdominal wall muscle spasm, worsening respiratory mechanics.
Analgesia: Potent opioid analgesics (such as hydromorphone or fentanyl) delivered via patient-controlled analgesia (PCA) or systematic dosing are frequently required to manage moderate-to-severe pain. Non-steroidal anti-inflammatory drugs (NSAIDs) may be utilized in specific, stable recovery windows under close monitoring.
Targeted Antibiotic Stewardship: Routine prophylactic antibiotics are no longer recommended for sterile acute pancreatitis or uncomplicated necrosis. Antibiotics are strictly reserved for cases with confirmed extra-pancreatic infections (such as cholangitis or urinary tract infections) or proven infected pancreatic necrosis identified via imaging and microbiological cultures.
4. Identifying and Eliminating Root Causes
To truly bring down pancreas inflammation for the long term, physicians must aggressively investigate and treat the primary etiology. The two most common culprits—accounting for the vast majority of cases—require distinct management pathways:
Gallstone Pancreatitis: When a gallstone migrates out of the gallbladder and obstructs the ampulla of Vater, pancreatic juices back up into the gland. Urgent diagnostic imaging (such as transabdominal ultrasound or endoscopic ultrasound) and early therapeutic endoscopic retrograde cholangiopancreatography (ERCP) are often deployed to relieve the biliary obstruction.
Alcohol-Induced Pancreatitis: Chronic or heavy alcohol consumption sensitizes pancreatic acinar cells to injury. Complete and permanent cessation of alcohol is non-negotiable for halting recurrent attacks and preventing the progression from acute episodes to irreversible chronic pancreatitis. Other metabolic contributors, such as severe hypertriglyceridemia (serum triglycerides exceeding 1,000 mg/dL), require rapid medical management using specialized lipid-lowering protocols, insulin infusions, or plasmapheresis to clear circulating free fatty acids that damage the microvasculature of the pancreas.
Part 3: Advanced Nutritional Strategies and Dietary Modulations
When managing pancreatitis, dietary intervention is not merely a supportive measure—it is a core physiological modulator of inflammation. The pancreas responds directly to the presence of macronutrients in the duodenum by secreting digestive enzymes and bicarbonate. Therefore, strategically managing what enters the gastrointestinal tract allows the organ to rest, recover, and downregulate inflammatory cascades.
The Role of Low-Fat Medical Nutrition Therapy
Fatty acids are potent triggers for the release of cholecystokinin (CCK), a hormone that stimulates pancreatic acinar cells to secrete digestive enzymes. In an inflamed pancreas, premature activation of these enzymes inside the tissue leads to autodigestion and sustained inflammation.
Restricting Dietary Fat: Limiting dietary fat intake to low levels (typically 20 to 30 grams per day during recovery phases, or as tailored by a clinical dietitian) minimizes CCK secretion. This reduces the workload on the exocrine pancreas.
Medium-Chain Triglycerides (MCTs): Unlike long-chain triglycerides, MCTs do not require pancreatic lipase or bile salts for absorption; they are absorbed directly via the portal venous system. Consequently, MCT oil can be utilized as an alternative energy source without triggering pancreatic stimulation.
Emphasizing High Biological Value Proteins: Adequate protein is vital for tissue repair and preventing muscle wasting during chronic illness, but it must be consumed in forms that do not over-stimulate digestive secretions. Lean poultry, egg whites, and plant-based protein isolates are frequently recommended.
Antioxidant Therapy and Micronutrient Repletion
Oxidative stress is a primary driver of tissue damage in both acute and chronic pancreatitis. The inflammatory response generates massive amounts of reactive oxygen species (ROS), depleting the body's natural antioxidant defenses and exacerbating cellular necrosis and fibrosis.
Specific Micronutrient Protocols: Clinical studies have explored high-dose antioxidant therapy—specifically combinations of Vitamin C, Vitamin E, selenium, and methionine—to scavenge free radicals. Selenium deficiency, in particular, is frequently observed in chronic pancreatitis and correlates with increased pain and disease severity.
Anti-Inflammatory Phytonutrients: Incorporating foods rich in polyphenols and flavonoids (such as berries, green tea, and turmeric extracts containing curcumin) can help modulate intracellular signaling pathways like NF-kB, suppressing the transcription of pro-inflammatory cytokines.
Part 4: Pharmacological Innovations and Targeted Interventions
While nutritional therapy provides the foundation, active inflammation often requires targeted pharmacological management to interrupt the underlying pathophysiological pathways. Medical science continues to refine both acute interventions and long-term disease-modifying therapies.
+-----------------------------------------------------------------+
| KEY PHARMACOLOGICAL TARGETS |
+-----------------------------------------------------------------+
| 1. Enzyme Suppression --> Minimizes autodigestion |
| 2. Cytokine Inhibition --> Blocks NF-kB & TNF-alpha pathways |
| 3. Fibrogenesis Block --> Prevents pancreatic stellate cells |
| 4. Pain Management --> Neuromodulators & multimodal analgesia|
+-----------------------------------------------------------------+
Interrupting the Inflammatory Cascade
In acute settings, research has focused on agents that can blunt the systemic inflammatory response syndrome (SIRS) associated with severe attacks.
Protease Inhibitors: Medications designed to inhibit trypsin and other premature intracellular enzymes aim to stop the autodigestive process at its inception. While clinical trial results have varied, research into specific synthetic protease inhibitors remains an active area of investigation.
Targeting Molecular Pathways: Novel biologic therapies are being evaluated for their ability to neutralize specific pro-inflammatory cytokines, such as tumor necrosis factor-alpha (TNF-) and interleukins (IL-1$\beta$, IL-6), which perpetuate pancreatic injury and lead to systemic complications.
Managing Chronic Fibrogenesis
Chronic pancreatitis is characterized by the progressive replacement of functional pancreatic parenchyma with scar tissue. This process is driven by the activation of pancreatic stellate cells (PSCs).
Stellate Cell Regulation: Emerging therapeutic strategies aim to keep PSCs in a quiescent state or induce apoptosis in active myofibroblasts. Agents that inhibit transforming growth factor-beta (TGF-) signaling or platelet-derived growth factor (PDGF) pathways hold promise for halting or reversing pancreatic fibrosis.
Enzyme Replacement Therapy (PERT): For patients with exocrine pancreatic insufficiency, administering exogenous pancreatic enzymes with meals reduces postprandial pain and malnutrition. By feeding the feedback loop that signals the pancreas that digestion is taken care of, PERT can indirectly reduce excessive pancreatic stimulation.
Part 5: Lifestyle Modifications and Long-Term Pancreatic Health
Sustained reduction of pancreatic inflammation requires permanent adjustments to lifestyle habits that directly injure or stress the organ. Addressing the root environmental causes is non-negotiable for long-term remission and preventing recurrent flares.
The Imperative of Smoking Cessation
Tobacco smoking is now recognized as an independent, major risk factor for both the initiation and progression of chronic pancreatitis.
Synergistic Toxicity: Smoking accelerates pancreatic calcification, worsens fibrosis, and significantly increases the risk of pancreatic cancer in patients with chronic inflammation.
Cellular Damage: Toxic compounds found in cigarette smoke induce oxidative stress directly within the acinar and ductal cells. Comprehensive smoking cessation programs are therefore an essential component of any anti-inflammation protocol.
Complete Alcohol Abstinence
Alcohol consumption is a leading global cause of both acute and chronic pancreatitis. Even modest amounts of alcohol can sensitize pancreatic acinar cells to injury, lower the threshold for premature enzyme activation, and increase intraductal protein precipitation.
Biological Mechanism: Ethanol metabolism within the pancreas generates toxic non-oxidative and oxidative metabolites that disrupt calcium homeostasis and trigger intracellular stress pathways.
Recovery Outlook: Complete and permanent cessation of alcohol is the single most effective intervention to halt disease progression, reduce pain frequency, and prevent hospital readmissions.
Part 6: Integrative Approaches and Future Horizons
As our understanding of the gut-pancreas axis deepens, integrative medicine and novel biotechnologies are paving the way for personalized management plans.
The Gut Microbiome and Intestinal Permeability
Emerging data suggest that alterations in the gut microbiota (dysbiosis) and increased intestinal permeability play a critical role in severe acute pancreatitis. When the gut barrier is compromised, bacterial translocation can infect pancreatic necrotic tissue, turning sterile inflammation into infected necrosis.
Probiotics and Prebiotics: Restoring a healthy microbial balance helps maintain mucosal integrity and modulates systemic immune responses. However, specific strains and timing must be carefully managed, especially in severe acute cases where enteral nutrition is preferred over broad probiotic supplementation.
Fecal Microbiota Transplantation (FMT): Investigational studies are exploring whether reshaping the microbiome via FMT can reduce systemic inflammation and improve clinical outcomes in refractory gastrointestinal disorders.
Conclusion: A Multidisciplinary Paradigm
Bringing down pancreas inflammation is rarely achieved through a single intervention. It demands a sophisticated, multi-pronged strategy that combines:
Immediate physiological rest via tailored low-fat nutritional therapy,
Targeted pharmacological and antioxidant support to quench oxidative stress and inhibit fibrogenesis,
Rigorous elimination of triggers such as alcohol and tobacco, and
Ongoing monitoring by a multidisciplinary team of gastroenterologists, dietitians, and pain specialists.
By addressing the inflammatory cascade at every level—from molecular pathways to daily lifestyle choices—patients can protect remaining pancreatic function, alleviate chronic pain, and reclaim their long-term health and vitality.
What specific aspect of pancreatic health or dietary recovery would you like to explore next?