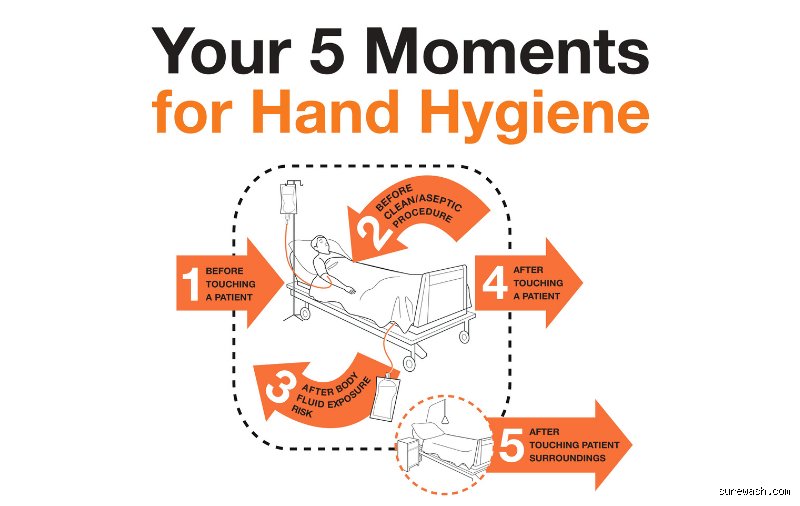
Introduction and fundamental principles
This conceptual model bridges the gap between theoretical knowledge and practical execution, offering healthcare personnel a clear, intuitive mental map of when hand hygiene must be performed during patient care delivery. Rather than relying on arbitrary intervals or subjective discretion, the five moments anchor hand hygiene directly to the workflow of clinical interaction. Understanding the physiological, epidemiological, and microbiological rationale behind each of these five points is essential for mitigating healthcare-associated infections (HAIs), protecting vulnerable patient populations, and upholding institutional patient safety standards.
1. Before touching a patient
Microbiological Rationale
The human skin is naturally colonized by resident microflora, which generally reside in the deeper layers of the epidermis and are resistant to mechanical removal. However, the hands frequently acquire transient flora, pathogenic organisms picked up from contaminated environmental surfaces, medical equipment, or direct contact with other individuals. When a healthcare worker approaches a patient without performing hand hygiene first, these transient microorganisms are directly transferred onto the patient's intact skin or mucous membranes.
For immunocompromised, surgical, or critically ill patients, introducing exogenous transient flora can precipitate severe opportunistic infections, surgical site contaminations, and systemic sepsis. Performing hand hygiene before touching a patient acts as a protective shield, ensuring that the clinician's hands are free of foreign pathogens prior to any physical interaction.
Clinical context and execution
This moment applies to any direct physical contact that does not break the skin barrier, as well as routine social or supportive touches. Examples include:
Assisting a patient to sit up in bed or adjust their position.
Conducting