Understanding Prostatectomy: Unpacking the Realities Behind the Statistics
When individuals or their loved ones are faced with a prostate cancer diagnosis, the terminology can quickly become overwhelming. Among the most frequent surgical interventions recommended by urological oncologists is a prostatectomy—the surgical removal of all or part of the prostate gland. While it is standard medical practice, people don't think about this enough regarding what "success" actually means over the long term.
Success is rarely a simple binary outcome of cured versus not cured. Instead, it encompasses a delicate, highly individual matrix of cancer eradication, urinary continence preservation, and sexual function retention. Navigating these overlapping dimensions requires a deep dive into data, clinical variables, and the lived experiences of patients.
Defining "Success" in Prostate Cancer Surgery
To evaluate the success rate of a prostatectomy accurately, we must first deconstruct the term itself. In oncology, success traditionally points to cancer control—specifically, achieving negative surgical margins and maintaining undetectable levels of prostate-specific antigen (PSA) post-surgery. However, patients experience success much more holistically. A cancer-free status paired with permanent urinary incontinence or severe erectile dysfunction paints a very different picture of recovery than a complete return to baseline quality of life.
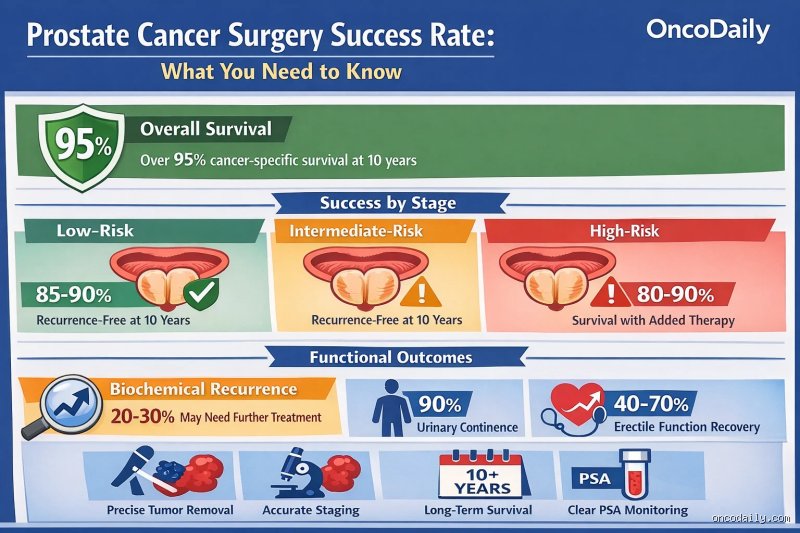
Statistically speaking, radical prostatectomy boasts exceptionally high overall cancer-specific survival rates, particularly when the disease is caught in its localized stages. For localized prostate cancer, 5-year and 10-year survival rates often exceed 95%. Yet, looking only at survival masks the nuances of biochemical recurrence (BCR)—a rising PSA level after surgery that indicates remaining or returning prostate cancer cells. Depending on pre-surgical risk factors like the Gleason score, clinical stage, and initial PSA levels, biochemical recurrence-free survival rates at 5 to 10 years can range anywhere from 70% to upwards of 90%.
This wide statistical variance highlights why personalized risk stratification is vital. Honestly, it's unclear to many patients prior to diagnosis just how much their individual tumor biology will dictate their post-operative journey, as two people with the same diagnosis can undergo identical surgeries and encounter entirely different outcomes.
The Anatomy of Risk: Pre-Surgical Factors That Drive Outcomes
Not all prostate cancers behave aggressively, and not all prostatectomies carry the same probability of a seamless recovery. Urologists rely heavily on risk classification models—such as the D'Amico risk classification—to categorize patients into low, intermediate, or high-risk groups.
Low-Risk Disease: Characterized by a low Gleason score (6 or lower), a low initial PSA (under 10 ng/mL), and a localized clinical stage (T1c or T2a). Patients in this category generally experience the highest rates of long-term biochemical control and cancer-specific survival.
Intermediate-Risk Disease: Involves a Gleason score of 7, a PSA between 10 and 20 ng/mL, or a slightly more advanced clinical stage. Outcomes remain generally favorable, though the probability of needing secondary treatments like radiation or hormone therapy down the line increases.
High-Risk Disease: Features a Gleason score of 8 to 10, a PSA exceeding 20 ng/mL, or more extensive tumor involvement (T2c or higher). Here, we're far from it when talking about guaranteed single-treatment cures; high-risk cases frequently demand a multimodal treatment approach where surgery is just the opening chapter.
Understanding these tiers shifts expectations. When a patient moves from a low-risk profile to a high-risk profile, the definition of surgical success evolves from a standalone cure to an essential cornerstone of a broader, comprehensive oncology strategy.
Surgical Techniques: Open, Laparoscopic, and Robotic-Assisted Approaches
The evolution of surgical technology has profoundly transformed prostatectomy outcomes over the past three decades. Historically, open retropubic or perineal prostatectomies were the default. Today, minimally invasive techniques—specifically robotic-assisted laparoscopic radical prostatectomy (RALRP)—have become the dominant standard of care in many developed medical centers.
The technological leap provided by robotic platforms offers surgeons high-definition 3D visualization and wristed instruments that mimic human movements with micro-scaling and tremor filtration. This precision allows for meticulous dissection around the delicate neurovascular bundles responsible for erectile function, as well as the intricate urinary sphincter mechanisms.
When comparing open surgery to robotic-assisted procedures, clinical data consistently demonstrates distinct advantages for the minimally invasive approach in terms of intraoperative metrics:
Blood Loss: Robotic procedures typically result in significantly lower estimated blood loss, sharply reducing transfusion rates.
Hospital Stay: Patients undergoing robotic-assisted surgery generally experience shorter hospital admissions—often returning home within 24 to 48 hours.
Recovery Timeline: Return to normal baseline activities is frequently accelerated, though long-term functional recovery timelines can still mirror those of open surgery depending on surgeon experience and patient anatomy.
Despite these technological marvels, the skill of the operating surgeon remains the single most critical determinant of success. The learning curve for robotic prostatectomy is steep, and high-volume surgeons—those who perform hundreds of these procedures annually—consistently report superior oncological and functional outcomes compared to low-volume practitioners.
Functional Outcomes: Continence and Quality of Life
Beyond eradicating malignant cells, the preservation of urinary continence stands as a paramount goal for anyone undergoing a prostatectomy. The urinary sphincter sits immediately adjacent to the apex of the prostate gland, making it vulnerable during resection and reconstruction.
Continence recovery rates vary widely based on age, baseline bladder function, and surgical technique, but modern nerve-sparing and structure-preserving approaches yield impressive numbers. Within 12 months post-surgery, approximately 85% to 95% of patients achieve complete urinary control, meaning they require zero pads or manage with at most a light safety liner for occasional stress incontinence. However, the immediate post-operative period can be challenging. Many individuals experience varying degrees of leakage when coughing, sneezing, or lifting heavy objects during the first few weeks or months.
Pelvic floor muscle training—commonly known as Kegel exercises—plays an indispensable role in accelerating this recovery. Engaging physical therapists specializing in men's pelvic health before and after surgery that changes everything for patients, shortening the timeline of urinary leakage and boosting overall confidence during the rehabilitation phase.
Navigating Sexual Health Post-Surgery
Sexual function recovery is arguably the most emotionally charged aspect of prostatectomy success. The neurovascular bundles—tiny networks of nerves and blood vessels that control erections—run along the left and right sides of the prostate. Even with advanced nerve-sparing techniques, these delicate structures inevitably experience trauma, stretching, or temporary stunning during the excision of the gland.
The probability of regaining natural erectile function depends heavily on three core variables:
Pre-operative Function: Men who enjoyed robust, reliable erections prior to surgery have a significantly higher probability of recovering them afterward.
Age: Younger patients (under 60) generally possess greater nerve recovery potential and resilience compared to older cohorts.
Surgical Extent: Unilateral (one side) or bilateral (both sides) nerve-sparing procedures preserve structural pathways, whereas non-nerve-sparing procedures (dictated by the tumor's proximity to the edge of the prostate) render natural erections unlikely.
Recovery of erectile function is not an overnight event; it is a biological marathon that can span anywhere from 12 to 36 months. Early penile rehabilitation protocols, which may include the use of phosphodiesterase type 5 (PDE5) inhibitors (such as sildenafil or tadalafil) and vacuum erection devices, are frequently prescribed to promote blood flow, preserve smooth muscle elasticity, and encourage nerve regeneration.
Long-Term Survival and Oncological Outcomes
While biochemical recurrence (BCR) indicates that microscopic prostate cancer cells may still be present, it does not automatically mean that a patient will experience clinical metastasis or die from the disease.
Population-based data indicates that the estimated overall survival rate at 5 years is approximately 96%, extending to roughly 85% at 10 years.
Key Risk Factors Influencing Success Rates
A patient's individual success rate cannot be generalized into a single statistic because it is heavily dictated by pre-operative characteristics and post-operative pathology reports. The primary clinical variables influencing long-term cancer control include:
Pathological Stage (T-Stage): Tumors confined entirely within the prostate (pT2) boast significantly higher long-term cure rates—often exceeding 85% to 90% freedom from recurrence at 5 years.
When cancer extends outside the capsule (pT3a or pT3b), the likelihood of microscopic disease remaining behind increases, lowering biochemical recurrence-free survival. Gleason Score / Grade Group: The aggressiveness of the cellular architecture plays a vital role. Low-grade cancers (Gleason 6 or Grade Group 1) carry a remarkably favorable prognosis, whereas high-grade patterns (Gleason 8–10 or Grade Groups 4–5) carry a substantially elevated risk of aggressive recurrence.
Surgical Margins: A "negative margin" means pathologists found a border of healthy tissue surrounding the removed tumor, lowering recurrence risk. A "positive margin" indicates cancer cells extended to the outer edge of the specimen, which increases the statistical chance of residual local disease.
Pre-operative PSA Velocity: Higher baseline PSA levels and rapid doubling times prior to surgery correlate with more advanced disease states.
Managing Recurrence and Looking Forward
For patients who do experience a rising PSA post-surgery, advanced diagnostic imaging—such as PSMA PET scans—can pinpoint microscopic or localized recurrence with unprecedented accuracy. Therapeutic options like salvage radiation therapy or targeted hormone modulation can successfully re-establish control over the disease.
This video provides an expert clinical overview of how urologists evaluate and manage biochemical relapse following a radical prostatectomy.