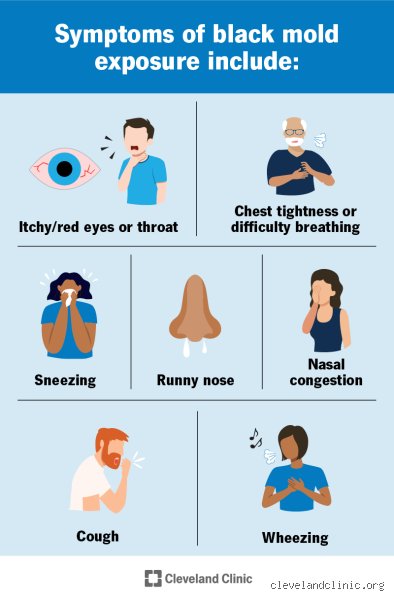
Because every breath draws thousands of these microscopic particles deep into the respiratory tract, the lungs are often the primary organs to experience the impact. Determining whether mold is actively affecting your respiratory health can be surprisingly complex. The symptoms frequently mimic common ailments such as seasonal allergies, the common cold, or routine fatigue. This comprehensive guide explores the physiological mechanisms of mold exposure, details the specific clinical signs that indicate your lungs are reacting, examines high-risk vulnerabilities, and outlines actionable diagnostic steps to safeguard your respiratory well-being.
Understanding the invisible threat: How mold interacts with the respiratory tract
To understand how mold affects lung function, it is helpful to look at what happens the moment you inhale contaminated air. Mold reproduces by releasing microscopic spores into the atmosphere. Because these spores are exceptionally lightweight and resilient, they easily remain airborne and travel deep into the respiratory system when disturbed.
In a healthy individual with a robust immune system, occasional exposure to outdoor mold spores is generally handled seamlessly by the body's natural defense mechanisms. The nasal passages, trachea, and upper airways capture larger particles, while specialized immune cells in the lungs—known as alveolar macrophages—engulf and destroy foreign debris.
However, indoor environments with chronic water damage present a different scenario. Continuous exposure to high concentrations of indoor mold alters this dynamic. When airborne spores, allergenic proteins, and mycotoxins bypass upper airway filters and reach the delicate lower airways and alveoli, several physiological reactions can occur:
Allergic Sensitization and Inflammation: For many people, mold proteins act as allergens. The immune system mistakenly identifies these harmless spores as dangerous invaders and produces Immunoglobulin E (IgE) antibodies. Upon re-exposure, these antibodies trigger mast cells to release histamine and other inflammatory chemicals, causing swelling, mucus hypersecretion, and airway constriction.
Direct Irritation: Even without a classic allergic response, the chemical byproducts and spores of certain molds can irritate the sensitive epithelial lining of the bronchi and bronchioles, leading to persistent coughing and throat discomfort.
Hypersensitivity Reactions: In susceptible individuals, repeated inhalation of specific organic dusts and molds can trigger an immune-mediated condition known as hypersensitivity pneumonitis, where the alveoli themselves become severely inflamed and scarred over time.
Fungal Colonization or Infection: Though less common in healthy people, individuals with pre-existing lung cavities or compromised immune systems can experience direct fungal growth within the respiratory tissues, leading to clinical conditions such as aspergillosis.
Recognizing the early warning signs: Respiratory symptoms of mold exposure
The manifestation of mold-related lung issues spans a broad spectrum, ranging from mild, transient upper respiratory irritation to severe, chronic pulmonary disease. Because symptoms often overlap with other environmental triggers, identifying the pattern of your discomfort is critical.
1. Persistent, unexplained coughing
A chronic, lingering cough is frequently one of the earliest indicators that your respiratory system is reacting to an airborne irritant. Unlike the sharp, productive cough associated with acute bacterial bronchitis or a viral chest cold, a mold-induced cough is often dry, hacking, and persistent. It may worsen during specific times of the day, such as first thing in the morning after spending hours sleeping in a mold-affected bedroom, or after spending extended periods in a damp basement or workspace. Over time, irritation of the bronchial tubes can cause the airways to produce excess mucus, turning a dry cough into a productive one marked by clear or whitish phlegm.
2. Wheezing and chest tightness
If you notice a distinct whistling sound (wheezing) when you exhale, or if your chest feels heavy and constricted, your lower airways may be narrowing due to inflammation or bronchospasm. Mold exposure is a well-documented trigger for bronchial hyper-reactivity. When mold spores irritate the smooth muscles surrounding the bronchial tubes, these muscles can contract abruptly, restricting airflow and making deep breaths feel difficult or labored.
3. Worsening Asthma and loss of baseline control
For individuals who already manage asthma, indoor mold acts as a powerful and pervasive trigger. If you find that your rescue inhaler (such as albuterol) is suddenly required with much greater frequency, or if your daily maintenance medications no longer keep your symptoms stable, environmental factors like hidden mold are often to blame. Asthma attacks brought on by mold exposure can range from moderate wheezing to severe, life-threatening exacerbations requiring emergency medical intervention.
4. Shortness of breath (dyspnea) with minimal exertion
Feelings of breathlessness that seem disproportionate to your physical activity level warrant close attention. If climbing a single flight of stairs or walking short distances leaves you winded in a way that is unusual for your fitness level, it suggests that gas exchange within your lung alveoli may be impaired. This symptom can point toward chronic inflammation or early-stage hypersensitivity pneumonitis.
Differentiating transient Irritation from Chronic conditions
A vital step in determining if mold is affecting your lungs is evaluating the context and timeline of your symptoms. Environmental physicians and allergists frequently look for specific behavioral and geographical patterns:
The "Away from Home" Test: One of the most telling clues of mold-induced respiratory distress is symptom variability based on location. Do your cough, congestion, and chest tightness improve significantly when you leave your home for a weekend trip, a vacation, or a prolonged workday elsewhere, only to return and flare up within hours of coming back indoors? This classic pattern strongly implicates your indoor environment.
Seasonal vs. Year-Round Persistence: While outdoor mold counts peak during damp autumn months or spring thaws, indoor mold thrives 365 days a year due to plumbing leaks, roof defects, or high relative humidity. If your "allergies" refuse to subside during the winter months when outdoor pollens are dormant, indoor fungal proliferation is a prime suspect.
High-Risk groups: Who is most vulnerable?
While anyone can experience irritation from heavy mold exposure, certain populations face a significantly higher risk of developing severe or complicated pulmonary reactions:
Asthmatics and Individuals with Chronic Lung Disease: People with pre-existing conditions like Chronic Obstructive Pulmonary Disease (COPD), bronchiectasis, or cystic fibrosis possess hyper-reactive or structurally altered airways. For these individuals, even minor exposure to mold spores can provoke severe bronchoconstriction and rapid clinical decline.
Immunocompromised Individuals: Patients undergoing chemotherapy, organ transplant recipients, individuals living with advanced HIV, or those on long-term systemic corticosteroid therapy have diminished immune defenses. They are uniquely susceptible to invasive fungal infections where molds actively colonize lung tissue.
Occupational Workers in Damp Environments: Agricultural workers, greenhouse operators, demolition crews, and building maintenance personnel frequently encounter dense concentrations of organic dusts and molds, placing them at high risk for occupational lung diseases such as "farmer's lung" or specific forms of hypersensitivity pneumonitis.
Comprehensive diagnostics and clinical evaluation
When a patient presents with persistent respiratory complaints suspected to stem from environmental fungal exposure, clinicians rely on a structured diagnostic framework. Because symptoms like coughing, wheezing, and shortness of breath overlap significantly with common allergies, asthma exacerbations, and viral bronchitis, isolating mold as the primary driver requires careful investigation.
The diagnostic process typically begins with a detailed environmental and occupational history. A physician will ask specific questions regarding:
The presence of visible water damage, leaks, or musty odors in the home, workplace, or school.
The temporal pattern of symptoms, specifically whether respiratory distress improves when the individual is away from the suspect environment for extended periods (such as during vacations or weekends).
Pre-existing respiratory vulnerabilities, including diagnosed asthma, chronic obstructive pulmonary disease (COPD), or immunocompromising conditions.
Following the clinical interview, objective testing may be employed to assess lung function and immune response:
Spirometry and Pulmonary Function Tests (PFTs): These tests measure airflow limitation, lung volume, and the rate at which air can be expelled from the lungs. In patients with mold-aggravated asthma or hypersensitivity pneumonitis, PFTs can quantify the degree of obstructive or restrictive impairment.
Allergy Testing: Skin prick tests or specific IgE blood tests (RAST) help determine if the patient has a measurable IgE-mediated immune sensitization to common indoor and outdoor molds (such as Alternaria, Cladosporium, Aspergillus, or Penicillium).
Imaging Studies: Chest radiography (X-rays) or high-resolution computed tomography (HRCT) scans of the chest are crucial when deep-lung involvement, such as hypersensitivity pneumonitis or pulmonary aspergillosis, is suspected. Imaging can reveal characteristic patterns such as interstitial infiltrates, nodules, or air-trapping.
Sputum Cultures and Specialized Blood Tests: In cases of suspected fungal infection or allergic bronchopulmonary aspergillosis (ABPA), analysis of sputum samples or serum precipitin (antibody) tests provide critical data to confirm the presence of specific fungal pathogens.
Management, remediation, and prevention strategies
Mitigating the health effects of mold requires a dual approach: addressing the medical symptoms within the body and eradicating the source of contamination in the environment. Treating the symptoms without resolving the underlying exposure often results in chronic, relapsing illness.
Medical Interventions
Depending on the specific diagnosis made by a healthcare professional, treatment plans may vary widely:
For Mold-Induced Allergies and Asthma: Management frequently includes intranasal corticosteroids, oral or topical antihistamines, and rescue or maintenance inhalers prescribed to control airway inflammation and bronchospasm.
For Hypersensitivity Pneumonitis: The cornerstone of treatment is strict avoidance of the offending antigen. In more severe or acute presentations, short courses of systemic corticosteroids may be prescribed by a pulmonologist to suppress the overactive immune response and prevent permanent lung scarring (fibrosis).
For Fungal Infections: Invasive or chronic pulmonary infections require targeted antifungal pharmacotherapy, which may range from oral azole medications to intravenous antifungals administered in clinical settings, depending on the pathogen and severity.
Environmental Remediation
Medical treatment cannot succeed if continuous exposure persists. Effective home and workplace mitigation involves:
Controlling Moisture: Maintaining indoor relative humidity below 50% using air conditioners and dehumidifiers. Promptly fixing plumbing leaks, roof leaks, and sealing foundation seepage.
Professional Abatement: Small patches of mold on hard surfaces can often be cleaned with appropriate detergent solutions, but extensive contamination, particularly involving porous materials like drywall, insulation, or carpeting, frequently necessitates professional remediation to prevent widespread spore dispersion during cleanup.
Improving Ventilation: Ensuring high-efficiency particulate air (HEPA) filtration in HVAC systems and properly venting moisture-generating appliances like clothes dryers and bathroom exhaust fans to the outdoors.
Conclusion
Recognizing whether mold is affecting your lungs requires careful observation of your symptoms, their timing, and your physical environment. While mild irritation and allergic rhinitis are common and manageable, deep-lung reactions like hypersensitivity pneumonitis and fungal infections represent serious medical concerns that demand professional evaluation. By combining prompt clinical diagnostics with rigorous environmental controls, individuals can safeguard their respiratory health and maintain a safe, breathable indoor environment.