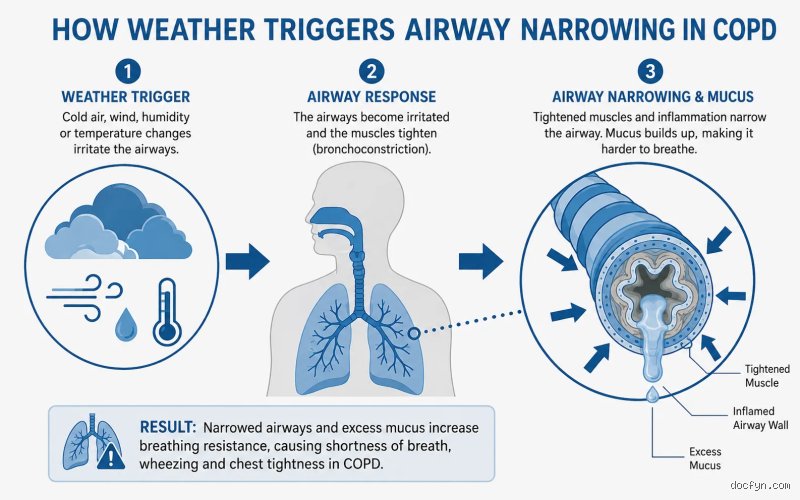
Understanding how moisture levels in the air interact with compromised airways requires a deep dive into respiratory physiology, fluid dynamics, and environmental science. Is humid air beneficial because it soothes dry tissues, or does it suffocate? Conversely, does dry air preserve breath, or does it trigger severe inflammation? This expert analysis explores the complex physiological relationship between humidity and COPD, unpacking the mechanisms that make changing weather patterns a daily challenge for pulmonary patients.
1. Defining the landscape: COPD and Environmental sensitivity
Chronic Obstructive Pulmonary Disease is an umbrella term encompassing progressive respiratory conditions characterized by long-term breathing difficulties and airflow limitation. Primarily driven by chronic bronchitis (inflammation and excessive mucus production in the bronchial tubes) and emphysema (destruction of the tiny air sacs, or alveoli, at the end of the airways), COPD fundamentally alters the mechanical efficiency of the human respiratory system.
In a healthy individual, the upper respiratory tract acts as an extraordinary conditioning chamber. As air is inhaled through the nose and mouth, it is rapidly warmed to body temperature and humidified to nearly one hundred percent saturation before it ever reaches the delicate lung tissue. This conditioning process protects the lower airways from thermal shock and desiccation.
However, in a patient with COPD, this intricate conditioning machinery is compromised. The structural integrity of the bronchial walls is degraded, cilia (the microscopic hair-like structures responsible for sweeping away mucus and debris) are paralyzed or destroyed, and the elastic recoil of the lung parenchyma is severely diminished. Consequently, when ambient air deviates significantly from optimal moisture ranges, the respiratory system of a COPD patient struggles to compensate, leading to acute exacerbations, increased coughing, wheezing, and debilitating shortness of breath (dyspnea).
2. The Dual-Edged sword: High Humidity vs. Low Humidity
To comprehend how humidity affects COPD, one must recognize that both extremes, excessive moisture (high humidity) and extreme dryness (low humidity), pose distinct physiological hazards. However, they do so through entirely different mechanisms.
High Humidity: The weight and Density of muggy Air
When relative humidity spikes, typically on hot, muggy summer days or in tropical climates, the air becomes saturated with water vapor. For a healthy person, this might feel slightly uncomfortable or sticky. For a person with COPD, high humidity can feel like breathing through a heavy, damp blanket.
Air Density and Gas Diffusion: Humid air is actually less dense than dry air at the same temperature because water vapor molecules displace heavier nitrogen and oxygen molecules. While this sounds counterintuitive, the primary burden of high humidity on COPD patients is not a lack of oxygen, but rather the viscosity and thermal load of the air. Muggy air is heavier to move, requiring greater muscular effort from the diaphragm and intercostal muscles to draw breath.
Pollutant Trapping: High humidity frequently correlates with stagnant air masses that trap particulate matter, smog, ozone, and allergens close to the ground. In urban environments, humid days often double as high-pollution days. For COPD lungs, which are hyper-reactive to airborne irritants, this chemical cocktail triggers immediate bronchospasm (the sudden tightening of muscles surrounding the airways).
Evaporative Cooling Failure: High humidity inhibits the body's natural cooling mechanism (sweat evaporation). When core body temperature rises, the cardiovascular and respiratory systems must work harder to dissipate heat, leading to hyperventilation and increased oxygen demand in a body whose lungs cannot efficiently supply it.
Low Humidity: The arid threat of winter and Air conditioning
At the opposite end of the spectrum, extremely low humidity, common during freezing winter months when cold air holds very little moisture, or inside buildings heavily conditioned by indoor heating and air conditioning, presents an equally dangerous set of challenges.
Desiccation of Mucosal Linings: Dry air rapidly strips moisture from the respiratory epithelium. In healthy lungs, a thin layer of mucus traps pathogens and foreign particles, which the cilia continuously move upward. When humidity plummets, this mucus layer dries out, becoming thick, viscous, and difficult to mobilize. This stagnation increases the risk of bacterial and viral colonizations, setting the stage for severe respiratory infections.
Airway Irritation and Micro-Fissures: Inhaling arid air causes microscopic drying and irritation along the bronchial tree. The body responds to this desiccation with an inflammatory cascade, releasing histamine and cytokines that cause the airways to swell and narrow further, a catastrophic event for an already narrowed airway lumen.
Triggering Reflex Coughing: Dry air acts as a mechanical and chemical irritant to the nerve endings embedded in the trachea and bronchi. This triggers persistent, hacking coughs that exhaust the patient, consume precious oxygen reserves, and can further damage fragile emphysematous tissue.
3. The aerodynamics of Airway resistance in High moisture
To fully appreciate the physiological burden of high humidity, one must examine the fluid dynamics inside the human bronchial tree. In COPD, airflow limitation is largely determined by airway resistance, which is mathematically governed by Poiseuille’s Law. Resistance is inversely proportional to the fourth power of the airway radius; even a microscopic decrease in radius results in an exponential spike in the effort required to move air.
When a COPD patient inhales hot, humid air, water vapor condenses within the cooling gradient of the upper and lower airways. This condensation adds microscopic droplets of water to an already over-abundant pool of thick, tenacious mucus characteristic of chronic bronchitis. The surface tension of this fluid layer increases resistance, making exhalation, already an active, labored process for emphysema patients due to air trapping, even more difficult.
High ambient humidity frequently coexists with elevated ambient temperatures. Heat stress forces the body to redirect blood flow toward the skin to cool down, which simultaneously increases cardiac output and respiratory rate. For a patient whose cardiopulmonary reserve is already diminished, this metabolic feedback loop quickly induces severe respiratory distress.
4. Meteorological factors and symptom variability
Humidity rarely acts in isolation. Meteorological systems are complex matrices involving barometric pressure, temperature, wind velocity, and air quality indices.
Barometric pressure (atmospheric pressure) often drops sharply ahead of storms or weather fronts. A drop in barometric pressure causes gases trapped within body cavities and lung tissues to expand slightly. In individuals with damaged, hyper-compliant lung tissue (such as those with severe emphysema), this expansion can exert physical pressure on the thoracic cavity, exacerbating feelings of tightness and breathlessness. When high humidity accompanies a falling barometric pressure, such as right before a summer thunderstorm, COPD patients frequently report feeling "smothered" or heavy-chested.
Looking ahead: Managing Environmental Triggers
As this analysis demonstrates, atmospheric moisture is a critical determinant of respiratory stability for individuals managing Chronic Obstructive Pulmonary Disease. Navigating these fluctuations requires strategic environmental control, such as monitoring dew points, utilizing indoor dehumidifiers during humid summer months, and employing cool-mist humidifiers during arid winter seasons while strictly maintaining hygiene to prevent mold proliferation.
(This concludes Part 1 of our expert analysis on humidity and COPD. In Part 2, we will explore advanced clinical mitigation strategies, personalized indoor environmental controls, and evidence-based pulmonary rehabilitation techniques designed to buffer patients against volatile meteorological shifts.)
Clinical management and Environmental control strategies
Navigating High Humidity challenges
When ambient relative humidity climbs past the 60% threshold, individuals managing chronic obstructive pulmonary disease (COPD) often experience an immediate surge in respiratory distress. From a physiological standpoint, humid air possesses higher vapor density, meaning water molecules displace other atmospheric gases, slightly reducing the partial pressure of breathable oxygen.
While this variation has negligible impact on healthy pulmonary systems, it poses an immediate challenge for compromised lung architecture characterized by air trapping, hyperinflation, and structural degradation.
To mitigate the adverse effects of high humidity, clinical guidelines emphasize robust environmental control:
Targeted Dehumidification: Deploying high-efficiency compressor dehumidifiers in primary living spaces, especially bedrooms and basements, maintains indoor relative humidity within the optimal 30% to 50% window.
Minimizing Biological Triggers: Controlling moisture effectively halts the rapid proliferation of indoor mold colonies and house dust mites, two prevalent biological allergens capable of instigating severe acute bronchospasm and prolonged exacerbations.
Inhaler Maintenance: Patients must store moisture-sensitive dry-powder inhalers (DPIs) in dry environments, as ambient moisture can cause internal medication clumping, impairing the delivery of critical bronchodilators to the lower airways.
Mitigating the risks of Low Humidity and arid climates
Conversely, plunging humidity levels, frequently experienced during deep winter months or in arid geographical regions, present an entirely distinct set of physiological hurdles for the respiratory epithelium.
Extremely dry air strips moisture from the mucous membranes lining the upper and lower respiratory tracts at an accelerated rate. This rapid evaporation desiccates the protective mucus blanket, crippling the mucociliary escalator's capacity to sweep away particulate matter, pollutants, and bacterial pathogens.
Cold, dry air frequently provokes reflex bronchospasm, causing the smooth muscles surrounding the bronchial tubes to constrict sharply. This constriction manifests as sudden wheezing, persistent coughing spells, and a tightening sensation across the chest wall.
Proactive Air Moisturization: Utilizing clean, regularly sanitized cool-mist humidifiers indoors helps restore critical moisture balance, preventing mucosal cracking and secondary respiratory infections.
Thermodynamic Filtering via Scarves: When venturing into cold, dry outdoor environments, wearing a loose scarf or thermal mask over the nose and mouth pre-warms and pre-humidifies inspired air before it reaches vulnerable bronchial structures.
Actionable Environmental mitigation framework
To maintain stability across fluctuating seasonal patterns, patients and caregivers should implement a structured daily monitoring routine. The matrix below outlines proactive steps based on atmospheric conditions:
| Atmospheric Condition | Primary Pathophysiological Risk | Recommended Environmental Intervention | Daily Lifestyle Adjustment |
|---|---|---|---|
| High Humidity (>60%) | Increased air density, impaired mucociliary clearance, mold/dust mite proliferation | Run air conditioning and dedicated electric dehumidifiers; track indoor hygrometer readings. | Limit strenuous outdoor activities during peak heat-index windows; pace daily physical chores. |
| Low Humidity (<30%) | Mucosal desiccation, impaired cilia function, reflex bronchospasm | Operate clean-water humidifiers; monitor and maintain indoor baseline moisture above 30%. | Wear a thermal facial covering outdoors to warm and condition incoming air. |
| Optimal Zone (30%–50%) | Baseline stability; minimal environmental provocation | Maintain standard HVAC filters; perform routine system maintenance. | Engage in prescribed pulmonary rehabilitation exercises safely. |
Conclusion and collaborative care planning
Humidity acts as a potent environmental modifier capable of shifting a stable COPD patient into acute respiratory distress. Because individual thresholds vary significantly, some patients react adversely to oppressive tropical moisture, while others experience severe distress during crisp, arid winter days, personalized awareness remains paramount.
Patients should closely track local weather metrics, including dew points and relative humidity indices, integrating these insights into their personalized COPD action plans. By pairing proactive indoor climate control with consistent communication alongside pulmonologists and respiratory therapists, individuals can successfully minimize weather-induced flare-ups, preserve lung function, and maintain an active, high quality of life.