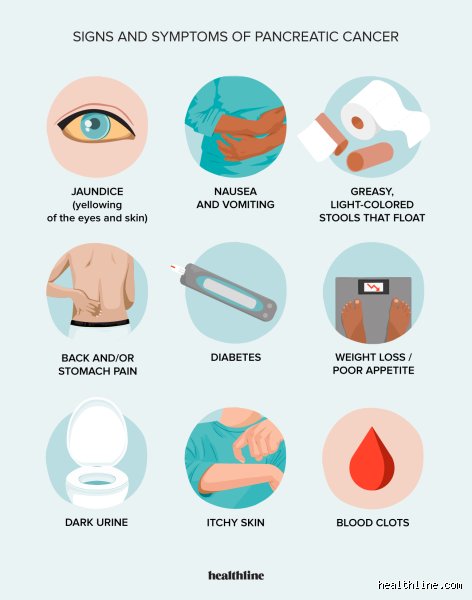
The Clinical enigma of pancreatic carcinoma
In its earliest, most localized, and surgically resectable stages, pancreatic cancer is almost universally asymptomatic. The pancreas is a deeply retroperitoneal organ, nestled securely in the upper posterior abdomen behind the stomach, duodenum, and transverse colon, enveloped by a dense network of major vascular structures and nerve plexuses. Because of this secluded anatomical sanctuary, neoplastic growths can expand, infiltrate local tissue planes, and even micrometastasize to regional lymph nodes and the hepatic parenchyma long before they trigger overt clinical manifestations.
Consequently, the vast majority of patients, exceeding 80% at the time of initial diagnosis, present with locally advanced or metastatic disease, precluding curative surgical resection, which remains the single most effective modality for long-term survival. Understanding, identifying, and acting upon the subtle, often non-specific early warning signs of pancreatic cancer is therefore an urgent clinical imperative. Primary care providers, specialists, and patients alike must cultivate a high index of suspicion, shifting the diagnostic paradigm away from late-stage presentation toward early recognition of the body's subtle distress signals.
1. Anatomical and pathophysiological determinants of Early symptoms
To comprehend why pancreatic cancer presents with the specific warning signs it does, one must first examine the dual functional architecture of the pancreas and its precise topographical relations within the abdominal cavity. The organ is functionally divided into two distinct components:
The Exocrine Pancreas: Comprising acinar and ductal cells that synthesize and secrete digestive enzymes (such as amylase, lipase, and proteolytic precursors) into the pancreatic ductal system, which empties into the duodenum.
The Endocrine Pancreas: Comprising the Islets of Langerhans, which secrete vital regulatory hormones directly into the bloodstream, most notably insulin, glucagon, and somatostatin.
Topographically, the pancreas is partitioned into the head, the neck, the body, and the tail. The anatomical location of the tumor dictates the chronology and constellation of symptoms a patient experiences:
| Anatomical Region | Predominant Tumor Location | Primary Clinical Consequences & Early Manifestations |
|---|---|---|
| Head of the Pancreas | ~65% to 70% of cases | Compression of the common bile duct; early painless or painful obstructive jaundice, dark urine, pale stools, and pruritus. |
| Body and Tail of the Pancreas | ~20% to 25% of cases | Delayed presentation; late-onset visceral pain radiating to the back due to celiac plexus infiltration, profound weight loss, and constitutional fatigue. |
| Diffusely Infiltrating | ~10% of cases | Mixed exocrine and endocrine failure, rapid-onset secondary diabetes mellitus, and systemic cachexia. |
Because the pancreas lacks a distinct capsule, malignant cells encounter minimal anatomical resistance as they extend outward. They readily invade perineural spaces (perineural invasion is a hallmark of PDAC) and surround major blood vessels, including the superior mesenteric artery, celiac axis, and portal vein. It is this aggressive neurotropic and vascular invasion that generates the classic, hallmark symptom clusters long before structural organ failure occurs.
2. Visceral abdominal pain and posterior back radiation
One of the most frequent, yet frequently misattributed, early warning signs of pancreatic cancer is persistent or intermittent abdominal discomfort that radiates through to the back. This pain pattern is rarely a sharp, superficial somatic pain; instead, it is typically described as a deep, gnawing, dull ache or a visceral "belt-like" or "band-like" sensation wrapping around the upper abdomen and mid-back.
The neurological mechanism behind the pain
The underlying pathophysiology of this specific pain involves the invasion of the rich neural networks surrounding the superior mesenteric artery and the celiac plexus. As tumor cells track along the nerve sheaths, a phenomenon known as perineural invasion, they chronically stimulate visceral sensory afferent fibers.
Localization: Patients typically localize the initial discomfort to the epigastrium (the upper central abdomen).
Progression: Over weeks to months, as the malignancy extends posteriorly toward the retroperitoneum and encroaches upon the retroperitoneal nerve plexuses (particularly the celiac ganglion), the pain shifts into a relentless, deep-seated backache.
Positional Modulation: Patients often discover that the pain is modulated by posture. It frequently worsens when lying supine, as gravity compresses the retroperitoneal structures against the vertebral column, and it may transiently ease when the patient leans forward or assumes a fetal position, which widens the retroperitoneal space and relieves tension on the celiac plexus.
Unfortunately, because upper abdominal discomfort, dyspepsia, and back strain are ubiquitous complaints in the general population, frequently attributed to peptic ulcer disease, gastroesophageal reflux disease (GERD), musculoskeletal strain, or irritable bowel syndrome, patients and clinicians alike often dismiss these symptoms initially. A critical red flag is pain that is progressively worsening, unresponsive to standard anti-ulcer medications or analgesics, and accompanied by unexplained constitutional decline.
3. Obstructive jaundice and associated dermatological and excretory markers
When a malignant neoplasm originates in the head of the pancreas, even a relatively small tumor mass can exert direct mechanical pressure on or completely obstruct the extrahepatic common bile duct as it traverses the pancreatic head on its journey to the duodenum. This biliary obstruction prevents the normal excretion of conjugated bilirubin into the gastrointestinal tract, leading to a pathological backup of bile pigments into the systemic circulation and tissues. This gives rise to obstructive jaundice.
Clinical triad of biliary obstruction
Jaundice is often one of the most alarming and unambiguous visual warning signs of pancreatic cancer. Its presentation is accompanied by a reliable triad of excretory and dermatological shifts:
Icterus and Scleral Icterus: The initial manifestation is typically a subtle yellow discoloration of the bulbar conjunctiva (the whites of the eyes), which becomes apparent when serum bilirubin exceeds roughly 2 to 3 mg/dL. As bilirubin accumulates further, the skin assumes a distinct yellow-to-bronze hue.
Choluria (Dark Urine): Because conjugated bilirubin is water-soluble, excess circulating levels are filtered by the renal glomeruli and excreted in the urine, turning it a characteristic deep amber, brown, or tea-like color long before skin yellowing becomes severe.
Acholic Stools (Pale/Clay-Colored Feces): With the biliary tract obstructed, stercobilin (the breakdown product of bilirubin that gives stool its normal brown color) fails to reach the intestinal lumen. Consequently, bowel movements become abnormally pale, gray, or clay-colored, and frequently appear greasy or foul-smelling (steatorrhea) due to unabsorbed dietary fats.
Intractable Pruritus (Itching)
A frequently under-recognized warning sign associated with obstructive jaundice is generalized, severe pruritus (itchiness). The systemic accumulation of bile salts in the dermal tissues irritates cutaneous sensory nerve endings. Patients often describe an intense, maddening itch all over their body, sometimes seeking medical evaluation for what they initially suspect is a severe dermatological allergy or eczema, only to discover that the root cause is biliary stasis driven by an underlying pancreatic head mass.
Unlike gallstone-induced obstruction, which is classically intermittent and accompanied by acute right upper quadrant pain, fever, and leukocytosis (Charcot's triad of cholangitis), pancreatic tumor obstruction is often insidious, progressive, and initially painless ("painless jaundice"), making its early recognition paramount.
4. Metabolic deregulation: Unexplained weight loss and Cachexia
Unintentional, progressive weight loss is one of the most sensitive, albeit non-specific, systemic warning signs of pancreatic cancer, present in upwards of 75% to 85% of patients at the time of diagnosis. Unlike intentional weight loss achieved through caloric restriction or physical activity, pancreatic cancer-associated weight loss occurs rapidly and without any conscious alteration in diet or lifestyle.
Multi-Factorial etiology of malignant weight loss
The dramatic wasting seen in pancreatic cancer is driven by a complex interplay of mechanical, enzymatic, and biochemical mechanisms:
Exocrine Insufficiency and Malabsorption: As the tumor destroys normal pancreatic parenchyma and obstructs the main pancreatic duct (duct of Wirsung), the secretion of critical digestive enzymes, lipase, amylase, and proteases, into the small intestine plummets. Without adequate lipase, dietary fats cannot be hydrolyzed into absorbable free fatty acids and monoglycerides, resulting in severe fat malabsorption (steatorrhea), caloric wasting, and nutrient deficiencies.
Anorexia and Early Satiety: Tumors residing in the body or tail of the pancreas can physically compress the stomach or alter gastrointestinal motility. Patients frequently report a profound loss of appetite (anorexia) or a sensation of early satiety, feeling completely full after consuming only a few bites of food, which drastically suppresses caloric intake.
Tumor-Induced Systemic Cachexia: Beyond simple starvation, pancreatic cancer cells secrete pro-inflammatory cytokines and tumor-derived catabolic factors (such as tumor necrosis factor-alpha [TNF-α\alphaα], interleukin-6 [IL-6], and proteolysis-inducing factor). These circulating mediators fundamentally alter host intermediary metabolism, accelerating skeletal muscle proteolysis and driving uncoupling of oxidative phosphorylation in adipose tissue. This metabolic reprogramming results in cancer cachexia, a wasting syndrome characterized by the rapid loss of both lean muscle mass and fat stores that is largely refractory to standard nutritional supplementation.
Any adult experiencing an unexplained loss exceeding 5% to 10% of their baseline body weight over a span of three to six months should undergo a thorough clinical investigation to rule out occult gastrointestinal malignancy.
5. Endocrine disruption: New-Onset diabetes mellitus as an Early indicator
The pancreas is an endocrine powerhouse, housing specialized cell clusters responsible for glucose homeostasis. A fascinating and clinically critical warning sign of pancreatic cancer is the sudden onset of new-onset diabetes mellitus (or the abrupt destabilization of previously well-controlled type 2 diabetes) in individuals over the age of 50, particularly when it occurs in the absence of traditional risk factors such as obesity or a strong family history of metabolic disease.
The paraneoplastic and structural diabetic link
The association between pancreatic adenocarcinoma and diabetes is bidirectional and deeply intertwined:
Beta-Cell Destruction: As a malignant neoplasm expands within the pancreatic architecture, it directly destroys or displaces adjacent insulin-producing beta cells, impairing endogenous insulin secretion.
Tumor-Mediated Insulin Resistance: Emerging oncologic research demonstrates that pancreatic cancer cells secrete specific circulating diabetogenic proteins (such as adrenomedullin) that induce peripheral insulin resistance in skeletal muscle, liver, and adipose tissue, driving hyperglycemia well before the tumor is large enough to be detected by standard cross-sectional imaging.
For clinicians, adult-onset diabetes diagnosed after age 50 that is accompanied by atypical clinical features, such as weight loss rather than weight gain, difficult-to-control blood glucose levels despite multiple oral hypoglycemic agents, or sudden requirements for insulin, should not be classified automatically as routine type 2 diabetes. Instead, it should serve as a high-yield clinical trigger prompting targeted screening of the pancreatic parenchyma via high-resolution contrast-enhanced computed tomography (CT) or magnetic resonance cholangiopancreatography (MRCP). Recognizing this subtle endocrine shift offers a crucial window of opportunity to detect pancreatic malignancy at a potentially pre-symptomatic or early localized stage, fundamentally altering the trajectory of patient survival.
The subtle and overlooked indicators: New-Onset diabetes and digestive disruptions
While classic symptoms like jaundice and radiating back pain often command medical attention, pancreatic cancer frequently announces its presence through far more subtle metabolic and gastrointestinal shifts. Among these, new-onset diabetes mellitus in individuals over the age of 50 stands out as one of the most critical diagnostic windows.
The pancreas is fundamentally responsible for producing insulin and glucagon, the hormones that regulate blood glucose levels. When a malignant tumor develops within the pancreatic tissue, it can progressively destroy the insulin-producing beta cells or induce a state of profound insulin resistance. Consequently, a patient who has maintained normal blood sugar levels throughout their life may suddenly develop Type 2 diabetes without traditional risk factors such as significant obesity or a strong genetic predisposition. Clinical research indicates that approximately one-quarter of all pancreatic cancer patients are diagnosed with diabetes in the three years preceding their cancer diagnosis. Recognizing this sudden metabolic shift as a potential red flag rather than routine adult-onset diabetes can alter the timeline of early detection.
In tandem with glucose dysregulation, patients often experience pronounced changes in exocrine function, the pancreas’s role in producing digestive enzymes. When a tumor blocks the pancreatic duct, enzymes such as lipase, amylase, and protease fail to reach the small intestine. This condition, known as exocrine pancreatic insufficiency (EPI), leads to malabsorption.
Steatorrhea: Because fats cannot be properly broken down, stools often become pale, bulky, greasy, or oily, and they frequently float in the toilet bowl.
Persistent Foul Odor: The presence of undigested fats and proteins results in unusually foul-smelling bowel movements.
Early Satiety and Bloating: Tumors can press against the stomach, causing patients to feel uncomfortably full after consuming only a small amount of food, which severely depresses appetite and accelerates unintended weight loss.
Systemic red flags: Blood clots, profound fatigue, and Cachexia
Pancreatic malignancies also exert systemic effects that extend far beyond the localized abdominal cavity. One of the more peculiar and dangerous manifestations is an increased tendency to form abnormal blood clots, clinically referred to as a hypercoagulable state.
Deep vein thrombosis (DVT) and Trousseau’s syndrome
Cancer cells secrete chemical factors into the bloodstream that activate the coagulation cascade, making blood prone to clotting. A deep vein thrombosis typically presents as painful swelling, redness, or warmth in one leg (most commonly the calf). In some cases, patients experience migratory superficial thrombophlebitis, blood clots that repeatedly form and resolve in different superficial veins across the body, a classic clinical phenomenon historically recognized as Trousseau's syndrome. Because a pulmonary embolism (a clot traveling to the lungs) is a life-threatening medical emergency, any unexplained DVT warrants a comprehensive medical workup that looks beyond the extremity.
Cancer Cachexia and exhaustion
Unexplained weight loss coupled with severe, unremitting fatigue is another hallmark constellation of symptoms. Cancer cachexia, a complex metabolic syndrome characterized by severe muscle wasting, loss of adipose tissue, and systemic inflammation, is driven by tumor-derived cytokines. Even when patients attempt to eat normally, their bodies hypermetabolize nutrients while the tumor actively consumes energy resources. This physiological stress creates a deep, debilitating fatigue that does not resolve with adequate sleep or rest, setting it apart from ordinary lifestyle burnout.
Why Early detection remains a formidable challenge
Understanding why pancreatic cancer warning signs are frequently missed requires looking at the anatomical reality of the organ. Tucked deep within the upper abdomen, nestled behind the stomach, liver, and intestines, the pancreas is virtually invisible during standard physical examinations in the early stages of disease. The symptoms of pancreatic cancer, such as mild indigestion, back strain, generalized fatigue, or minor shifts in bowel patterns, heavily overlap with a myriad of benign gastrointestinal disorders, including irritable bowel syndrome, gastritis, gallstones, and routine musculoskeletal back pain.
Because the body can often compensate for localized cellular disruption, tumors in the body or tail of the pancreas can grow quite large before causing any noticeable obstruction or nerve invasion. Consequently, many patients are diagnosed only after the disease has advanced or metastasized to nearby blood vessels or the liver.
The Medical Imperative: Persistence is key. While the vast majority of individuals experiencing back pain or indigestion do not have pancreatic cancer, symptoms that are persistent, progressive, new, and completely unexplained by lifestyle factors demand a thorough medical re-evaluation.
Navigating the diagnostic maze
When a physician suspects potential pancreatic pathology based on warning signs, a structured diagnostic protocol is deployed to confirm or rule out malignancy. Modern diagnostic medicine relies on a combination of advanced imaging and targeted biomarker testing:
High-Resolution Cross-Sectional Imaging: Multiphase contrast-enhanced CT scans (computed tomography) of the abdomen are the primary gold standard for visualizing pancreatic masses, assessing tumor resectability, and evaluating vascular involvement. Magnetic resonance cholangiopancreatography (MRCP) provides detailed imaging of the pancreatic and bile ducts without ionizing radiation.
Endoscopic Ultrasound (EUS): This minimally invasive procedure involves passing a specialized endoscope equipped with an ultrasound probe down the esophagus and into the stomach and duodenum. EUS allows gastroenterologists to obtain high-resolution images of the pancreatic parenchyma and perform a fine-needle aspiration (FNA) biopsy to retrieve tissue samples for pathological analysis.
Serum Biomarkers: Blood tests may include carbohydrate antigen 19-9 (CA 19-9), which is frequently elevated in pancreatic ductal adenocarcinoma. While CA 19-9 is not sufficiently specific or sensitive to serve as a standalone general screening tool for asymptomatic populations, it is invaluable for monitoring treatment response and disease recurrence in diagnosed patients.
Empowering proactive health management
Pancreatic cancer remains one of the most aggressive malignancies in modern oncology, largely due to its silent early progression and the subtle nature of its initial warning signs. However, recognizing the constellation of risk factors and symptoms, ranging from painless jaundice and dark urine to deep, unremitting mid-back pain, sudden-onset diabetes in older adults, greasy malabsorptive stools, and unexplained, rapid weight loss, provides a crucial defense mechanism.
Empowerment begins with active listening to one's own body. If you or a loved one experience persistent, progressive gastrointestinal symptoms or metabolic changes that defy explanation, do not dismiss them as routine stress or aging. Seeking prompt medical evaluation, advocating for specialized diagnostic imaging when symptoms persist, and maintaining open communication with healthcare providers can bridge the gap between late-stage discovery and timely, life-saving intervention.