For a 70-year-old woman, the definition of a "normal" or healthy weight is far more nuanced than a single number on a scale. It is an intricate interplay of physiological changes, metabolic shifts, muscle preservation, bone density, functional independence, and chronic disease risk. Aging is not merely a continuation of earlier adulthood; it is a distinct biological chapter accompanied by profound transformations in body composition. Understanding what constitutes a healthy weight at age 70 requires looking beyond conventional paradigms and embracing an approach that prioritizes vitality, strength, and resilience over antiquated aesthetic standards.
The paradigm shift: Why traditional BMI falls short in older adults
To understand weight in older adulthood, one must first recognize the limitations of the Body Mass Index (BMI). Developed in the 19th century by Belgian mathematician Adolphe Quetelet, BMI was designed as a tool to measure population-level trends, not individual health. It calculates weight relative to height (BMI=weight in kg/height in meters2BMI = ext{weight in kg} / ext{height in meters}^2BMI=weight in kg/height in meters2), but it remains entirely blind to what makes up that weight. It cannot distinguish between metabolically active muscle mass, dense bone tissue, visceral fat, and subcutaneous fat.
For a 70-year-old woman, relying solely on standard BMI charts can be misleading for several reasons:
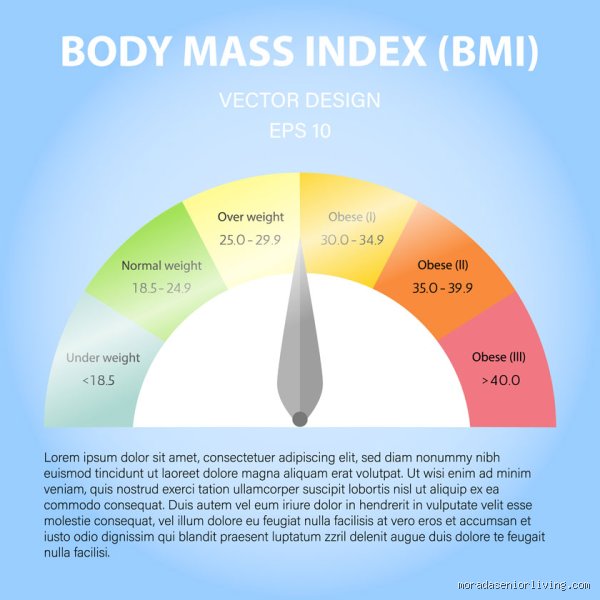
Sarcopenic Obesity: As women age, particularly following the hormonal shifts of menopause, there is a natural tendency to lose skeletal muscle mass, a process known as sarcopenia, while simultaneously accumulating body fat, particularly around the abdomen (visceral fat). A 70-year-old woman might have a BMI that falls squarely within the "normal" range (18.5 to 24.9), yet she may possess a high percentage of body fat and low muscle mass. This condition, sometimes called "skinny fat" or sarcopenic obesity, carries significant metabolic risks, including insulin resistance, cardiovascular strain, and functional decline, despite a normal scale weight.
Height Loss and Spinal Compression: Over the decades, cumulative wear and tear on the intervertebral discs, coupled with age-related bone mineral density loss (osteopenia or osteoporosis), often results in a measurable decrease in height. Because height is the denominator in the BMI equation, a shrinking denominator artificially inflates the BMI calculation, potentially categorizing a woman as overweight when her actual body mass has remained stable.
The "Obesity Paradox" in Gerontology: Interestingly, numerous large-scale epidemiological studies have suggested that older adults, particularly those over the parameter of 65 or 70, who fall into the overweight category (BMI of 25.0 to 29.9) or even the lower end of Class I obesity (BMI 30.0 to 34.9) often experience lower all-cause mortality and better resilience during acute illnesses, surgeries, or systemic infections compared to their normal-weight peers. A slightly higher energy reserve can act as a biological buffer against chronic wasting diseases, falls, and recovery periods.
Consequently, modern geriatric medicine views body weight not as an isolated static metric, but as a component of overall functional capacity and metabolic health.
The biological landscape: How Body composition changes at age 70
To evaluate weight at 70, we must examine the physiological canvas of the aging female body. By the eighth decade of life, several hallmark shifts have altered how the body processes energy, stores fat, and builds tissue:
Basal Metabolic Rate (BMR) Reduction: Due to the gradual loss of metabolically active lean muscle tissue and age-related declines in mitochondrial efficiency, resting energy expenditure decreases. If caloric intake remains identical to what it was at age 40 or 50, gradual fat accumulation becomes common, even with moderate physical activity.
Fat Redistribution: Hormonal shifts during and after menopause alter fat distribution pathways. Subcutaneous fat (the fat stored just beneath the skin on the hips and thighs) tends to decrease, while visceral fat (deep abdominal fat surrounding vital organs like the liver, pancreas, and intestines) increases. Visceral fat is hormonally active and secretes inflammatory cytokines, making its accumulation a more critical health indicator than total body weight.
Skeletal Integrity and Bone Mineral Density: Estrogen matters a lot in maintaining bone density. Following menopause, the rate of bone resorption outpaces bone formation. For a 70-year-old woman, maintaining adequate mechanical loading on the skeleton is vital. Extremely low body weight is frequently correlated with lower bone mineral density, significantly elevating the risk of fragility fractures resulting from minor falls.
Moving beyond the scale: Key markers of health at 70
Because a scale measures gravity's pull on total mass rather than health quality, a 70-year-old woman evaluating her physical status should look toward a comprehensive dashboard of metrics:
1. Waist Circumference and Waist-to-Height ratio
As noted, where fat is stored matters far more than total pounds. For women, a waist circumference measuring greater than 35 inches (88 centimeters) is generally associated with an increased risk of metabolic syndrome, type 2 diabetes, and cardiovascular disease, regardless of BMI. A simpler, highly effective metric is the waist-to-height ratio: keeping one's waist measurement to less than half of their height provides a reliable gauge of central adiposity.
2. Functional Strength and Muscle quality
Weight is meaningless if it cannot support an independent, active lifestyle. Functional fitness, assessed through indicators such as grip strength, the ability to rise from a chair without using one's arms, and walking speed, is a far more potent predictor of longevity and quality of life at age 70 than weight alone. Preservation of muscle mass through adequate dietary protein and resistance exercise protects metabolic health and prevents frailty.
3. Metabolic Biomarkers
A truly healthy weight is reflected internally. Regular assessment of fasting blood glucose, hemoglobin A1c, lipid profiles (HDL, LDL, triglycerides), and inflammatory markers (such as high-sensitivity C-reactive protein) offers a clearer picture of whether a person's weight is supporting metabolic homeostasis or driving systemic stress.
Beyond the scale: Clinical considerations for weight management in later life
As we continue our exploration into body weight during the seventh decade of life, it becomes increasingly clear that looking at a single number on a bathroom scale is an inadequate way to measure wellness. For a 70-year-old woman, weight is a dynamic reflection of metabolic health, bone density, and functional independence. Shifting our perspective from rigid cosmetic standards to longevity and resilience allows for a much healthier, more realistic approach to aging.
The role of Body composition: Muscle versus Fat
One of the primary reasons standard Body Mass Index (BMI) charts fall short for older adults is their inability to distinguish between lean muscle mass and adipose (fat) tissue.
Sarcopenia and Muscle Loss: As women age, particularly following the hormonal shifts of menopause, there is a natural tendency to lose muscle mass, a condition known as sarcopenia. If a 70-year-old woman focuses solely on losing weight through caloric restriction without incorporating resistance exercise and adequate protein intake, she is likely losing metabolically active muscle rather than fat.
Visceral Adiposity: Conversely, post-menopausal changes often promote a shift in fat distribution, encouraging fat storage around the abdominal organs (visceral fat) rather than subcutaneously in the hips and thighs. Visceral fat is biologically active and secretes inflammatory markers that increase cardiovascular risk, even if a woman’s overall weight appears "normal" on a standard chart.
Therefore, two women of the exact same height and weight at age 70 can experience vastly different health outcomes based entirely on their muscle-to-fat ratio.
Why a slightly higher BMI can be protective
Geriatric medicine has increasingly embraced the concept of the "obesity paradox" in older populations. While excess weight carries well-documented risks in younger adults, clinical data for individuals over 65 tells a slightly different story.
Research indicates that a slightly elevated BMI, traditionally classified as "overweight" (ranging roughly from 25 to 30), is often associated with the lowest all-cause mortality rates in older adults. There are several physiological reasons for this:
The Metabolic Reserve: Acute illnesses, infections, surgeries, or falls are common stressors in later life. A modest energy reserve provides a vital buffer, helping the body withstand the catabolic stress of recovery without descending into rapid malnutrition or frailty.
Bone Density Protection: Higher body weight places mechanical loading on the skeleton, which helps stimulate bone formation and reduce the risk of osteoporosis-related fractures, a major health threat for women in their 70s.
Immune Resilience: Chronic undernutrition and low body weight are heavily linked to compromised immune function, delayed wound healing, and higher rates of institutionalization among older demographics.
Practical metrics to evaluate health beyond weight
Instead of fixating on a specific poundage, healthcare providers look at a broader constellation of functional indicators to determine if a 70-year-old woman is thriving:
Grip Strength: Measured with a dynamometer, handgrip strength is a powerful proxy for overall bodily strength, functional independence, and systemic vitality.
Gait Speed: The speed at which an individual comfortably walks across a room correlates strongly with neurological health, cardiovascular fitness, and longevity.
Waist Circumference: Assessing abdominal girth provides a direct window into visceral fat accumulation. For women, maintaining a waist circumference below 35 inches is generally recommended to mitigate cardiometabolic risks, regardless of total weight.
Nutritional Status: Ensuring adequate intake of high-quality proteins, micronutrients (such as Vitamin D and calcium), and hydration takes precedence over aggressive dieting.
Conclusion and actionable guidance
For a 70-year-old woman, a "normal" or healthy weight cannot be distilled into a single rigid digit. While a modified BMI range of approximately 23 to 30 is widely accepted by geriatric specialists as a safe zone, context is everything. Weight stability, maintenance of physical strength, the ability to perform daily activities with ease, and joy in movement are far more telling markers of vitality than strict adherence to outdated height-weight tables.
Any intentional weight changes, whether gain or loss, should always be discussed thoroughly with a primary care physician or a clinical geriatric dietitian to ensure that muscle mass and nutritional integrity are carefully preserved.