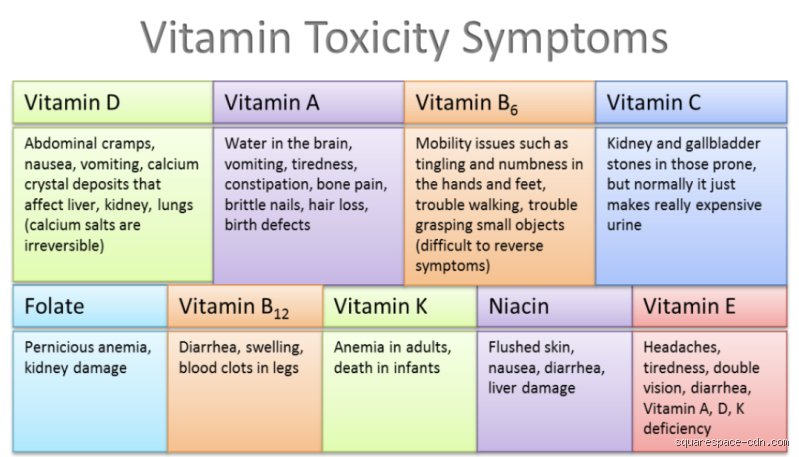
Understanding which vitamins to avoid or strictly regulate is critical for maintaining steady symptom control and avoiding dangerous drug-nutrient interactions.
The core mechanism: Why supplements clash with Parkinson’s medications
To understand why specific vitamins pose a risk, it is necessary to look at how the gold-standard Parkinson’s medication, levodopa (most commonly prescribed as carbidopa/levodopa, or Sinemet), works in the body.
Levodopa is an amino acid precursor that crosses the blood-brain barrier and converts into dopamine, replenishing the depleted stores caused by the loss of dopaminergic neurons in the substantia nigra. Because levodopa is fragile, it faces two major hurdles before it ever reaches the brain:
Premature Peripheral Conversion: Enzymes in the bloodstream and gut, specifically aromatic L-amino acid decarboxylase (AADC), want to convert levodopa into dopamine before it crosses the blood-brain barrier. If this happens in the bloodstream, the dopamine cannot enter the brain to help motor symptoms, and instead causes severe nausea, vomiting, and blood pressure drops. Medications like carbidopa or benserazide are paired with levodopa specifically to block this enzyme in the periphery.
Competitive Absorption: Levodopa relies on specialized transport proteins (specifically the large neutral amino acid transporter, LAT1) to move from the small intestine into the bloodstream and across the blood-brain barrier.
Vitamins and supplements that alter enzyme activity, bind to medications in the digestive tract, or compete for cellular transport can render a carefully calibrated dose of Parkinson's medication ineffective, triggering sudden "off" periods, rigidity, and tremors.
1. Vitamin B6 (Pyridoxine): The classic Levodopa antagonist
Vitamin B6 is perhaps the most historically notorious vitamin in Parkinson’s management, though its risk profile depends entirely on the specific medication regimen a patient takes.
The Biochemical Conflict Vitamin B6 acts as an essential cofactor for the enzyme aromatic L-amino acid decarboxylase (AADC), the exact enzyme responsible for converting levodopa into dopamine. When high doses of Vitamin B6 are introduced into the body, they supercharge this enzyme in the peripheral bloodstream, causing levodopa to convert into dopamine prematurely outside the brain.
Who Is at Risk?
Patients taking uncompounded Levodopa: For individuals taking plain levodopa without a decarboxylase inhibitor (a rare regimen today, though still used in specific clinical scenarios or certain regions), supplemental Vitamin B6, even in modest doses found in standard multivitamins (often 10 mg to 50 mg), can completely neutralize the therapeutic effect of the drug.
Patients taking Carbidopa/Levodopa or Benserazide/Levodopa: The addition of carbidopa largely protects levodopa from the effects of standard dietary Vitamin B6. However, megadoses of Vitamin B6 (typically defined as exceeding 50 mg to 100 mg per day, which are common in "B-Complex" or "stress-relief" supplements) can still overwhelm the protective capacity of carbidopa, leading to erratic symptom control and reduced medication efficacy.
Additional Neurotoxicity Risks Beyond drug interactions, chronic intake of high-dose Vitamin B6 (typically greater than 200 mg daily over several months) can cause sensory peripheral neuropathy, resulting in numbness, tingling, burning sensations, and loss of balance. Because individuals with Parkinson’s already contend with postural instability and gait disturbances, B6-induced neuropathy can significantly increase the risk of debilitating falls.
2. Iron supplements: The gut Absorption blocker
While technically a mineral rather than a vitamin, iron is present in the vast majority of standard daily multivitamins and is frequently taken independently to combat fatigue, one of the most common non-motor symptoms of Parkinson’s disease.
Chelation in the Digestive Tract Iron poses a direct physical barrier to Parkinson’s medications in the stomach and small intestine. When iron and levodopa (as well as entacapone, a COMT inhibitor used to prolong levodopa's effect) are present in the digestive tract at the same time, they undergo a chemical process called chelation.
Iron ions bind tightly to the levodopa or entacapone molecules, forming an insoluble complex that the intestinal wall cannot absorb. Clinical studies demonstrate that taking iron alongside carbidopa/levodopa can reduce the absorption of levodopa by 30% to 50%, essentially cutting a patient's medication dose in half.
The Brain Iron Accumulation Paradox The relationship between iron and Parkinson’s extends beyond the stomach. Post-mortem and advanced MRI studies consistently show that the substantia nigra of individuals with Parkinson’s contains abnormally high concentrations of iron. Excess free iron in the brain catalyzes the production of toxic free radicals (reactive oxygen species) via the Fenton reaction, driving oxidative stress and accelerating the death of dopamine-producing neurons.
Because of both the severe absorption block and the potential for neuro-oxidative stress, individuals with Parkinson's should never take iron supplements or iron-containing multivitamins unless a blood test (measuring serum ferritin and transferrin saturation) explicitly confirms iron-deficiency anemia. Even when medically necessary, iron must be separated from Parkinson’s medications by at least two to three hours.
3. High-Dose Vitamin e: Failed neuroprotection and Bleeding Risks
For decades, Vitamin E (alpha-tocopherol) was heavily promoted to Parkinson’s patients due to its potent antioxidant properties. The prevailing theory was that high doses of Vitamin E could neutralize free radicals in the brain and slow the progression of the disease.
Clinical Evidence and Lack of Efficacy This hypothesis was rigorously tested in the landmark DATATOP (Deprenyl and Tocopherol Antioxidative Therapy of Parkinsonism) clinical trial, which followed 800 early-stage Parkinson’s patients taking 2,000 IU of Vitamin E daily. The results were definitive: high-dose Vitamin E showed no measurable benefit in delaying disability or slowing the progression of Parkinson’s disease.
Why High-Dose Vitamin E Should Be Avoided Despite the lack of neurological benefit, high-dose Vitamin E carries substantial systemic risks, particularly for the older demographic most affected by Parkinson's:
Hemorrhagic Stroke and Bleeding: Doses exceeding 400 IU per day interfere with Vitamin K-dependent clotting factors and inhibit platelet aggregation. This significantly elevates the risk of severe bruising, gastrointestinal bleeding, and hemorrhagic stroke, a critical concern for patients experiencing frequent falls or those taking blood thinners (such as warfarin, apixaban, or daily aspirin).
Increased All-Cause Mortality: Meta-analyses of large clinical trials have linked chronic supplementation of Vitamin E at doses of 400 IU/day or higher to a statistically significant increase in all-cause mortality and heart failure in older adults.
While obtaining Vitamin E naturally through whole foods (such as almonds, sunflower seeds, spinach, and olive oil) is safe and beneficial, high-dose synthetic supplements should be avoided.
4. Vitamin B3 (Niacin) and NAD+ precursors: Dose-Dependent complications
Vitamin B3 (niacin, nicotinamide, and newer derivatives like nicotinamide riboside) has attracted recent scientific interest because of its role in cellular energy production (NAD+ synthesis) and mitochondrial function, a known weak point in Parkinson’s pathology. However, unsupervised supplementation carries distinct drawbacks.
Vasodilation and Orthostatic Hypotension Standard niacin (nicotinic acid) in doses above 50 mg to 100 mg triggers a well-known "niacin flush", intense redness, warmth, and itching caused by the rapid dilation of peripheral blood vessels. For someone with Parkinson’s disease, this sudden vasodilation is far more than a cosmetic annoyance.
Many people with Parkinson’s suffer from neurogenic orthostatic hypotension (nOH), a condition where the autonomic nervous system fails to constrict blood vessels properly upon standing, causing a dangerous drop in blood pressure. Levodopa and dopamine agonists themselves lower blood pressure. Adding high-dose niacin can trigger severe dizziness, lightheadedness, and syncope (fainting), dramatically elevating the risk of head trauma and fractures.
Methylation Depletion Emerging clinical trials exploring high-dose niacinamide or nicotinamide riboside in Parkinson’s are carefully monitored because excessive intake of Vitamin B3 derivatives can deplete the body's pool of methyl groups. Because the enzyme COMT (catechol-O-methyltransferase) relies on methyl groups to metabolize dopamine and levodopa, chronically saturating the body with high doses of B3 can alter homocysteine levels and disrupt normal neurotransmitter metabolism.
In the second part of this guide, we will examine fat-soluble vitamins that accumulate to toxic levels (Vitamin A), minerals that mimic or worsen movement disorders (Manganese and Copper), and herbal/over-the-counter supplements (such as St. John's Wort, Mucuna pruriens, and Melatonin) that carry hidden risks for Parkinson's patients.
Vitamin e: The disappointing antioxidant
For years, researchers hoped that high-dose Vitamin E (alpha-tocopherol) would slow the progression of Parkinson’s disease by neutralizing free radicals and protecting dopaminergic neurons from oxidative stress. This optimism led to the landmark DATATOP (Deprenyl and Tocopherol Antioxidative Therapy of Parkinsonism) clinical trial. Unfortunately, the results revealed that Vitamin E offered no measurable neuroprotective benefit in delaying the need for levodopa therapy.
Beyond its lack of efficacy in halting disease progression, taking high-dose Vitamin E supplements carries distinct risks for individuals with Parkinson's:
Increased Bleeding Risk: Vitamin E acts as a mild blood thinner by inhibiting platelet aggregation. Because motor symptoms like postural instability and freezing of gait significantly elevate the risk of falls in Parkinson's patients, taking high-dose Vitamin E increases the danger of severe bruising, internal bleeding, or hemorrhagic stroke following a fall.
Medication Interactions: If you are taking anticoagulant or antiplatelet medications, such as warfarin, apixaban, or daily aspirin, for cardiovascular health, adding Vitamin E compounds the blood-thinning effect.
Pro-Oxidant Potential: At megadoses (typically above 400 IU per day), Vitamin E can paradoxically shift from acting as an antioxidant to a pro-oxidant, potentially exacerbating cellular stress rather than relieving it.
Obtaining Vitamin E through whole foods like almonds, sunflower seeds, spinach, and avocados is entirely safe and beneficial, whereas isolated, high-dose synthetic supplements should generally be avoided.
High-Dose Vitamin a and Beta-Carotene
Vitamin A is a fat-soluble vitamin essential for vision, immune function, and cellular communication. Because it is fat-soluble, excess amounts are not easily excreted in the urine; instead, they accumulate in the liver and adipose tissue, leading to toxicity (hypervitaminosis A).
In the context of Parkinson’s disease, excessive Vitamin A supplementation presents overlapping neurological and physical hazards:
Mimicking or Worsening Neurological Symptoms: Vitamin A toxicity causes increased intracranial pressure, resulting in severe headaches, dizziness, blurred vision, and profound fatigue. In a patient with Parkinson’s, these symptoms can easily be mistaken for disease progression or medication side effects, leading to unnecessary adjustments in dopaminergic therapy.
Bone Density Loss: Chronic overconsumption of preformed Vitamin A (retinol) has been linked to decreased bone mineral density and an increased risk of fractures. People with Parkinson’s already face a substantially higher risk of osteoporosis and hip fractures due to reduced mobility, lower Vitamin D levels, and frequent falls.
High-dose beta-carotene supplements, a precursor to Vitamin A, have been associated with an increased risk of lung cancer in current and former smokers. Unless a specific deficiency is diagnosed by a physician, standalone Vitamin A supplements are rarely warranted.
Niacin (Vitamin B3) in Megadoses
The relationship between Vitamin B3 (niacin) and Parkinson’s disease is nuanced. Emerging research suggests that physiological levels of niacin, and specific forms like nicotinamide riboside, may support mitochondrial health and reduce neuroinflammation. However, high-dose, over-the-counter niacin supplements (often taken to manage cholesterol) pose significant tolerability and safety issues for those living with Parkinson's.
The primary concern is niacin-induced vasodilation, commonly known as the "niacin flush." High doses cause blood vessels near the skin's surface to widen rapidly, triggering intense redness, warmth, itching, and tingling. More importantly, this sudden peripheral vasodilation can cause a sharp drop in blood pressure.
Because neurogenic orthostatic hypotension (a sudden drop in blood pressure upon standing) affects up to 30% to 50% of people with Parkinson’s disease, and is further worsened by medications like levodopa and dopamine agonists, taking high-dose niacin can trigger severe lightheadedness, fainting, and dangerous falls. Sustained-release niacin formulations carry a documented risk of hepatotoxicity (liver damage), placing extra metabolic strain on the body alongside daily Parkinson's medications.
The hidden danger of "Brain health" proprietary Blends
Walk down any pharmacy aisle, and you will find dozens of over-the-counter supplements marketed for "neuroprotection," "memory support," or "cellular energy." For individuals managing a progressive neurological condition, these products are deeply appealing, and uniquely hazardous.
Unlike prescription medications, dietary supplements are not rigorously tested for safety, purity, or efficacy before reaching store shelves. For someone with Parkinson's, multi-ingredient blends create three major problems:
Unregulated Megadoses: A single "brain health" capsule may contain 500% to 2,000% of the Recommended Dietary Allowance (RDA) for Vitamin B6, Vitamin E, or trace minerals. If you are also taking a daily multivitamin, you can inadvertently reach toxic thresholds.
Undisclosed Herbal Interactions: Many vitamin complexes include herbal extracts like St. John’s Wort, Ginkgo biloba, or Mucuna pruriens (velvet bean). St. John’s Wort alters liver enzymes that metabolize medications; Ginkgo biloba increases bleeding risk; and Mucuna pruriens contains naturally occurring, unstandardized levels of L-dopa, which can cause unpredictable spikes in dyskinesia, nausea, and hallucinations when combined with prescription carbidopa/levodopa.
Mineral Chelation: Supplements that combine vitamins with minerals like iron, zinc, or magnesium can bind to levodopa in the gastrointestinal tract, preventing the medication from entering the bloodstream and triggering sudden "off" periods where motor symptoms return abruptly.
Summary table: Vitamins to avoid or limit with Parkinson's
| Vitamin / Supplement | Primary Risk with Parkinson's | Safe Approach |
|---|---|---|
| Vitamin B6 (Pyridoxine) | Inactivates standalone L-dopa; high doses (>100 mg/day) cause peripheral neuropathy. | Safe in standard doses if taking carbidopa/levodopa; avoid megadoses. |
| Vitamin E | Increases bleeding risk after falls; interacts with blood thinners; no proven neuroprotection. | Obtain through whole foods (nuts, seeds, leafy greens) rather than high-dose pills. |
| Vitamin A (Retinol) | Fat-soluble toxicity causes dizziness, headaches, and reduced bone density (higher fracture risk). | Avoid standalone supplements unless treating a confirmed clinical deficiency. |
| Niacin (Vitamin B3) | High doses cause vasodilation, worsening orthostatic hypotension and fainting risks. | Avoid high-dose flushing niacin; discuss targeted B3 forms with a neurologist. |
| Multi-Ingredient "Brain" Blends | Unregulated dosages, hidden herbs (Mucuna), and minerals that block levodopa absorption. | Stick to single-ingredient, third-party tested supplements (USP or NSF certified). |
Practical guidelines for Safe supplementation
Navigating nutrition with Parkinson's disease does not mean avoiding all supplements. In fact, targeted supplementation, such as Vitamin D3 for bone health and immune support, or Vitamin B12 to counteract levodopa-induced homocysteine elevation, is frequently recommended by movement disorder specialists. The goal is precision rather than guesswork.
To protect the effectiveness of your Parkinson's medications and minimize side effects, follow these core principles:
Verify Third-Party Testing: Look for seals from independent organizations such as USP (U.S. Pharmacopeia), NSF International, or ConsumerLab. These certifications verify that the bottle actually contains what is listed on the label and is free from heavy metals or unlisted pharmaceuticals.
Separate Minerals from Levodopa: Even if a vitamin complex contains small amounts of iron, calcium, or zinc, space it at least 2 hours apart from your carbidopa/levodopa doses to ensure optimal medication absorption.
Request Baseline Blood Panels: Before starting any new vitamin regimen, ask your neurologist or primary care physician to check your serum levels of Vitamin B12, methylmalonic acid, homocysteine, and 25-hydroxy Vitamin D. Supplementing based on lab work ensures you address genuine deficiencies without risking toxicity.
Audit Your Full Regimen Annually: Bring every bottle, including over-the-counter vitamins, gummies, and herbal teas, to your neurology appointments. A quick medication reconciliation with your care team can prevent subtle nutrient-drug interactions from undermining your symptom control.