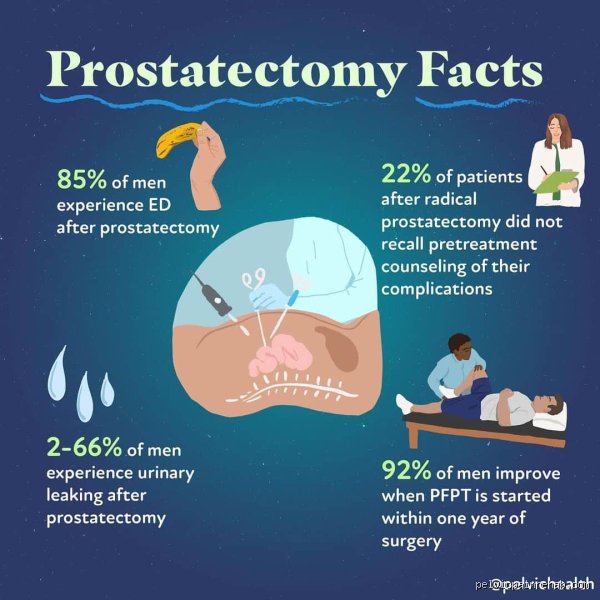
Understanding the downsides, side effects, and long-term functional implications of prostate removal is essential for patients and their care partners. This comprehensive first part of our expert analysis delves deeply into the anatomical realities, immediate postoperative hurdles, and the profound impacts on urinary and sexual function that define the "downside" of prostate surgery.
1. Navigating the anatomical landscape and surgical realities
To understand why prostate removal carries substantial functional consequences, one must first appreciate the delicate anatomical neighborhood the prostate occupies. Roughly the size of a walnut, the prostate gland sits directly beneath the bladder, encircling the urethra, the muscular tube responsible for carrying urine out of the body and semen during ejaculation.
More critically, the prostate is intimately intertwined with an intricate network of nerves, blood vessels, and supportive musculature. The neurovascular bundles, which are responsible for generating erectile function, run alongside the capsule of the prostate. The urinary sphincter mechanism, the complex arrangement of muscles that controls voluntary urinary continence, lies immediately adjacent to, and sometimes relies upon, the apex of the prostate gland.
During a radical prostatectomy (whether performed via open surgery, laparoscopy, or robot-assisted techniques), the surgeon must excise the entire prostate gland along with the seminal vesicles and frequently surrounding lymph nodes. Even with the advent of nerve-sparing techniques, which attempt to preserve the delicate erectile nerves when cancer localization permits, the physical disruption to this tightly packed anatomical zone is profound. The structural alterations inevitably create a ripple effect across multiple bodily systems.
2. Urinary dysfunction: The immediate and Long-Term challenge
One of the most frequent and distressing downsides of prostate removal is the disruption of normal urinary control. Because the prostate acts as a structural anchor and contributes to the natural closure mechanism of the urinary tract, its absence requires the body to rely entirely on the external urinary sphincter to maintain continence.
Immediate postoperative incontinence
Immediately following the removal of the catheter (typically one to two weeks post-surgery), almost all patients experience a degree of urinary leakage or outright incontinence. When the catheter is first removed, the sphincter muscles are often stunned, weakened, or temporarily bruised from surgical manipulation. Coughing, sneezing, laughing, or standing up can trigger involuntary urine leakage. While pelvic floor muscle rehabilitation (Kegel exercises) and time help the vast majority of patients regain continence over a period of weeks to months, this phase represents a significant disruption to daily life, confidence, and comfort.
Long-Term urinary complications
While most men achieve good continence control by the one-year mark, a subset of patients experience long-term or permanent stress urinary incontinence, requiring ongoing use of pads or specialized management strategies. The healing process at the anastomosis, the surgical reconnection site where the bladder is stitched directly to the urethra, can occasionally lead to scar tissue formation known as a vesicourethral anastomotic stricture. This narrowing of the urinary passage obstructs normal urine flow, causing weak streams, urinary hesitancy, or recurrent infections, and may necessitate secondary outpatient procedures (such as urethral dilation or laser incision) to restore normal caliber.
3. Sexual dysfunction: Ejaculatory loss and erectile alterations
The impact of prostate removal on male sexual health is profound, multi-dimensional, and often represents the most emotionally challenging aspect of the surgical downside.
Permanent loss of ejaculation
The physiological reality of a radical prostatectomy includes the permanent cessation of antegrade ejaculation. Because the prostate and seminal vesicles, the organs responsible for producing the fluid components of semen, are entirely removed, and the vas deferens are surgically transected and sealed, men undergoing this procedure will experience "dry orgasms." While the sensory experience of climaxing may remain largely intact for many individuals, the physical expulsion of seminal fluid is gone forever. This has direct implications for natural fertility, meaning patients desiring biological children post-surgery must rely on pre-surgical sperm banking and assisted reproductive technologies.
Erectile dysfunction (ED) and nerve damage
Erectile function relies on a delicate electrochemical signaling cascade involving the cavernous nerves that run flush against the prostate gland. Even when a surgeon performs a meticulous "nerve-sparing" procedure, these microscopic nerves suffer from stretching, thermal energy (if using electrocautery), or bruising during the dissection.
Consequently, postoperative erectile dysfunction is virtually universal in the immediate aftermath of surgery. Recovery of natural erectile function is a slow, gradual process that can take anywhere from 12 to 36 months. Recovery rates depend heavily on:
Pre-surgical baseline: Age and existing erectile function prior to surgery.
Surgical technique: Whether unilateral or bilateral nerve-sparing was technically feasible based on the cancer's proximity to the capsule.
Penile rehabilitation protocols: Early introduction of phosphodiesterase type 5 (PDE5) inhibitors, vacuum erection devices, or intracavernosal injections to maintain penile blood flow and prevent tissue fibrosis during the recovery window.
Despite best medical efforts, a significant percentage of patients experience permanent erectile dysfunction, requiring assistive devices or medical therapies to achieve erections sufficient for penetration.
...impact on intimacy, self-esteem, and relationship dynamics. When spontaneity is compromised and physical changes alter body image, emotional strains can surface. Counseling, open communication with partners, and specialized urological rehabilitation programs are vital components of comprehensive recovery, ensuring that patients do not navigate these psychological hurdles in isolation.
Long-Term oncological and anatomical considerations
Beyond the immediate postoperative and medium-term functional recovery phases, patients must weigh the long-term anatomical alterations resulting from a radical prostatectomy. Because the prostate and seminal vesicles are completely excised, natural seminal fluid production ceases permanently. This results in absolute infertility, meaning biological fatherhood post-surgery is only achievable via prior sperm cryopreservation (sperm banking) and assisted reproductive technologies like IVF.
Structural changes at the bladder-urethra junction can occasionally lead to late-onset complications such as bladder neck contracture or urethral stricture, scar tissue formation that narrows the urinary passage and causes obstructive voiding symptoms months or years down the line. While often treatable with minimally invasive outpatient procedures like dilation, it represents an ongoing maintenance of urinary tract health.
Weighing risks against benefits
Deciding to undergo prostate removal requires a deeply personalized risk-benefit analysis. While a radical prostatectomy remains a cornerstone treatment with high success rates for local disease control, the trade-offs involve significant physiological and emotional adjustments. Understanding these potential downsides, ranging from temporary urinary leakage and erectile dysfunction to permanent anatomical and reproductive changes, empowers patients and their healthcare teams to map out proactive rehabilitation strategies, set realistic expectations, and optimize long-term quality of life.