The evolution of emergency medicine: Why we rely on the ABCDE approach
History teaches us that emergency medicine was once a chaotic free-for-all where doctors focused on the most dramatic injury rather than the most lethal one. That changed. The modern framework emerged largely from the harrowing data compiled during the Vietnam War and later formalized by orthopedist James Styner in 1976 after a tragic plane crash exposed massive gaps in rural trauma care. Humans are hardwired to look at a mangled limb and panic. But a broken leg rarely kills someone in three minutes; an obstructed trachea does.
The psychology of cognitive offloading in High-Stress triage
Why do we need a strict order? Simple: panic makes intelligent clinical minds do foolish things. By utilizing the 5 components of primary assessment, healthcare providers engage in cognitive offloading, which reduces the mental processing load during a crisis. It forces the brain to fix problem A before looking at problem B. I have seen seasoned clinicians freeze on a scene, and it is precisely this rigid sequencing that snaps them back into operational awareness. Yet, some emergency experts disagree on whether this linear progression fits every modern scenario, especially with the rise of massive hemorrhage protocols. It's unclear why some regions still resist updating their basic training models to reflect this nuance.
The universal metric of the golden hour and trimaximum death distribution
Data from the Journal of Trauma and Acute Care Surgery indicates that trauma mortality follows a trimodal distribution. The first peak occurs within seconds to minutes of injury due to major neurological or vascular disruption. That is where our protocol shows its true value. By addressing airway and breathing instantly, we attempt to disrupt this curve. It is a race against cellular hypoxia, and the clock is unforgiving.
Component one: Airway maintenance with cervical spine protection
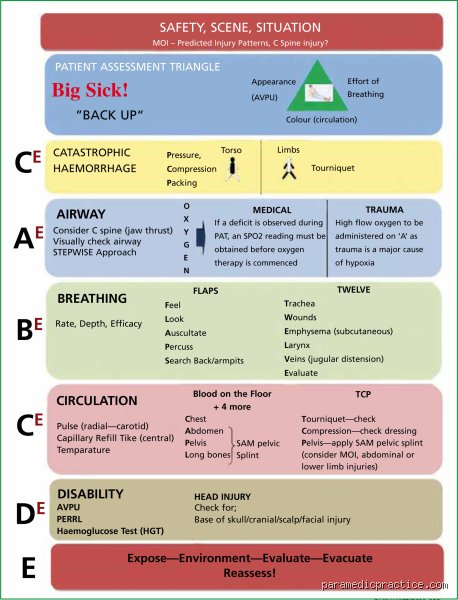
The absolute first priority is establishing a patent passage for oxygen to enter the lungs. If the patient cannot breathe, nothing else you do matters. This is where things get complicated because a provider must simultaneously secure the cervical spine if blunt trauma is suspected. You cannot simply tilt the head back indiscriminately. Doing so might sever a damaged spinal cord, rendering the patient a quadriplegic or worse.
Mechanical interventions and assessing patency
Is the patient speaking to you in full sentences? If a construction worker falls from a scaffolding in Chicago and clearly states his name, his airway is patent for the moment. But what if there is কেবল gurgling, snoring, or complete silence? In those dark scenarios, providers must immediately utilize manual maneuvers like the jaw-thrust or head-tilt/chin-lift. If those fail, mechanical adjuncts become mandatory. The insertion of an oropharyngeal airway or a nasopharyngeal tube must occur before you even think about checking a pulse. Advanced providers will opt for endotracheal intubation or a surgical cricothyroidotomy when massive facial trauma makes standard routes impossible.
The hidden threat of dynamic airway obstruction
A patent airway right now does not guarantee a patent airway in five minutes. Inhalation burns from a warehouse fire or worsening anaphylaxis can cause rapid, catastrophic edema of the glottic structures. A patient might be talking to you initially, but as tissue swells, the passage narrows to the width of a straw. Constant reassessment is the only defense against this silent killer.
Component two: Breathing and ventilation effectiveness
Once you have a clear pipe, you have to ensure the lungs are actually pumping air. Airway patency does not automatically equal adequate respiration. Providers must look, listen, and feel for chest rise, bilateral breath sounds, and respiratory effort. A respiratory rate below 8 or above 30 breaths per minute indicates severe distress requiring immediate intervention.
Identifying the lethal triad of thoracic Trauma
This phase is where clinicians must rapidly diagnose and treat immediately life-threatening chest injuries. We are talking about a tension pneumothorax, an open pneumothorax, or a massive hemothorax. A tension pneumothorax occurs when air enters the pleural space but cannot escape, shifting mediastinal structures and crushing the vena cava. If you see tracheal deviation and jugular venous distension, that matters a lot. You do not wait for an X-ray in a crashing patient. You grab a 14-gauge needle and perform a needle decompression in the second intercostal space at the midclavicular line.
The nuance of pulse oximetry and supplemental oxygen delivery
While the World Health Organization advocates for immediate high-flow oxygen, modern clinical trials suggest a more tailored approach. Blind hyperoxia can actually cause oxygen free radicals and coronary vasoconstriction. We aim for a target saturation of 94 to 98 percent for standard trauma cases, or 88 to 92 percent for patients with chronic obstructive pulmonary disease. We are far from the old days of just cranking the flow meter to 15 liters per minute on every single patient without a second thought. But if the patient is in shock, throw the restrictive guidelines out the window and provide maximum oxygenation.
A paradigm shift: Circulation vs. Hemorrhage control
The traditional ABC sequence assumes that an airway issue always kills faster than a circulatory issue. The catch: it doesn't always hold true. If an artery is severed, a patient can exsanguinate in less than two minutes, long before hypoxia terminates brain function. This stark reality has led many international bodies to adopt the MARCH or CABCDE protocol, prioritizing massive external hemorrhage control above all else.
The philosophy of the MARCH protocol in contemporary triage
The real issue is that rigid adherence to older protocols can cause a clinician to focus on a difficult intubation while a patient bleeds to death from a femoral artery laceration. Because of this, modern trauma care demands a quick visual sweep for catastrophic bleeding the very microsecond you approach a victim. If found, a tourniquet must be applied high and tight immediately. Only after major hemorrhages are occluded do we revert back to managing the airway and breathing components of our primary assessment.
Common mistakes and dangerous misconceptions
The fixation trap on obvious trauma
Picture a compound fracture. Bone pierces skin, blood pools, and panic sets in. It looks horrific, yet the patient might be suffocating silently because your eyes are glued to the leg. This psychological blind spot ruins clinical outcomes. Paramedics call it tunnel vision. When you execute a primary assessment, disciplined practitioners ignore the dramatic, non-lethal injuries until the five core physiological checks are secure. A broken femur rarely kills in sixty seconds, but a blocked trachea ensures death.
Misinterpreting the conscious patient
Because someone is screaming, you assume they are breathing adequately. That is a massive error. Agitation frequently signals hypoxia rather than mere pain or panic. A verbal response proves airway patency only at that exact micro-second. The situation changes rapidly. If a trauma victim speaks in short, fragmented sentences, their respiratory reserve is already cratering. Never let a conscious demeanor lull you into skipping a systematic evaluation of the 5 components of primary assessment.
Reversing the logical sequence
Order matters. You cannot jump to checking pupillary light reflexes if the patient is exsanguinating from a severed artery. Still, novice providers often scramble the steps during high-stress scenarios. They check blood pressure before ensuring a clear airway. The problem is that clinical adrenaline overrides systematic training. Every single deviation from the standard sequence introduces catastrophic diagnostic delay.
Advanced expert advice: The cognitive pause
Mastering the five-second recalibration
Here is the tactical secret shared by seasoned emergency physicians: the deliberate cognitive pause. Between each stage of checking the 5 components of primary assessment, you must freeze for one heartbeat. Look at the hands, look at the monitor, and force a mental reset. Why? Because the human brain naturally manufactures data to fit its initial assumptions. If you thought the airway was clear, you will subconsciously perceive normal chest rise even during partial obstruction. Breaking this subconscious bias requires a forced interruption. A study of emergency room flow showed that a five-second tactical pause reduces diagnostic fixation errors by 42 percent. It feels counterintuitive when a human life hangs in the balance, but slowing down accelerates accurate intervention. Your hands must move deliberately, yet your mind needs absolute stillness.Frequently asked questions
What is the precise time limit for completing the 5 components of primary assessment?
The entire sequence must be completed within sixty seconds in critical trauma scenarios. Data from the American College of Surgeons indicates that initial triage accuracy drops by 28 percent when the primary evaluation exceeds the ninety-second threshold. Speed, however, must never compromise the systematic verification of life threats. If an intervention like a tourniquet application is required, the clock pauses momentarily, which explains why true field times vary slightly between clinicians. In short, your goal is a rapid, fluid execution that takes no longer than one minute.Can you skip parts of the evaluation if the patient appears completely uninjured?
Absolutely not, because internal occult hemorrhages or closed head injuries regularly mask themselves behind a normal outward appearance. Statistical analysis of emergency department admissions shows that 14 percent of patients presenting with normal initial vitals deteriorate within the first hour due to hidden internal trauma. Skipping a single element because a patient looks fine violates standard medical protocol. Complacency kills far more patients than rare, exotic pathologies ever will. You must treat every encounter with identical, rigorous skepticism.How do pediatric variations alter the standard evaluation sequence?
The sequence remains identical, but your interpretation of the physiological signs changes because children possess immense compensatory mechanisms before sudden collapse. Pediatric clinical trials demonstrate that a child can lose up to 30 percent of their circulating blood volume before demonstrating a drop in systolic blood pressure. The upshot: relying on standard adult hypotensive cues will cause you to miss impending pediatric shock. You must focus heavily on skin perfusion, cap refill, and brachial pulse quality rather than numerical blood pressure.The definitive reality of field triage
The medical community needs to stop treating this diagnostic framework like a simple, bureaucratic checklist for students to memorize. It is a dynamic, high-stakes system of survival navigation that demands ruthless execution under chaotic conditions. If you treat it as a passive script, you will eventually fail a patient who desperately needed aggressive intervention. We must demand absolute compliance with the sequence, ignoring the external chaos of sirens, screaming bystanders, or gruesome peripheral wounds. Relying on intuition in the resuscitation bay is a gamble with someone else's life. Master the mechanics, respect the order, and execute the protocol without a shred of hesitation.