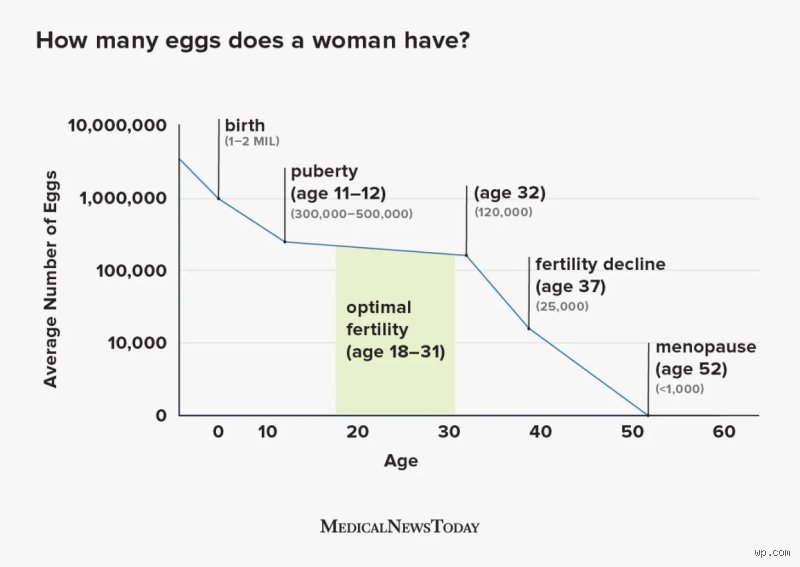
To truly grasp the quantitative landscape after age thirty, one must first look at the baseline. At birth, a female infant possesses roughly one to two million eggs. By the time puberty arrives, that number has already plummeted via natural cell death (atresia) to between 300,000 and 400,000. Every single month thereafter, a continuous, hormone-independent loss occurs alongside the monthly recruitment of a dominant follicle. By the time a person reaches their 30th birthday, the average ovarian reserve hovers around 10,000 to 12,000 eggs—representing a staggering loss of roughly 95% to 97% of the original congenital pool. From this milestone onward, the trajectory of loss shifts from a steady slope to a steeper descent.
The mechanics of accelerated attrition
The transition past the third decade is defined not just by a lower absolute number of oocytes, but by a distinct acceleration in the rate of loss. While the biological mechanisms governing this speed-up are multifaceted, they are deeply tied to follicular dynamics and local ovarian microenvironments. As the total pool shrinks below a critical threshold—typically estimated to occur around the mid-30s, the remaining follicles appear to deplete at an even faster relative velocity. This phase shift underscores why clinical guidance often emphasizes that fertility changes are nonlinear; the curve steepens significantly with each passing year.
At a microscopic level, the ovaries are constantly burning through their stock. Each month, a cohort of primordial follicles is recruited, but only one typically matures into an ovulated egg while the rest undergo atresia. As a person moves through their thirties, the quality of the remaining recruitment pool also begins to shift in tandem with the quantity. The cumulative impact of oxidative stress, mitochondrial DNA mutations, and meiotic spindle errors over decades begins to manifest structurally within the oocytes themselves. Consequently, the physiological challenge after 30 is twofold: dealing with a diminishing absolute volume of cells while simultaneously navigating an increasing proportion of cells with compromised chromosomal integrity.
Follicular recruitment and hormonal feedback loops
The dwindling egg supply directly alters the endocrine signaling between the ovaries and the brain, reshaping the menstrual cycle long before clinical menopause or even perimenopause sets in. The brain, via the hypothalamus and pituitary gland, relies on feedback signals to regulate reproductive hormones. As the number of healthy, responsive follicles declines, the production of Anti-Müllerian Hormone (AMH), a protein secreted by cells in early-stage follicles, drops correspondingly. Low AMH acts as an early warning indicator that the ovarian reserve is contracting.
In response to falling AMH and inhibin B levels, the pituitary gland ramps up its secretion of Follicle-Stimulating Hormone (FSH) to try and coax the aging ovaries into recruiting follicles. This subtle hormonal elevation is a hallmark of early reproductive aging. Because FSH levels rise, the follicular phase of the menstrual cycle often shortens, causing overall cycle lengths to compress from a standard 28 days to 24 or 25 days. These microscopic and hormonal adjustments serve as the unseen prologue to the broader clinical shifts that become more pronounced as a person approaches age 35 and beyond.
Quantifying the reserve through clinical diagnostics
Because subjective feelings or regular menstrual cycles do not guarantee a robust egg count, reproductive endocrinology relies on objective biomarkers to map an individual's remaining ovarian reserve. Clinical evaluation typically combines blood assays and high-resolution imaging to paint a comprehensive picture of both quantity and functional potential. These diagnostic tools have become standard protocols for those planning family-building timelines or investigating age-related fertility shifts.
The primary laboratory metric is the Anti-Müllerian Hormone (AMH) blood test, which can be performed on any day of the menstrual cycle because AMH levels remain relatively stable day-to-day. Paired with a baseline Day 3 Follicle-Stimulating Hormone (FSH) and estradiol draw, clinicians can assess how hard the pituitary is working to stimulate the ovaries. Concurrently, a transvaginal ultrasound is performed during the early follicular phase to conduct an Antral Follicle Count (AFC). This involves visually tallying the small, fluid-filled sacs (2–9 millimeters in diameter) visible in both ovaries, which directly reflects the pool of active, recruitment-ready follicles remaining in the biological queue.
Interpreting biomarkers across the fourth decade
Evaluating these metrics requires age-adjusted context, as what is considered a robust reserve at age 38 would be viewed as deficient at age 22. For individuals aged 30 to 34, a typical AMH level generally ranges between 2.1 and 4.2 ng/mL, though individual variation is vast due to genetics, lifestyle factors, and medical history. By the time a person crosses into the 35 to 39 bracket, normal AMH ranges shift downward to roughly 1.1 to 2.5 ng/mL. Antral follicle counts follow a similar downward progression, moving from average cohorts of 15 to 20 total follicles in early adulthood down to single digits or lower as the late thirties unfold.
It is vital to distinguish between quantitative reserve and qualitative potential. Diagnostic markers like AMH and AFC measure the *number* of eggs remaining, but they do not explicitly measure chromosomal normalcy or live-birth capability. While a 34-year-old and a 38-year-old might theoretically present with similar AMH values, the biological competence of the eggs, their ability to successfully fertilize, divide, and result in a healthy pregnancy, is heavily influenced by chronological age. This distinction underscores why clinical interpretations look at both the biological inventory and the timeline over which that inventory has aged.
Common pitfalls in daily time management
Overestimating future free time
People consistently misjudge how much time upcoming tasks will require, leading to overbooked schedules and chronic lateness. This cognitive bias results in committing to obligations without accounting for routine friction, unexpected interruptions, or basic biological needs like rest and meals. When schedules become overly packed, stress levels rise and the quality of execution declines significantly across every assigned duty.
Ignoring energy fluctuations
A major error in schedule planning is treating all hours of the day as having equal productive value. Human alertness and cognitive capacity fluctuate according to circadian rhythms, meaning peak mental performance occurs during specific windows rather than continuously. Attempting high-concentration analytical work during a natural afternoon energy trough produces subpar results and consumes far more time than necessary.
Multitasking across complex tasks
Attempting to handle multiple demanding projects simultaneously destroys efficiency through constant attentional switching. While individuals often feel more productive while juggling several items, cognitive processing bottlenecks prevent true parallel execution. Each switch between distinct workflows incurs a mental penalty that accumulates over hours, ultimately reducing total output and increasing error rates.
The impact of Micro-Transitions on productivity
Cognitive switching costs
Short interruptions between tasks often cause larger productivity losses than people realize. Even a brief glance at a notification breaks deep concentration, requiring several minutes to regain the previous level of focus. These micro-transitions disrupt working memory and create subtle mental fatigue that degrades performance long before the workday ends. The invisible friction of shifting attention between entirely different software applications or physical workspaces drains cognitive reserves without producing any tangible output.
Structuring buffer periods
Inserting short, unstructured pauses between major tasks provides the brain necessary recovery time. These intervals prevent the accumulation of cognitive fatigue and allow ideas to consolidate naturally before the next cognitive demand begins. Maintaining deliberate breathing room in a daily schedule transforms chaotic pacing into a sustainable rhythm that supports long-term consistency. Protecting these transitions ensures that energy levels remain relatively stable from morning until evening.
Frequently asked questions
What is the optimal duration for a focused work session?
Research tracked by productivity software analytics indicates that high-performing workers often maintain focus for approximately fifty minutes followed by a brief break. This pattern aligns with natural ultradian rhythms that govern human alertness and fatigue cycles throughout the day. Taking short pauses prevents cognitive exhaustion and sustains high attention levels across extended periods. Implementing structured intervals helps maintain consistent output without triggering burnout.