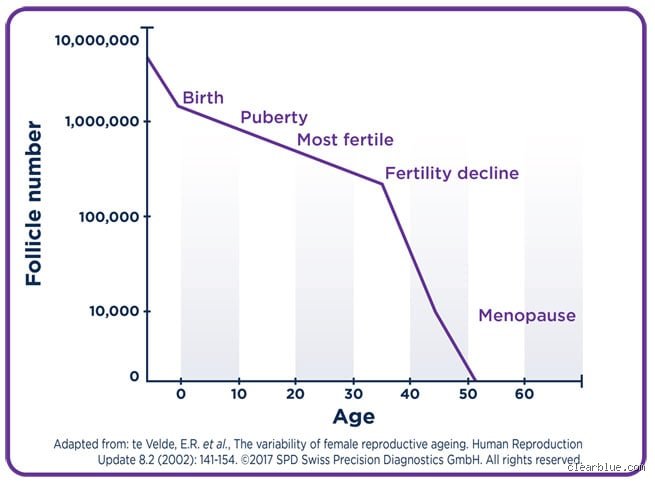
Understanding exactly what happens to the ovarian reserve at age 60 requires looking beyond simple arithmetic. The biology of female reproductive aging is not a steady, linear countdown; rather, it is a complex physiological process involving continuous follicular loss, hormonal shifts, and profound changes in both egg quantity and chromosomal integrity.
The baseline: Starting with millions
Unlike sperm, which are continuously generated throughout adult life via spermatogenesis, human oocytes (eggs) are formed entirely during fetal development. By approximately 20 weeks of gestation, a female fetus reaches her lifetime peak of roughly 6 to 7 million oocytes.
From that point forward, the biological clock is permanently set to attrition. Even before birth, millions of these immature eggs undergo a natural process of programmed cell death known as atresia. By the time a baby is born, her ovarian reserve has already dropped to roughly 1 to 2 million follicles.
This decline continues silently throughout childhood, long before reproductive hormones activate the menstrual cycle. By the onset of puberty—typically between ages 11 and 14, only about 300,000 to 500,000 eggs remain. Out of this entire pool, only about 400 to 500 will ever mature and be released during ovulation over a lifetime. The remaining 99.9% are lost through ongoing follicular recruitment and atresia.
The rate of decline across the decades
The depletion of the ovarian reserve does not occur at a uniform pace. Instead, it follows a biphasic curve that accelerates sharply in the late thirties:
| Life Stage | Approximate Remaining Egg Count | Key Physiological Dynamics |
|---|---|---|
| Fetal Peak (20 weeks) | 6,000,000 – 7,000,000 | Maximum lifetime oogenesis achieved in utero. |
| Birth | 1,000,000 – 2,000,000 | Rapid prenatal atresia reduces the initial pool by over 70%. |
| Puberty | 300,000 – 500,000 | Hypothalamic-pituitary-ovarian axis activates; ovulation begins. |
| Age 30 | ~100,000 – 150,000 | Steady monthly loss of roughly 1,000 immature follicles per cycle. |
| Age 37 | ~25,000 | Critical threshold; rate of follicular atresia more than doubles. |
| Age 51 (Average Menopause) | ~1,000 | Insufficient follicles remain to sustain cyclical estrogen production. |
| Age 60 | < 1,000 (Often near 0) | Postmenopausal state; residual follicles are largely non-viable. |
During the twenties and early thirties, a woman loses roughly 1,000 immature follicles each month, not through ovulation, which claims only one dominant follicle, but because cohorts of primordial follicles are continuously recruited to grow and subsequently die off when they do not receive adequate hormonal stimulation.
Around age 37, a well-documented biological inflection point occurs. When the reserve drops to roughly 25,000 follicles, the rate of follicular loss accelerates dramatically. By the time the average woman reaches menopause around age 51, her ovarian reserve has fallen below the critical threshold of roughly 1,000 follicles. At this point, there are simply too few responsive follicles left to produce the estrogen and progesterone required to trigger endometrial shedding, bringing menstrual cycles to a permanent halt.
The reality at Age 60: Quantity vs. Viability
Because the average age of natural menopause in Western populations is 51, with a normal clinical range spanning from 45 to 55, the vast majority of women at age 60 are roughly five to fifteen years postmenopausal. At this stage, two distinct biological realities define the state of the ovaries:
Near-Total Depletion of the Reserve: Histological studies of postmenopausal ovaries demonstrate that while the ovarian cortex does not instantly become completely devoid of primordial follicles the day menstruation stops, the residual pool continues to dwindle after menopause. By age 60, fewer than 1,000 quiescent follicles remain, and in many individuals, microscopic examination reveals virtually zero surviving oocytes.
Loss of Functional Responsiveness: Even when a few hundred primordial follicles persist at age 60, they are functionally dormant and resistant to gonadotropin stimulation. In a postmenopausal body, the pituitary gland secretes persistently high levels of Follicle-Stimulating Hormone (FSH) and Luteinizing Hormone (LH) in a futile attempt to stimulate ovarian activity. The surviving follicles lack the cellular machinery and receptor sensitivity to respond to these signals, meaning natural ovulation does not occur.
Why Egg quality matters more than Count
When discussing reproductive biology at age 60, counting remaining follicles tells only half the story. Equally critical is oocyte quality, specifically, the chromosomal integrity and mitochondrial energy capacity of the eggs.
Human eggs remain arrested in the prophase of Meiosis I from fetal life until just hours before ovulation. For a 60-year-old woman, any surviving oocyte has been suspended in cellular stasis for six decades. Over that span, the cohesin proteins that hold sister chromatids together gradually degrade, and oxidative stress accumulates within the ovarian microenvironment.
As a result, even in the late thirties and forties, well before menopause, the rate of aneuploidy (chromosomal abnormalities in the egg) rises exponentially:
At age 25, roughly 75% to 80% of a woman's eggs are chromosomally normal (euploid).
By age 40, the proportion of euploid eggs drops to approximately 35% to 40%.
By age 45, more than 85% to 90% of remaining eggs carry chromosomal abnormalities.
By age 60, virtually 100% of any residual oocytes exhibit severe chromosomal degradation and mitochondrial dysfunction, rendering them incapable of supporting healthy fertilization or embryonic development.
The endocrine shift of the Postmenopausal ovary
A common misconception is that once the egg supply drops below 1,000 and menopause occurs, the ovaries become completely inactive organs. While they cease producing estradiol and progesterone at reproductive levels, the postmenopausal ovary at age 60 remains an active endocrine tissue.
The ovarian stroma, the connective tissue framework surrounding the depleted follicles, continues to respond to elevated LH levels by secreting small but physiologically meaningful amounts of androgens, primarily testosterone and androstenedione. In peripheral tissues such as adipose tissue, skin, and muscle, an enzyme called aromatase converts these ovarian and adrenal androgens into estrone (E1E_1E1), a weaker form of estrogen that becomes the dominant circulating estrogen after menopause.
Understanding this transition clarifies why the depletion of the egg supply affects far more than fertility: the loss of follicular granulosa cells alters the entire hormonal architecture of the body, influencing bone density, cardiovascular health, metabolic regulation, and neurological function well into a woman's sixties and beyond.
The mechanics of the final countdown: How atresia reshapes the Reserve
While menopause marks the official end of menstrual cycles, the biological winding-down process, known as follicular atresia, is not a sudden cliff; it is a steady, lifelong attrition that accelerates sharply in the late thirties and forties. Understanding what happens to the remaining follicles at age 60 requires looking closely at how the ovarian microenvironment transforms after the reproductive window closes.
Throughout a woman's reproductive years, follicles are recruited in waves every month. Only one dominant follicle typically reaches maturity and ovulates, while dozens of others in that cohort undergo atresia, a programmed cellular degeneration. By the time a woman reaches menopause, on average around age 51 in the United States and Europe, the total follicle count has dropped below the critical threshold of roughly 1,000 primordial follicles. Without enough active follicles to produce consistent surges of estradiol and progesterone, the hypothalamic-pituitary-ovarian (HPO) axis shifts into a new equilibrium.
Between menopause and age 60, that remaining pool of approximately 1,000 follicles does not simply freeze in time. Instead, low-level, disorganized follicular recruitment continues for several years post-menopause. Because these aging follicles are largely unresponsive to the soaring levels of follicle-stimulating hormone (FSH) secreted by the pituitary gland, they fail to mature and instead undergo continuous atresia. By the time a woman celebrates her 60th birthday, histological studies of ovarian tissue show that the follicular reserve is either completely exhausted (zero follicles) or reduced to a microscopic handful of scattered, quiescent primordial follicles, often fewer than a few dozen across both ovaries.
Why Age 60 looks different for everyone
Although the biological trajectory points toward near-total depletion by age 60, individual variation remains significant. Two 60-year-old women can have markedly different cellular landscapes inside their ovaries depending on several key determinants:
Initial Ovarian Endowment: Before birth, at around 20 weeks of gestation, a female fetus possesses between 6 and 7 million oocytes. By birth, that number drops to 1 to 2 million. Women born at the higher end of this spectrum naturally retain a slightly larger residual pool decades later.
Timing of Menopause: A woman who experiences menopause at age 45 has already crossed the less-than-1,000-follicle threshold 15 years before turning 60, virtually guaranteeing complete depletion by her sixth decade. Conversely, a woman who enters menopause late, at age 55 or 56, is only four or five years post-menopause at age 60 and is much more likely to still harbor a small, detectable number of primordial follicles.
Genetic and Environmental Modulators: Specific genetic variants affecting DNA repair pathways (such as BRCA1, BRCA2, and MCM8/9) accelerate oocyte apoptosis, leading to earlier exhaustion. Lifestyle and medical exposures, most notably cigarette smoking, which introduces polycyclic aromatic hydrocarbons that directly destroy ovarian follicles, as well as chemotherapy or pelvic radiation, can deplete the reserve years ahead of schedule.
| Age Milestone | Approximate Follicle Count | Dominant Physiological State |
|---|---|---|
| Fetal Peak (20 weeks) | 6,000,000 – 7,000,000 | Rapid mitotic division and peak oocyte formation |
| Birth | 1,000,000 – 2,000,000 | Onset of lifelong atresia; oocytes arrested in prophase I |
| Puberty | 300,000 – 400,000 | Initiation of cyclic ovulation and monthly cohort recruitment |
| Age 37 | ~25,000 | Acceleration of follicular loss; noticeable decline in fertility |
| Menopause (~Age 51) | Less than 1,000 | Cessation of menses; sharp drop in ovarian estradiol |
| Age 60 | 0 to ~100 | Near-total or complete depletion; stromal dominance |
Can the Remaining eggs at 60 ever be used?
A common question among patients reading about residual follicles after menopause is whether those final few dozen eggs hold any reproductive potential. From both a cellular and clinical standpoint, the answer is no.
Even when rare primordial follicles persist in the ovarian cortex at age 60, they have been suspended in the dictyate stage of meiosis I for six decades. Over that span, the cohesin proteins that hold sister chromatids together degrade, mitochondrial DNA accumulates oxidative damage, and the surrounding granulosa cells lose their ability to support healthy oocyte maturation. Consequently, the rate of chromosomal aneuploidy in oocytes retrieved past age 45 already approaches 80% to 90%, and by age 60, spontaneous or assisted conception using a woman's own eggs is biologically unviable.
When pregnancies do occur in women in their late fifties or sixties, occasionally making headlines, they are achieved exclusively through in vitro fertilization (IVF) using donor oocytes from younger women, or through embryos that were cryopreserved decades earlier. In these cases, exogenous estrogen and progesterone are administered to prepare the endometrial lining of the uterus, which retains its capacity to carry a pregnancy long after the ovaries have retired.
What happens to the ovaries once the eggs are gone?
Reaching zero eggs does not mean the ovaries become inert or obsolete organs. At age 60, the ovaries undergo a distinct structural and functional shift rather than disappearing entirely.
Histologically, the ovarian cortex thins and becomes fibrotic, losing the fluid-filled antral follicles that give younger ovaries their plump, dynamic appearance on ultrasound. The organs shrink in volume, typically measuring less than 2 to 3 cubic centimeters, compared to 6 to 10 cubic centimeters during reproductive years.
Functionally, however, the ovarian stroma (the connective tissue framework of the ovary) remains metabolically active. Under the influence of chronically elevated luteinizing hormone (LH) from the pituitary gland, specialized stromal and hilar cells continue to synthesize androgens, primarily testosterone and androstenedione. Peripheral tissues, such as adipose tissue, skin, and muscle, then use the enzyme aromatase to convert a portion of these ovarian androgens into estrone, a weaker form of estrogen that becomes the primary circulating estrogen in postmenopausal women. This low-level hormonal output plays a continuing role in bone density maintenance, cardiovascular physiology, and metabolic health well into a woman's seventies and eighties.
Measuring Ovarian Reserve at 60: Why standard tests stop working
In younger women, clinicians estimate egg supply using Anti-Müllerian Hormone (AMH) blood tests and Antral Follicle Counts (AFC) via transvaginal ultrasound. At age 60, neither tool provides meaningful information about whether a handful of primordial follicles remain:
AMH Levels: AMH is secreted specifically by the granulosa cells of small growing (pre-antral and small antral) follicles, not by dormant primordial follicles. Because follicle growth has stalled by age 60, serum AMH drops to undetectable levels (typically below 0.01 ng/mL) several years before menopause and remains flat thereafter.
Ultrasound Imaging: Antral follicles measure 2 to 10 millimeters in diameter and are easily visible on ultrasound. Primordial follicles, by contrast, measure roughly 30 to 50 micrometers, far below the resolution of clinical imaging. A 60-year-old ovary appears smooth and solid on ultrasound regardless of whether it contains zero primordial follicles or fifty.
Knowing the exact microscopic egg count at age 60 is clinically unnecessary. By this stage of life, reproductive endocrinology shifts its focus entirely from follicular reserve to systemic hormonal balance, monitoring bone mineral density, cardiovascular risk factors, and menopausal symptom management as the body settles into its post-reproductive equilibrium.