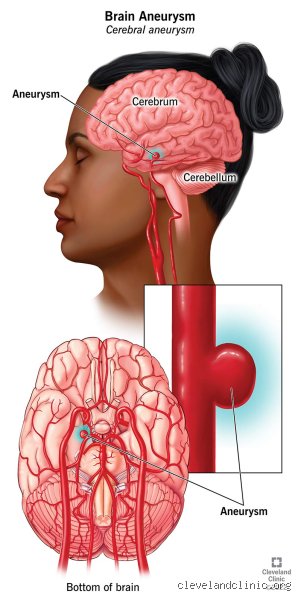
When people talk about a brain aneurysm bursting, they are usually talking about a ticking clock where every single second genuinely changes the math. If you're imagining a dramatic movie scene where someone clutches their head and drops instantly, that does happen sometimes, but it's often a much more chaotic, confusing slide into pain that catches everyone off guard.
To understand how long a person has, you have to look at what's actually happening inside the skull. An aneurysm is a weak, ballooning spot on a blood vessel wall—often shaped like a tiny, thin-walled berry sitting right at a fork in the arteries at the base of the brain. When that wall finally gives out, arterial blood starts pumping directly into the space surrounding the brain, a medical emergency known as a subarachnoid hemorrhage.
The immediate window—the first 24 hours, is the most brutal phase. Statistically, about a quarter of people who suffer a rupture don't survive this first day. Some pass away almost instantly from the sheer force and pressure of the initial bleed, which can cause catastrophic damage to vital brain structures or trigger a rapid buildup of intracranial pressure that cuts off blood flow entirely. Others lose consciousness and slip into a coma before anyone can call for help.
For the people who do survive that initial burst, the clock doesn't reset; it just shifts into a different gear. You aren't simply dealing with the mess of the first leak anymore. The body enters a high-risk window that stretches across the first two weeks, where the primary threats change day by day.
One of the biggest immediate dangers in the hours following a rupture is rebleeding. A freshly clotted aneurysm is notoriously fragile. If a person's blood pressure spikes, or even if they just strain too hard, that fragile clot can blow out. The risk of rebleeding is highest in the very first 24 to 48 hours, and a second bleed is dramatically more lethal than the first. This is why doctors treat a secured diagnosis like a five-alarm fire, moving patients as quickly as safely possible into procedures like surgical clipping or endovascular coiling to physically seal off the weak spot from the inside or outside.
Beyond the risk of a secondary bleed, the blood sitting in the subarachnoid space starts irritating the surrounding brain tissue and blood vessels. This triggers a secondary complication called vasospasm, which typically rears its head anywhere from three to fourteen days after the initial event. During a vasospasm, the large blood vessels in the brain suddenly and
The Critical Window: Immediate survival and Pre-Hospital realities
When a cerebral or aortic aneurysm ruptures, time ceases to be a mere abstraction and becomes an uncompromising currency. The primary question, "How long do you have?", defies a single, universal answer because the timeline depends heavily on whether the rupture is intracranial (a brain aneurysm leading to a subarachnoid hemorrhage) or extracranial (such as an abdominal aortic aneurysm). However, in both scenarios, the margin for survival is measured in minutes, hours, and days rather than weeks or months.
Statistically, approximately 15% of individuals suffering a ruptured brain aneurysm do not survive long enough to reach a hospital. They succumb within the first few minutes due to the catastrophic pressure wave and massive initial hemorrhage inside the skull. For those who do make it to an emergency department, the next milestone is the 24-hour mark. Roughly 25% of patients pass away within the first day, either from the primary bleed or from immediate secondary complications such as severe brain swelling, cardiac arrest, or rebleeding of the fragile, unclipped vessel.
Similarly, with an abdominal aortic aneurysm (AAA) rupture, the statistics are stark. Up to 80% to 90% of individuals with a ruptured AAA die before reaching medical attention or shortly after arrival, making it one of the most lethal surgical emergencies known to medicine. For those who survive the initial hemorrhage long enough to undergo emergency surgical repair, survival hinges entirely on the swiftness of intervention. Every minute that passes without blood flow restoration or bleeding control exponentially increases## The Critical Window: Understanding the Timeline of a Ruptured Aneurysm
When a cerebral aneurysm ruptures, it leads to a subarachnoid hemorrhage, bleeding into the space between the brain and the surrounding membrane. This is a catastrophic medical emergency where every minute dictates the margin between survival, permanent neurological disability, and mortality. Statistically, approximately 40% of people who experience a ruptured aneurysm do not survive the first 24 hours. Of those who reach the hospital alive, prompt medical intervention is the single most critical determinant of long-term outcomes.
The golden hours of Pre-Hospital care
The immediate aftermath of a rupture is characterized by a sudden, excruciating headache often described by patients as the "worst headache of their life" (frequently referred to as a thunderclap headache), accompanied by rapid loss of consciousness, nausea, vomiting, and neck stiffness.
In these critical moments, the time elapsed from the moment of rupture to the initiation of definitive neurosurgical or endovascular care is measured in minutes, not hours.
Minutes 0–60: The initial bleeding phase. The primary risk during this window is sudden cardiac or respiratory arrest due to intracranial pressure spikes or secondary brainstem compression. Immediate activation of emergency medical services (EMS) is vital. Paramedics stabilize airway, breathing, and circulation (the ABCs) and transport the patient directly to a comprehensive stroke center or a facility equipped with neurosurgical capabilities.
Hours 1–6: The diagnostic and stabilization window. Upon arrival, emergency physicians and neurologists work under immense time pressure to confirm the diagnosis and secure the ruptured blood vessel to prevent re-bleeding, which carries an even higher mortality rate than the initial rupture.
Diagnostic protocols in the emergency setting
Time is saved or lost during the diagnostic phase. Modern emergency departments utilize rapid, high-resolution imaging modalities to map the cerebral vasculature with pinpoint accuracy.
Non-Contrast Computed Tomography (CT) Scan: This is almost invariably the first imaging test performed. A CT scan can rapidly detect acute blood in the subarachnoid space with high sensitivity within the first 24 hours of symptom onset.
Computed Tomography Angiography (CTA): By injecting a contrast dye into the bloodstream, CTA allows physicians to visualize the exact location, size, and morphology of the aneurysm, guiding the surgical team on whether to pursue an endovascular or open surgical approach.
Digital Subtraction Angiography (DSA): Considered the gold standard for vascular mapping, DSA involves catheter-guided imaging through the femoral or radial artery to provide a real-time, dynamic view of blood flow within the brain's arterial network.
Lumbar Puncture (Spinal Tap): In cases where the CT scan is negative or equivocal despite a classic clinical presentation of a thunderclap headache, examining the cerebrospinal fluid for the presence of xanthochromia (yellowish discoloration from degraded blood breakdown products) confirms a subarachnoid hemorrhage.
Definitive treatment options: Securing the vessel
Once the diagnosis is confirmed and the aneurysm is located, the immediate priority shifts to preventing re-rupture. Re-bleeding typically occurs within the first 24 hours, most frequently in the first few hours, and carries a mortality rate exceeding 70%. Modern medicine relies on two primary techniques to secure the aneurysm:
1. Endovascular coiling (minimally invasive)
Endovascular coiling is performed from inside the blood vessel. A neurointerventional radiologist threads a microcatheter through the arterial system (usually starting from the groin or wrist) up into the cerebral circulation and directly into the sac of the aneurysm. Platinum coils are then deployed through the catheter into the aneurysm. These coils induce blood clotting (thrombosis) within the sac, permanently sealing it off from the main bloodstream and neutralizing the risk of further rupture. This method requires shorter recovery times and avoids opening the skull, making it the preferred first-line treatment for many anatomical locations.
2. Surgical clipping (open microsurgery)
For aneurysms with specific shapes, wide necks, or associated blood clots (hematomas) that require surgical evacuation, open microsurgical clipping remains the standard of care. A neurosurgeon performs a craniotomy (temporarily removing a section of the skull) to access the base of the aneurysm. A tiny, specialized metal clip is placed across the neck of the aneurysm, stopping blood flow into the sac while preserving normal blood flow through the parent artery. Once clipped, the aneurysm is permanently excluded from the circulatory system.
Navigating secondary complications: The days after
Surviving the initial rupture and securing the aneurysm is only the first battle. The subsequent days and weeks introduce secondary pathophysiological processes that require intensive neurological monitoring and critical care management:
Cerebral Vasospasm: Typically occurring between 4 to 14 days after the initial bleed, vasospasm involves the delayed narrowing of cerebral blood vessels in response to blood breakdown products in the subarachnoid space. This constriction can drastically reduce blood flow to regions of the brain, causing delayed ischemic strokes. Continuous transcranial Doppler monitoring and medications such as nimodipine are standard prophylactic measures.
Hydrocephalus: Blood in the subarachnoid spaces can block the normal absorption pathways of cerebrospinal fluid, leading to fluid accumulation within the brain's ventricles (hydrocephalus). This increases intracranial pressure and may require temporary external ventricular drainage (EVD) or the placement of a permanent shunt.
Hyponatremia: Electrolyte imbalances, particularly low sodium levels resulting from cerebral salt wasting syndrome, are common and require rigorous management to prevent secondary brain swelling.
Long-Term prognosis and Neuro-Rehabilitation
The journey following a ruptured aneurysm extends far beyond acute hospital discharge. The recovery trajectory depends heavily on the patient's age, overall health status, the initial World Federation of Neurosurgical Societies (WFNS) grade, and the promptness of intervention.
While some individuals make a full recovery and return to their pre-event lifestyle, many survivors experience long-term sequelae. These can include cognitive deficits (such as memory impairment, reduced processing speed, and executive dysfunction), emotional challenges (depression, anxiety, and post-traumatic stress disorder), and chronic fatigue.
Comprehensive neuro-rehabilitation, encompassing physical therapy, occupational therapy, speech therapy, and psychological counseling, matters a lot in maximizing functional independence and enhancing the quality of life for survivors and their families.
Understanding the rapid timeline and relentless progression of a ruptured aneurysm underscores the critical importance of recognizing the warning signs and seeking immediate, specialized emergency medical care without delay.