Yet, as the therapeutic landscape matures, a critical question persists among clinicians, researchers, and everyday seekers of mental wellness: Does CBT actually work?
The answer is rarely a simple binary. While decades of randomized controlled trials (RCTs) confirm its robust efficacy, a nuanced examination reveals that CBT is not a universal panacea. Its success depends heavily on the specific psychological target, the adherence of both practitioner and client, and the fundamental mechanics of how an individual processes thought and behavior.
The theoretical architecture: What is CBT?
To understand whether CBT works, one must first deconstruct what it is. Developed primarily by Dr. Aaron T. Beck in the 1960s, CBT emerged as a departure from traditional psychodynamic approaches that focused heavily on deep-seated childhood traumas and unconscious drives. Instead, Beck observed that his depressed patients experienced streams of negative thoughts that popped up automatically. Crucially, these automatic thoughts heavily influenced their moods and behaviors.
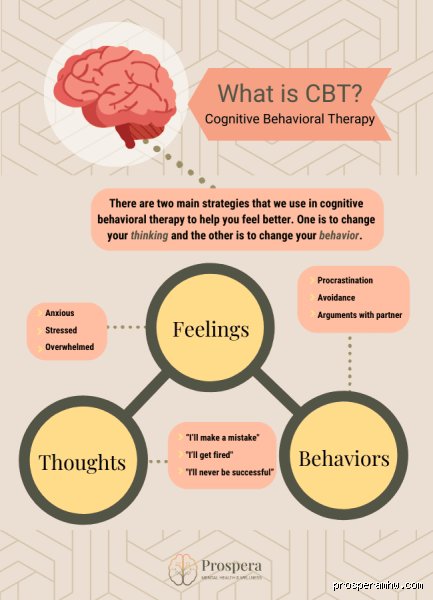
The core premise of CBT rests upon the cognitive model, which asserts that our thoughts, feelings, and behaviors do not exist in isolation; they are deeply interconnected in a dynamic, reciprocal feedback loop.
Situations trigger events in our external environment.
Thoughts (specifically automatic cognitive appraisals) interpret those situations, often skewed by cognitive distortions.
Emotions arise directly from those interpretations, rather than from the situation itself.
Behaviors follow as a reaction to those emotions, which in turn reinforce the original thoughts, completing the loop.
For example, imagine two individuals walking down a hallway and passing a coworker who looks straight ahead and does not say hello.
Person A thinks: "They must be angry at me because of something I did." This thought triggers feelings of anxiety and rejection, leading Person A to avoid the coworker in the future.
Person B thinks: "They must be preoccupied or didn't notice me." This thought produces neutral or unbothered feelings, leading Person B to wave cheerfully next time.
The objective of CBT is not positive thinking for the sake of forced optimism, but rather cognitive flexibility, the ability to identify, evaluate, and modify dysfunctional thinking patterns into more realistic, balanced perspectives, while simultaneously modifying maladaptive behavioral habits through deliberate action.
The empirical evidence: What do the data say?
In science-based medicine, "Does it work?" is answered through rigorous accumulation of quantitative data, meta-analyses, and comparative outcome studies. By these metrics, CBT is arguably the most extensively researched form of psychotherapy in history.
1. Depression and anxiety Disorders
For unipolar depression, hundreds of clinical trials indicate that CBT is just as effective as pharmacotherapy (such as Selective Serotonin Reuptake Inhibitors, or SSRIs) in the acute phase of treatment. Crucially, longitudinal studies show that patients who successfully complete a course of CBT often experience lower relapse rates post-treatment compared to those treated with medication alone. This is widely attributed to the "skill-acquisition" model of CBT: patients learn active psychological tools that they can deploy independently long after formal therapy sessions conclude.
In anxiety disorders, including panic disorder, social anxiety, and phobias, CBT often incorporates exposure therapy, a behavioral component where clients systematically and safely confront feared stimuli. The data here are remarkably strong; structured behavioral exposure rewires fear conditioning through the neurological mechanism of extinction learning, frequently yielding rapid and sustained symptom reduction.
2. Effect sizes and comparative efficacy
When statisticians calculate effect sizes (Cohen’s ddd) comparing CBT to treatment-as-usual or waitlist controls across hundreds of trials, CBT consistently demonstrates moderate-to-large effect sizes, typically ranging from 0.50.50.5 to 0.80.80.8 or higher depending on the condition.
However, comparative effectiveness research, such as studies contrasting CBT with other manualized psychotherapies like Acceptance and Commitment Therapy (ACT), psychodynamic therapy, or interpersonal therapy (IPT), often reveals a nuanced reality known in clinical psychology as the Dodo Bird Verdict: most major psychotherapies produce comparable overall benefits. While CBT excels at structured symptom reduction and skill building, its superiority over other established modalities is not always absolute across every single mental health condition.
Core mechanisms of change: How CBT creates shifts
To evaluate CBT's effectiveness, researchers look beyond mere symptom checklists to investigate how and why change occurs within the human mind. Modern neuroimaging and psychological research highlight several core mechanisms:
Cognitive Restructuring: The intentional practice of examining evidence for and against automatic negative thoughts. When practiced consistently, this strengthens prefrontal cortical control over hyperactive limbic responses (such as threat detection in the amygdala).
Behavioral Activation: In depressive states, individuals tend to withdraw from rewarding activities, which starves the brain of positive reinforcement and worsens low mood. Behavioral activation systematically re-engages the individual in meaningful, value-driven actions, effectively breaking the depressive inertia.
Metacognitive Awareness: Developing the capacity to view thoughts as "mental events" or hypotheses rather than absolute facts ("I am having the thought that I am a failure," versus "I am a failure"). This creates essential psychological distance between the self and transient mental content.
Limitations and where CBT falls short
Despite its impressive empirical track record, an objective look at CBT reveals notable boundaries and limitations. Understanding these constraints is vital for anyone considering whether the modality is appropriate for their specific needs:
High Structure vs. Complex Trauma: CBT is inherently present-focused, highly structured, and goal-oriented. While this makes it exceptionally effective for acute phobias, panic, and mild-to-moderate depression, it can sometimes feel mechanical or dismissive to individuals grappling with complex trauma, chronic developmental neglect, or deeply entrenched personality organization issues. These conditions often require longer-term, relational, or bottom-up somatic approaches.
The Importance of Homework and Effort: CBT is not a passive treatment. Unlike medical interventions where a patient simply takes a pill, CBT requires active client participation, workbook exercises, thought records, and behavioral experiments between sessions. For individuals suffering from severe clinical fatigue or profound motivational deficits, completing CBT homework can present a formidable barrier.
Therapist Variance: Because CBT relies heavily on manualized protocols, poor implementation by inadequately trained practitioners can reduce the therapy to a rigid, checklist-driven exercise that fails to build the vital therapeutic alliance necessary for deep psychological healing.
Long-Term efficacy and relapse prevention: Beyond the initial symptom reduction
While the initial phases of Cognitive Behavioral Therapy (CBT) focus heavily on acute symptom relief, such as dampening panic responses, interrupting depressive rumination, or managing immediate avoidance behaviors, the true hallmark of CBT's effectiveness lies in its long-term impact. Critics and skeptics often ask whether the gains made during a standard 12-to-16-week protocol persist after therapy concludes, or if CBT merely acts as a temporary psychological bandage.
Longitudinal studies tracking patients across various diagnostic categories, ranging from generalized anxiety disorder (GAD) to major depressive disorder (MDD) and obsessive-compulsive disorder (OCD), reveal a reassuring trend. Unlike pharmacological interventions, where discontinuation frequently precipitates a high rate of symptom relapse, CBT equips patients with a meta-cognitive skillset. This skillset is often termed "cognitive immunization."
When individuals learn to identify their own cognitive distortions, systematically test their underlying assumptions, and engage in regular behavioral experiments, they essentially become their own therapists. The neural pathways reinforced through repeated cognitive restructuring and exposure exercises create enduring neuroplastic changes. Functional neuroimaging studies demonstrate that successful CBT alters activation patterns in the prefrontal cortex and the amygdala, strengthening top-down emotional regulation. Consequently, patients who have completed CBT show significantly lower relapse rates over two-to-five-year follow-up periods compared to those treated with medication alone, and often comparable or superior rates when compared to continuation pharmacotherapy.
Tailoring CBT for Complex presentations and comorbidities
Standard CBT protocols were historically designed and tested on patients presenting with single, isolated diagnoses in tightly controlled clinical trials. However, real-world clinical practice rarely presents such neat, textbook cases. Comorbidity, the presence of two or more disorders concurrently, is the rule rather than the exception. A patient presenting with social anxiety disorder may simultaneously struggle with dysthymia, substance use, or chronic pain.
To address this complexity, contemporary CBT has evolved through modular frameworks and transdiagnostic approaches. The Unified Protocol for Transdiagnostic Treatment of Emotional Disorders, for instance, recognizes that many emotional disorders share underlying mechanisms, such as high neuroticism and a tendency to engage in emotion regulation through avoidance. Instead of treating anxiety and depression as entirely separate entities, a transdiagnostic CBT approach targets core processes:
Increasing present-focused emotion awareness
Changing maladaptive emotion appraisal processes
Preventing emotional avoidance
Facilitating action tendencies associated with adaptive emotional experiences
For individuals with complex trauma or personality-related difficulties, standard CBT protocols are frequently augmented. Interventions such as Trauma-Focused CBT (TF-CBT) or Dialectical Behavior Therapy (DBT), which emerged from a CBT lineage, integrate mindfulness, acceptance, and distress tolerance strategies. This ensures that CBT remains flexible, rigorous, and deeply responsive to the intricate realities of human psychological suffering.
The therapeutic alliance: The catalyst for Cognitive change
It is a common misconception that CBT is a cold, mechanical, and overly intellectualized treatment consisting merely of worksheets, thought logs, and automated exercises. In reality, the efficacy of CBT is deeply contingent upon the quality of the therapeutic alliance, the collaborative working relationship between the therapist and the client.
CBT is explicitly designed as a collaborative empiricism. The therapist and client form a scientific team, treating the client's thoughts not as absolute facts, but as working hypotheses to be tested collaboratively. This cooperative stance fosters a sense of empowerment and safety, which is particularly vital when asking patients to confront deeply feared situations through exposure therapy.
A skilled CBT therapist balances technical competence with high levels of empathy, warmth, and genuine attunement. When clients feel deeply understood rather than judged or cross-examined, their defensive resistance lowers, enabling them to engage more courageously with the rigorous cognitive and behavioral challenges that drive real therapeutic transformation.
Limitations, nuances, and When CBT might fall short
An objective evaluation of CBT requires acknowledging its boundaries and limitations. While the empirical support for CBT is vast, it is not a universal panacea. There are specific contexts and populations where standard CBT may prove insufficient or require substantial modification:
Severe Neurodevelopmental or Cognitive Impairments: CBT relies heavily on metacognition, self-reflection, and abstract reasoning. For individuals with severe intellectual disabilities, advanced dementia, or active, florid psychosis where reality testing is profoundly impaired, traditional cognitive restructuring is difficult to implement.
Systemic and Environmental Stressors: CBT focuses primarily on internal cognitive and behavioral loops. While it acknowledges external realities, it cannot solve systemic poverty, chronic discrimination, domestic abuse, or unsafe living environments. In such cases, while CBT can help manage the emotional toll of these stressors, it must be paired with macro-level structural support and social interventions.
Client Preference and Fit: Some individuals find the structured, goal-oriented, and homework-heavy nature of CBT to be overly rigid. Patients seeking deep existential exploration, long-term psychodynamic uncovering of unconscious drives, or unstructured emotional processing may resonate more strongly with humanistic, psychodynamic, or experiential modalities.
Recognizing these nuances does not diminish CBT's value; rather, it highlights the importance of clinical wisdom in matching the right treatment modality to the unique profile, history, and preferences of the individual.
The future of CBT: Digital Health, AI augmentation, and personalization
As mental healthcare enters a new technological era, CBT is undergoing a rapid digital transformation. Computerized CBT (cCBT) and mobile health applications have made evidence-based cognitive restructuring tools accessible to broader populations, bypassing traditional geographical and financial barriers to care. Randomized controlled trials on structured cCBT platforms demonstrate significant reductions in mild-to-moderate anxiety and depression symptoms, validating digital modalities as effective first-line interventions or adjuncts to human-led therapy.
Simultaneously, researchers are exploring how machine learning and artificial intelligence can enhance personalized CBT. By analyzing biometric data, speech patterns, and session transcripts, predictive models can help clinicians identify which specific CBT components, behavioral activation, cognitive reframing, or exposure, are most likely to yield optimal outcomes for a specific patient profile. This moves clinical practice away from a trial-and-error approach toward precision mental health.
Does CBT therapy really work? The weight of decades of rigorous psychological science answers with an emphatic yes. It works because it is pragmatic, transparent, and grounded in the fundamental human capacity to examine our own minds, challenge our fears, and author new behavioral patterns. While no single therapy can solve every human struggle, CBT remains one of our most powerful, adaptable, and scientifically validated tools for fostering lasting psychological resilience.