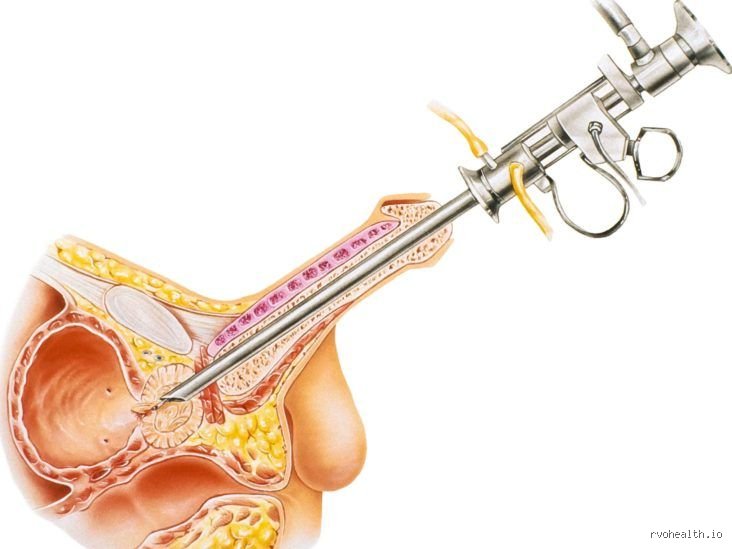
Historical milestones and the evolution of prostate surgery
The journey of understanding whether humans can survive without a prostate is rooted in decades of surgical innovation. For centuries, diseases of the prostate were viewed as a near-certain sentence due to severe hemorrhage and infection risks.
The dawn of radical procedures in Baltimore
The modern era of prostate surgery took shape at Johns Hopkins Hospital in Baltimore, Maryland. In 1904, pioneer surgeon Dr. Hugh Hampton Young performed the first successful radical perineal prostatectomy. Dr. Young’s meticulous anatomical approach proved that the prostate could be entirely excised without causing immediate mortality, laying the groundwork for modern oncology and urological surgery.
The laparoscopic and robotic revolution
For decades, open surgery remained grueling, involving long recovery times and high risks of incontinence. This paradigm shifted dramatically in 2000, when the FDA cleared the da Vinci surgical system for clinical use. Pioneering urologists began utilizing robotic-assisted laparoscopic radical prostatectomy, drastically minimizing blood loss and transforming patient recovery windows. Think of removing a malfunctioning prostate with modern robotic precision like replacing a faulty fuel injector in a high-performance engine: the core machinery of the vehicle keeps running, but the system is expertly optimized to prevent catastrophic failure down the road.
Anatomy and physiological Function: How the body operates Post-Surgery
To understand how a human thrives post-prostatectomy, one must examine the precise architecture of the pelvic region and how neighboring organs compensate.
The structural blueprint of the pelvis
The prostate sits directly beneath the bladder, wrapping completely around the urethra—the tube responsible for carrying urine out of the body. It is flanked by the seminal vesicles and dense bundles of nerves responsible for urinary sphincteric control and erectile function.
Urinary tract reconnection and Bladder dynamics
When a surgeon performs a radical prostatectomy, the entire prostate gland and adjacent seminal vesicles are removed. To restore continuity, the surgeon directly stitches the neck of the bladder down to the remaining urethra—a delicate maneuver known as vesicourethral anastomosis.
The Plumbing Redirection: Mechanically, this is comparable to cutting out a clogged segment of a kitchen pipe and coupling the upper PVC line directly to the lower drainpipe. Water flow continues, though the surrounding muscle valves require time to regain tension.
The Cellular Adaptation: Over ensuing months, the urinary sphincter muscles adapt to compensate for the missing tissue, gradually restoring baseline continence for the vast majority of patients.
Hormonal preservation and endocrine balance
Unlike the thyroid or adrenal glands, the prostate does not manufacture systemic hormones. Testosterone production continues uninterrupted because the testicles remain untouched, ensuring that secondary sex characteristics, muscle mass regulation, and metabolic baselines remain active.
While the clinical reality is straightforward, a human male can absolutely survive without a prostate, the physiological and psychosocial ripple effects of a radical prostatectomy require careful, ongoing management. The human prostate is not a life-sustaining organ like the heart, liver, or kidneys; it does not filter metabolic waste, synthesize vital systemic hormones, or maintain electrolyte balance. However, its anatomical position at the nexus of the urinary and reproductive tracts means its removal fundamentally alters two core aspects of quality of life: urinary continence and sexual function.
Navigating life after a prostatectomy requires understanding how the body adapts mechanically, neurogenic recovery, and the therapeutic strategies available to restore post-surgical quality of life.
Mechanical and anatomical adaptations: Urinary Function
The prostate encircles the urethra just below the bladder neck, functioning as part of the muscular valve mechanism that maintains urinary continence. When the prostate is excised, typically along with the seminal vesicles, the bladder neck must be surgically reconnected directly to the membranous urethra (a step known as vesicourethral anastomosis).
This reconstruction fundamentally alters urinary mechanics:
Sphincter Reliance: Prior to surgery, continence relies on both an internal (involuntary) sphincter at the bladder neck and an external (voluntary) sphincter below the prostate. Surgical removal leaves the external urethral sphincter as the primary mechanism preventing urine leakage.
Stress Urinary Incontinence (SUI): Because the external sphincter is subjected to sudden stretch and operative trauma, most patients experience temporary stress incontinence, leakage triggered by coughing, laughing, lifting, or sudden movements.
Recovery Timeline: For the majority of men, urinary control improves steadily over 3 to 12 months as local inflammation resolves and surrounding tissues heal.
Rehabilitation & therapeutic interventions
To accelerate bladder control, post-prostatectomy rehabilitation emphasizes targeted neuromuscular training:
Pelvic Floor Physical Therapy (Kegel Exercises): Progressive resistance and biofeedback training strengthen the levator ani and striated urethral sphincter muscles to compensate for the loss of the internal sphincter.
Pharmacotherapy: Anticholinergic medications or beta-3 adrenergic agonists may be prescribed if bladder spasms or urge incontinence co-occur alongside stress leakage.
Surgical Solutions for Persistent Incontinence: If significant incontinence persists past the 12-to-18-month mark, minimally invasive procedures, such as male synthetic slings or the implantation of an Artificial Urinary Sphincter (AUS), can effectively restore total bladder control.
Reproductive & sexual health after removal
The primary biological role of the prostate gland is the secretion of an alkaline fluid that constitutes approximately 30% of semen, providing nourishment and a transport medium for sperm. Consequently, its complete removal brings immediate and permanent structural shifts to reproductive biology.
[ Testes ] ------------(Sperm)------------\
|
(Vasa Deferentia) [Surgical Ligation]
|
[ Bladder ] ---> [ Vesicourethral Anastomosis ] <--- (Urethra) ---> (Dry Ejaculation)
Permanent infertility and Dry Orgasm
Because radical prostatectomy involves transecting and ligating the vasa deferentia and removing the seminal vesicles, sperm can no longer mix with seminal fluid or exit the body.
Infertility: Surgical removal results in total, irreversible anatomical infertility. Men desiring future biological children must pursue pre-operative sperm cryopreservation (sperm banking) or post-operative testicular sperm extraction (TESE) combined with in vitro fertilization (IVF).
Anorgasmic vs. Dry Orgasm: Climactic sensation is driven by neurological reflexes distinct from fluid ejection. Patients can still achieve sexual sensation and orgasm, but it will be entirely "dry" (without ejaculate release).
Erectile dynamics & Penile Rehabilitation
The cavernous nerves responsible for triggering erections travel along the outer surface of the prostate gland in extremely thin, delicate neurovascular bundles. Depending on the extent and location of any underlying disease (such as localized prostate cancer), surgeons employ nerve-sparing techniques to preserve these pathways.
Even when nerves are preserved, neuropraxia (temporary nerve stunning due to surgical traction and edema) causes temporary erectile dysfunction. Recovery is gradual, often requiring 12 to 24 months for nerve signal transmission to return.
Post-Surgery Timeline
[ 0-3 Months ] ------> [ 3-12 Months ] ------> [ 12-24 Months ]
Neuropraxia / ED Initial Nerve Recovery Maximum Function Restored
Pelvic Rehab Starts Oral PDE5 Inhibitors Implants (if refractory)
Modern erectile rehabilitation protocols focus on maintaining tissue oxygenation within the corpora cavernosa to prevent fibrosis during the recovery phase:
| Rehabilitation Modality | Mechanism of Action | Clinical Application |
|---|---|---|
| PDE5 Inhibitors (e.g., Tadalafil, Sildenafil) | Boosts nitric oxide signaling to promote smooth muscle relaxation and cavernous blood flow. | Daily low-dose or on-demand therapy as nerves regain responsiveness. |
| Vacuum Erectile Devices (VED) | Creates negative mechanical pressure to draw oxygenated arterial blood into the penile shafts. | Used daily or prior to intercourse to preserve tissue elasticity. |
| Intracavernosal Injections (ICI) | Directly delivers vasodilators (e.g., Alprostadil/Trimix) bypasses damaged autonomic nerves. | Highly effective short-term option during neuropraxia recovery. |
| Penile Prostheses | Inflatable or semi-rigid rods surgically placed within the erectile chambers. | Definitive treatment for refractory erectile dysfunction post-rehabilitation. |
Long-Term monitoring and health outcomes
Living without a prostate does not shorten life expectancy; on the contrary, when performed to eliminate localized malignancy, the procedure significantly improves long-term survival rates. However, long-term post-operative care centers on clinical surveillance.
In patients who have undergone radical prostatectomy for cancer, Prostate-Specific Antigen (PSA) serves as an ultra-sensitive biomarker for disease surveillance. Because the prostate is the primary source of PSA in the human body, serum levels should drop to an undetectable level (typically <0.1 ng/mL<0.1 ext{ ng/mL}<0.1 ng/mL) within several weeks of complete surgical excision. Periodic blood testing monitors for biochemical recurrence, allowing clinicians to intervene early with secondary targeted therapies if microscopic cellular remnants persist.
Human life without a prostate is not only entirely viable, but with modern nerve-sparing surgical approaches, structured pelvic rehabilitation, and multimodal therapies, patients reliably return to active, fulfilling, and healthy lives.
To explore specific post-operative care and recovery protocols: