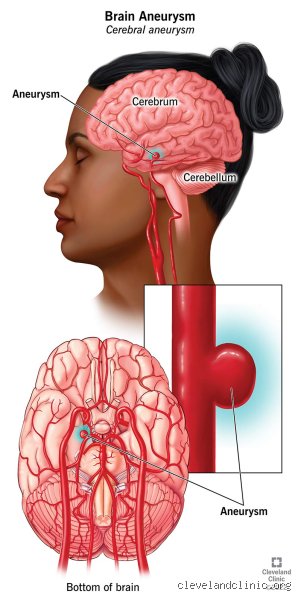
An intracranial or aortic aneurysm rupture represents one of the most critical medical emergencies in vascular neurology and cardiovascular medicine. When a weakened, dilated portion of an arterial wall gives way under hemodynamic stress, arterial blood surges into the surrounding space—whether into the subarachnoid space surrounding the brain or into the thoracic and abdominal cavities. In the immediate aftermath of such a catastrophic event, a fundamental physiological question arises: Can a ruptured aneurysm heal on its own?
To answer this question accurately requires a careful distinction between spontaneous biological repair (such as local blood clot formation) and genuine anatomical and clinical healing. While the body possesses powerful vascular repair mechanisms designed to arrest active bleeding, the structural reality of an arterial aneurysm means that spontaneous biological clot formation almost never equals a true cure. Understanding why requires a deep dive into vascular anatomy, hemodynamics, arterial wall architecture, and the cascade of physiological events that occur when an aneurysm breaches.
The Anatomy of an Aneurysm: Why Arteries Bulge and Burst
To understand how an aneurysm behaves after rupturing, one must first examine the architecture of the normal arterial wall and how it becomes structurally compromised.
A healthy artery consists of three distinct layers:
Tunica Intima: The innermost layer, lined with endothelial cells that provide a smooth surface for blood flow and actively regulate vascular tone and anti-clotting mechanisms.
Tunica Media: The middle layer, composed primarily of smooth muscle cells, elastic fibers, and collagen. This layer provides the structural integrity and resilience needed to absorb the high-pressure wave generated by each heartbeat.
Tunica Adventitia: The outermost connective tissue layer, rich in collagen, which anchors the blood vessel to surrounding tissues and provides external structural support.
In a saccular ("berry") aneurysm—the most common shape found in brain arteries—a local defect or degeneration in the tunica media and internal elastic lamina allows the inner vessel layers to bulge outward under high arterial pressure. Over time, the wall of this expanding outpouching becomes progressively thinner, weaker, and more fragile, consisting of little more than degraded fibrous tissue with virtually no muscular layer remaining.
When the wall stress exceeds the tensile strength of this compromised tissue, the aneurysm ruptures. In intracranial aneurysms, this sends high-pressure arterial blood into the subarachnoid space (causing a subarachnoid hemorrhage or SAH). In thoracic or abdominal aortic aneurysms, rupture leads to massive internal bleeding into the retroperitoneal or pleural cavities.
The Immediate Response: Spontaneous Hemostasis and Clotting
When an aneurysm wall breaches, the human body does not remain passive. An immediate physiological defense system—known as hemostasis—is triggered in an effort to prevent fatal exsanguination.
1. Vascular Spasm and Hemodynamic Drop
Immediately following rupture, the violent jet of extravasated blood and the release of potent vasoactive substances (such as endothelin-1, thromboxane A2, and hemoglobin breakdown products) cause local arterial vasospasm. The feeding blood vessels constrict dramatically to slow the velocity and volume of blood rushing toward the site of the breach. Simultaneously, if the rupture is intracranial, the sudden influx of blood into the closed cranial vault rapidly elevates intracranial pressure (ICP). As ICP rises toward the level of mean arterial pressure (MAP), the net pressure gradient across the aneurysm wall temporarily decreases, reducing active bleeding.
2. Platelet Plug Formation
Exposure of subendothelial collagen and tissue factor at the rupture site instantly recruits blood platelets. Platelets adhere to the damaged tissue via von Willebrand factor, undergo activation, and aggregate together to form a primary platelet plug over the tear in the aneurysm wall.
3. The Coagulation Cascade and Fibrin Mesh
Simultaneously, the extrinsic pathway of the coagulation cascade is triggered by exposed tissue factor. Prothrombin is converted to thrombin, which rapidly cleaves fibrinogen into insoluble fibrin strands. This fibrin mesh weaves through and reinforces the platelet plug, stabilizing a blood clot (thrombus) directly over the site of the rupture.
Clot Formation vs. True Healing: The Crucial Distinction
This initial clotting process can, in many cases, temporarily seal the breach in the aneurysm wall and stop active bleeding. To a layperson, this might look like the body "healing" the aneurysm. However, in vascular medicine, a temporary thrombus is fundamentally different from structural healing.
┌───────────────────────────────────────────────────────────┐
│ Aneurysm Rupture │
└─────────────────────────────┬─────────────────────────────┘
 │
 ┌──────────────┴──────────────┐
 ▼ ▼
 Spontaneous Hemostasis Structural Defect
 • Platelet aggregation • Degraded elastic lamina
 • Fibrin mesh formation • Absent smooth muscle
 • Temporary blood clot • Permanent wall weakness
 │ │
 ▼ ▼
 Temporary Bleeding Stop EXTREME RISK:
 (Does NOT equal healing) RE-RUPTURE
True healing of a blood vessel requires re-endothelialization and structural wall reconstruction—specifically, the formation of organized fibrous tissue lined by healthy endothelial cells that can withstand systemic systolic blood pressures (typically 120 mmHg or higher, and significantly higher during exertion or stress).
Because an aneurysm lacks a normal tunica media and possesses abnormal extracellular matrix architecture, the body rarely achieves stable, long-term tissue remodeling over the rupture site. Instead, the newly formed clot remains fragile, unstable, and constantly exposed to high-pressure arterial pulsations.
Why Ruptured Aneurysms Fail to Heal on Their Own
There are several biomechanical and biological factors that prevent a ruptured aneurysm from undergoing complete, self-directed healing:
Relentless Hemodynamic Pulsations: The human heart beats roughly 60 to 100 times per minute, sending a relentless hydraulic shockwave through the arterial tree. A fresh, soft blood clot sealing a ruptured aneurysm wall is continuously buffeted by these pressure waves. Without surgical or endovascular reinforcement, the clot frequently degrades or shifts under this mechanical force.
Endogenous Fibrinolysis: The body possesses a natural enzymatic process called fibrinolysis, primarily driven by plasmin, designed to dissolve blood clots over time so that blood vessels remain open. Unfortunately, as the body’s natural system begins to break down the temporary clot sealing the aneurysm, the weak underlying tissue defect is re-exposed.
Absence of Regenerative Wall Architecture: Healthy wound healing elsewhere in the body relies on robust connective tissue and surrounding capillary blood supply. The wall of a cerebral or aortic aneurysm is chronically hypoxic, inflamed, and structurally degenerate. Smooth muscle cells—which normally produce collagen and structural matrix—are largely absent or apoptotic within the aneurysm dome.
Because of these limitations, an untreated, untreated ruptured aneurysm does not undergo safe resolution. Instead, it enters a volatile, high-risk state characterized by a devastating clinical threat: re-rupture.
The Menace of Re-rupture
The single greatest danger of assuming a ruptured aneurysm will "heal itself" is the extremely high incidence of early re-bleeding. In subarachnoid hemorrhage caused by cerebral aneurysms, the risk of re-rupture is highest within the first 24 hours following the initial event (peaking within the first 6 to 12 hours).
A secondary rupture carries a mortality rate approaching 50% to 70%, and surviving patients face a drastically heightened risk of severe, irreversible neurological damage compared to the initial bleeding event. This stark statistical reality is why modern neurosurgical and vascular guidelines treat any suspected or confirmed aneurysm rupture as a maximum-priority emergency requiring immediate hospital admission and definitive surgical or endovascular repair.
Rare Exceptions: Spontaneous Thrombosis
Medical literature does record rare instances where an aneurysm appears to undergo spontaneous complete thrombosis—a phenomenon where the entire body of the aneurysm fills with a solid blood clot and effectively closes itself off from circulation.
Spontaneous thrombosis occurs most frequently in giant aneurysms (those greater than 25 mm in diameter) or in aneurysms with narrow necks and turbulent internal blood flow patterns. In these specific anatomical configurations, blood stagnates within the large aneurysmal sac, favoring extensive intravascular coagulation.
However, even when spontaneous thrombosis occurs, it cannot be relied upon as a safe or permanent cure for several key reasons:
Incomplete Obliteration: In many cases, dynamic angiographic studies reveal that what appears to be a fully thrombosed aneurysm actually retains a small, persistent "channel" or neck fragment of active blood flow. This residual lumen remains under arterial pressure and can rupture again.
Recanalization: Over weeks, months, or years, the body's natural inflammatory and angiogenic responses can dissolve or penetrate the internal thrombus, opening new channels for blood flow (recanalization) and restoring the threat of rupture.
Mass Effect: A thrombosed giant aneurysm does not shrink immediately. The large, hard clot continues to exert pressure on adjacent neurological or vascular structures, causing persistent neurological deficits, cranial nerve palsies, or seizures.
Summary of Part 1
While the human body responds to an arterial rupture with immediate biological countermeasures—vasospasm, platelet plug formation, and fibrin clotting—these mechanisms represent temporary emergency containment rather than true anatomical healing. The extreme mechanical forces of arterial blood pressure, combined with the underlying structural degradation of the vascular wall, make self-healing extraordinarily rare and unpredictable.
Relying on natural healing after an aneurysm rupture carries a devastatingly high risk of early re-rupture, disability, and death. Modern medicine therefore relies on rapid diagnostic imaging and definitive interventions—such as microvascular clipping or endovascular coiling—to secure the vessel.
(Continued in Part 2: Clinical Evaluation, Surgical and Endovascular Interventions, Acute Complications, and Long-Term Rehabilitation).
It looks like your prompt cut off or was a bit unclear regarding what topic or content you want the rest of the article to cover! Could you please share a bit more context or the preceding text so I can finish writing the remaining sections for you?