The hidden toll: Unmasking the true magnitude of pandemic mortality
The illusion of official numbers
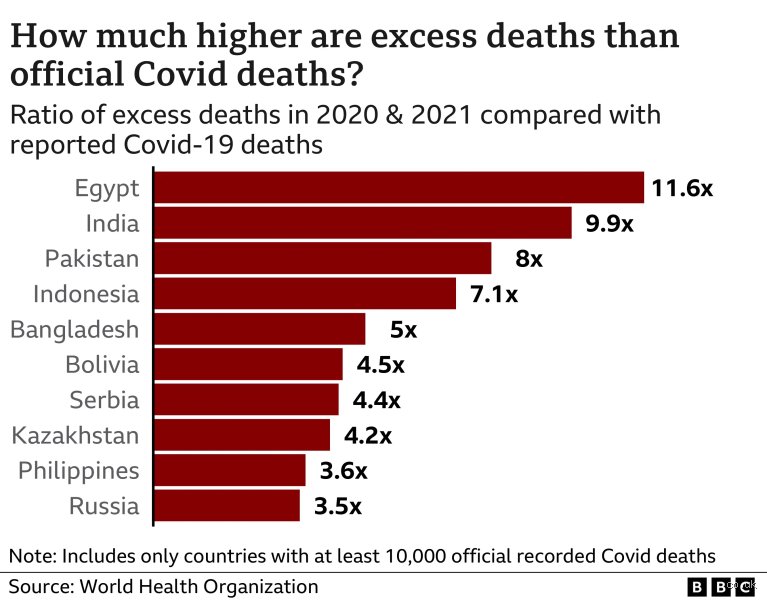
At first glance, government-reported figures offered a concrete metric. Countries with advanced diagnostic capabilities, robust electronic health records, and centralized reporting systems could track positive polymerase chain reaction (PCR) tests linked to subsequent deaths with reasonable precision. However, even in wealthy nations, the criteria for what constituted a "COVID-19 death" shifted over time. Did the patient die of the virus, or with the virus? Was a terminal cancer patient who contracted the virus in a hospice counted? Conversely, in many low- and middle-income countries, robust testing was an unreachable luxury. Millions of people died at home without ever seeing a doctor, let alone receiving a nasal swab. In rural expanses across South Asia, sub-Saharan Africa, and parts of Latin America, death registration systems are historically incomplete; entire lifetimes pass, and generations end, without formal vital statistics recording their entry or exit.
Consequently, official numbers served as a severe undercount. They captured a snapshot shaped by administrative capacity rather than biological reality. Governments with weaker surveillance networks or political incentives to downplay the crisis could easily project an illusion of containment simply by failing to test. If a person died of acute respiratory distress in a remote village during a massive regional wave, but no test was administered, official dashboards remained pristine while graveyards expanded.
The power and precision of excess mortality
To pierce through this fog of under-reporting, epidemiologists turned to excess mortality analysis, the gold standard for measuring public health catastrophes. Excess mortality calculates the difference between the total number of people who died from all causes during the pandemic and the number of deaths that would have been expected based on historical seasonal trends. This method neutralizes diagnostic gaps; it does not matter whether a death certificate explicitly lists coronavirus, cardiac arrest, or pneumonia. If a community experiences a sudden, statistically anomalous surge in total fatalities coinciding with a viral wave, those lives lost belong to the ledger of the pandemic.
When major global health institutions and independent research groups, such as the World Health Organization (WHO) and the Institute for Health Metrics and Evaluation (IHME), ran these models, the results shattered official narratives. Comprehensive analyses covering the initial years of the crisis revealed that the true global death toll was not hovering around 5 or 6 million, but was instead staggering closer to 15 to 18 million excess deaths.
This massive discrepancy, representing a global death toll roughly three times higher than official figures indicate, proves that the pandemic's lethality was vastly underestimated. The data forces us to conclude that COVID-19 was not merely a localized health disruption or a bad flu season, but a historic demographic shock that dramatically altered global life expectancy and community structures.
Direct vs. Indirect victims: A unified catastrophe
A critical nuance in analyzing these 15 to 18 million excess deaths involves distinguishing between direct viral destruction and indirect systemic collapse. Not every excess death was caused by acute viral pneumonia chewing through lung tissue. A significant portion of this catastrophic toll stems from the collateral damage inflicted on global healthcare systems.
When hospitals were overrun with COVID-19 patients, intensive care units vanished. Routine screenings for cancer, cardiovascular evaluations, and elective surgeries were abruptly canceled or indefinitely postponed. Millions of individuals suffering from chronic conditions, diabetes, kidney disease, hypertension, found themselves cut off from regular care or terrified to visit medical facilities for fear of nosocomial infection. Strict lockdowns, economic devastation, and isolation catalyzed spikes in mental health crises, substance abuse overdose fatalities, and untreated acute medical emergencies like strokes and heart attacks.
Some analysts attempt to compartmentalize these categories, separating those who suffocated from the virus from those who died because an ambulance took three hours to arrive. Yet, from an epidemiological and historical perspective, this distinction is semantic. Whether a patient succumbed to viral hypoxia or a ruptured appendix that went unoperated because every surgical theater was packed with COVID-19 cases, both deaths are direct consequences of the pandemic. The virus broke the machinery of modern civilization, and the resulting debris claimed millions of lives outside official statistics.
Facing the historical reality
The debate over how many people died from COVID-19 is settled not by looking at bureaucratic death certificates, but by examining the cold, unyielding mathematics of excess mortality. The evidence is definitive: official figures represent a dramatic illusion, masking a tragedy nearly three times larger than acknowledged. With a true death toll scaling between 15 and 18 million lives, the pandemic stands as one of the most lethal public health crises in modern history. Recognizing this massive toll is not an exercise in morbid accounting; it is an urgent imperative for global accountability, ensuring that future generations accurately measure the true cost of systemic vulnerability and medical disruption.
What specific region or demographic factor do you think played the biggest role in driving these massive discrepancies between official reports and actual excess mortality?